


The 99495 CPT code designates transitional care management (TCM) services for patients returning to a community setting after a medical facility discharge. The American Medical Association established this code to capture the extensive clinical and administrative work required to prevent hospital readmissions. Procedure 99495 covers a continuous 30-day service period that begins on the exact date a patient leaves an eligible facility.
Medical billers and coders must understand that the 99495 CPT description does not apply to a single office visit. It represents a bundle of non-face-to-face care coordination, medication management, and one mandatory clinical examination.
Understanding CPT code 99495 requirements
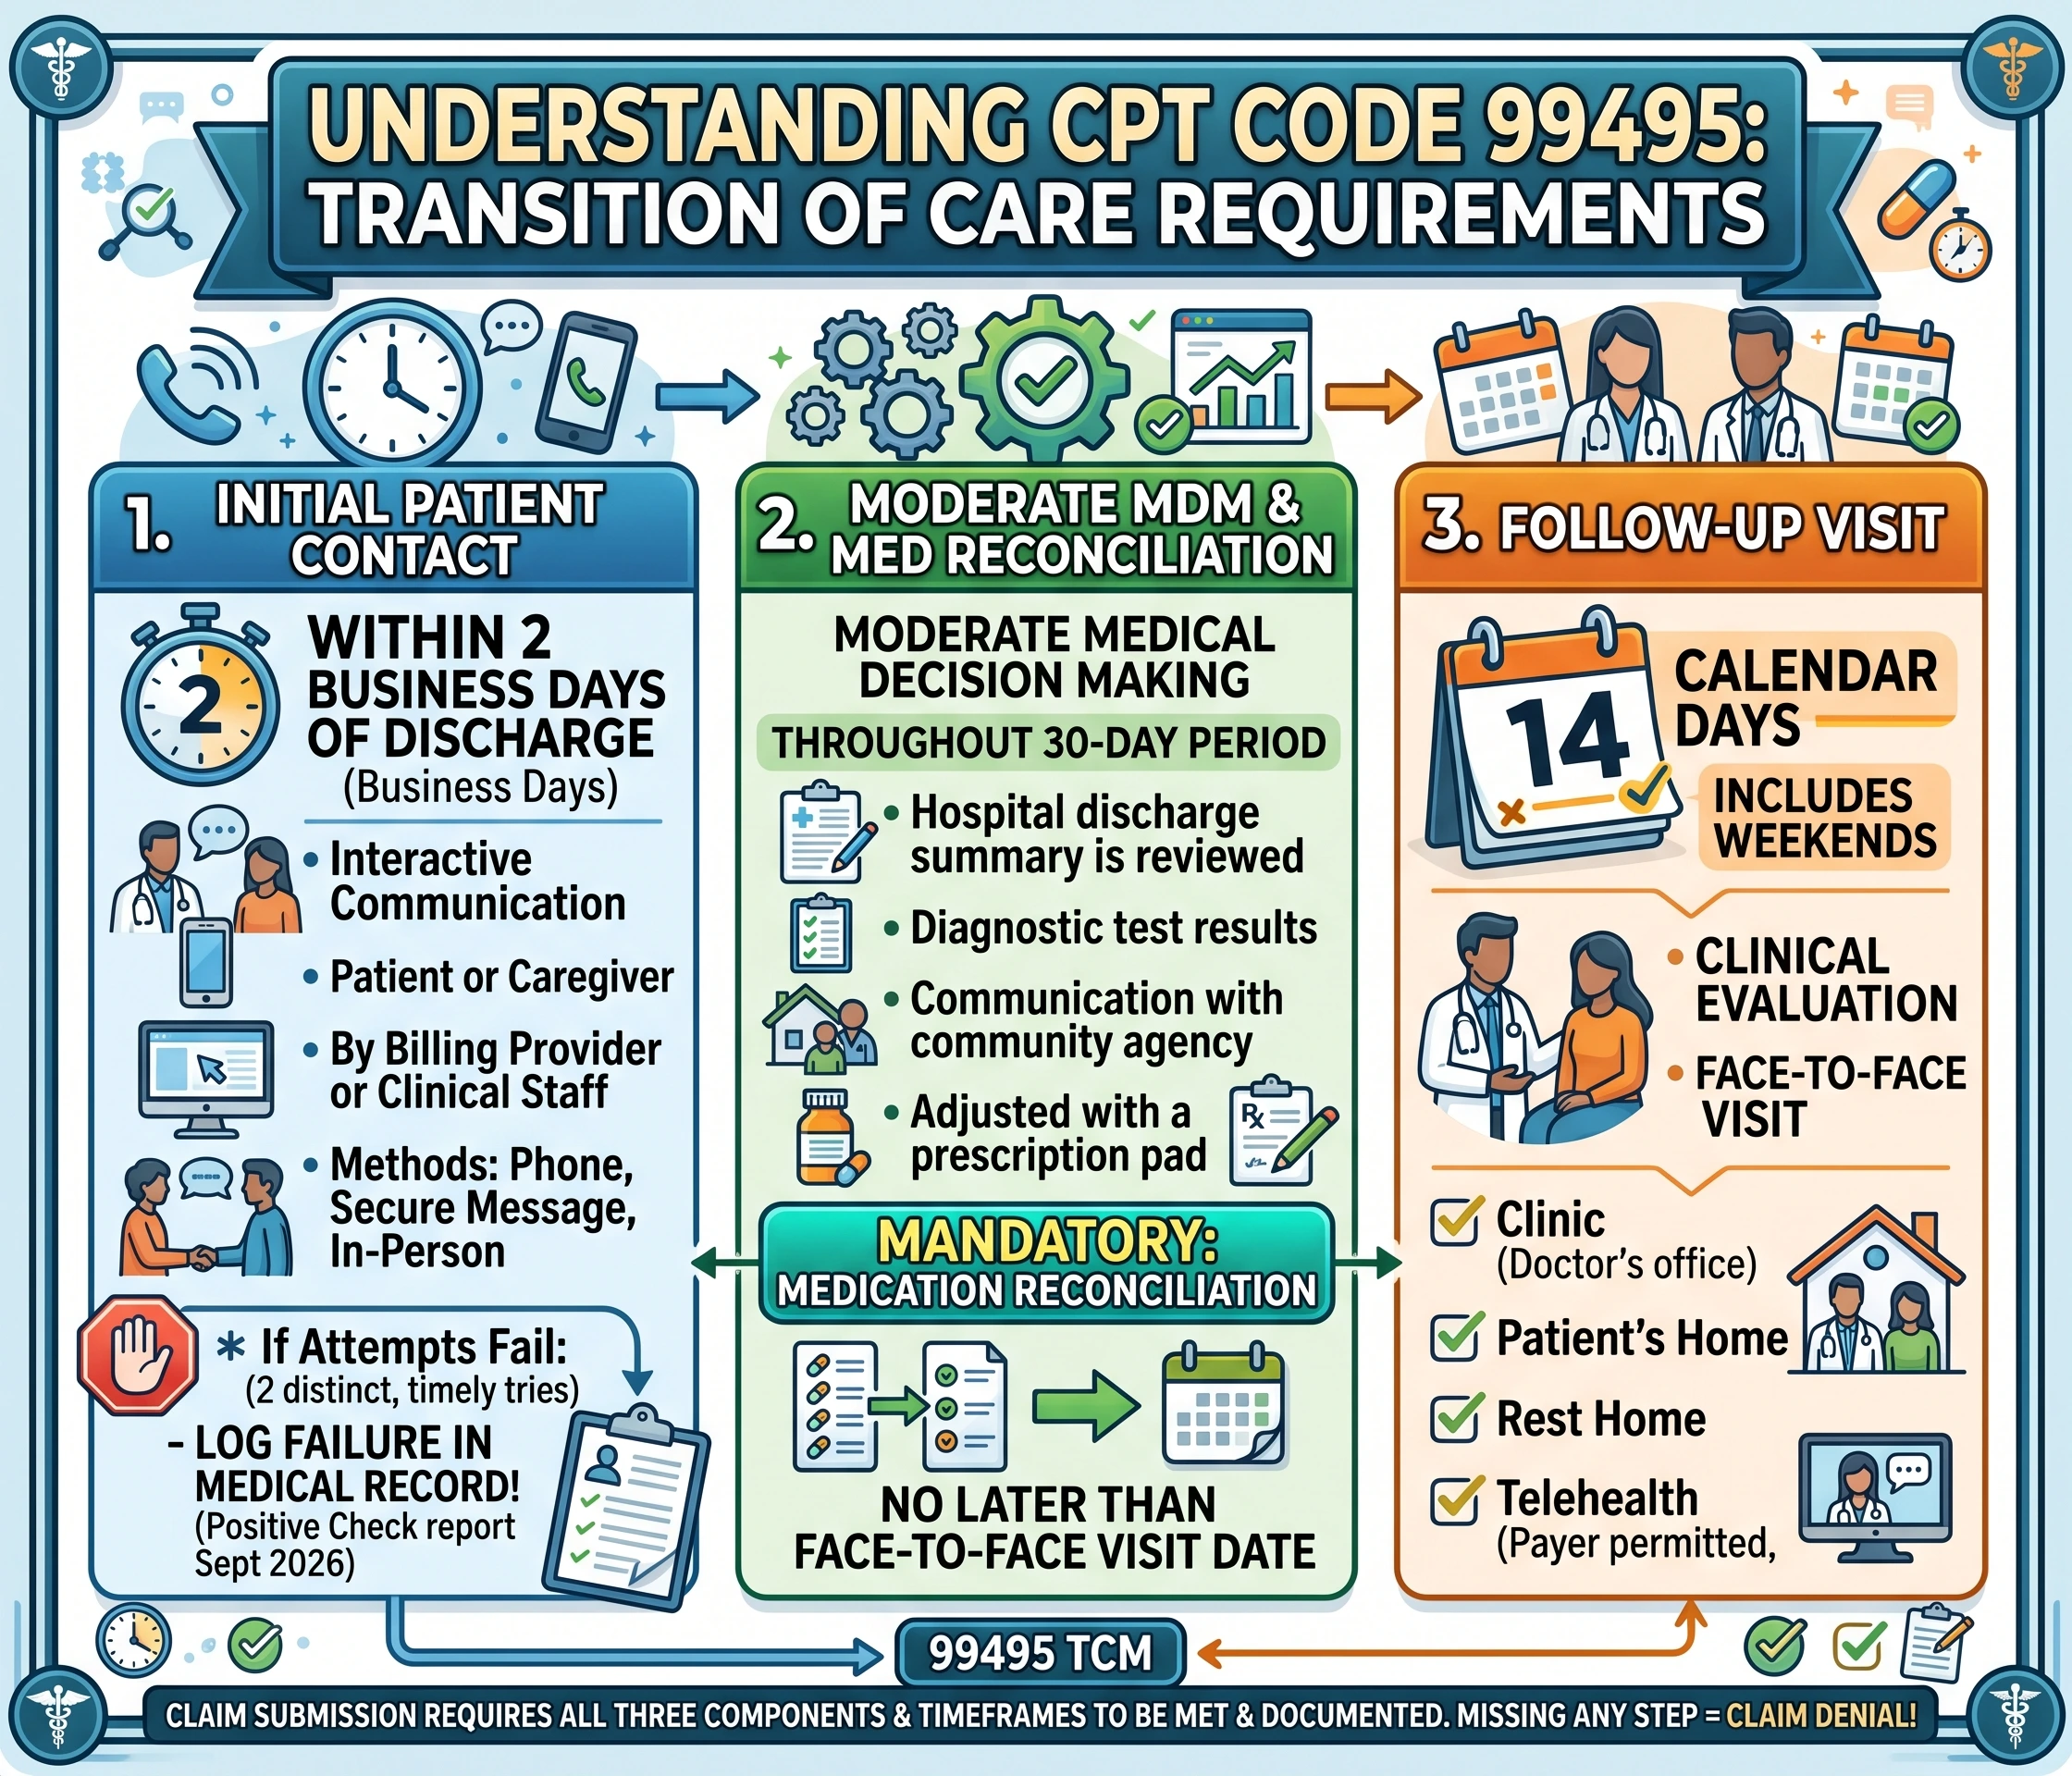
To submit a valid claim for billing code 99495, healthcare providers must complete three distinct components within specific timeframes. Missing any of these steps, or failing to document them accurately, will result in claim denial.
Initial patient contact after discharge
The first requirement of transition of care CPT 99495 is interactive communication. The billing provider or a qualified clinical staff member must contact the patient or their designated caregiver within two business days of discharge. This contact can occur via direct telephone call, secure electronic portal message, or an in-person conversation.
A September 2026 report by Positive Check indicates that if staff members cannot reach the patient after two distinct, timely attempts, they must log these failed efforts in the medical record. As long as the remaining clinical criteria are met, the provider may still report the service.
Moderate medical decision making
The 99495 CPT code description requires medical decision making (MDM) of at least moderate complexity throughout the 30-day period. This level of care management typically involves patients with multiple chronic conditions that are stable post-discharge. Providers meet this requirement by reviewing hospital discharge summaries, evaluating pending diagnostic tests, coordinating with community health agencies, and adjusting prescription regimens.
Medication reconciliation is a mandatory component of this process. The provider must reconcile the patient’s discharge medications with their pre-admission list no later than the date of the clinical examination.
The follow-up visit within 14 days
The final mandatory component is a clinical evaluation. Providers must conduct a face-to-face visit within 14 calendar days of the discharge date. This window includes weekends. The location of this follow-up visit is not strictly limited to an outpatient clinic. Practitioners can perform the evaluation in the patient’s home, a rest home, or via telehealth if current payer policies permit.
99495 time requirements and billing frequency limit
The 99495 billing frequency limit restricts providers to reporting this service only once per patient during the 30-day period following discharge. Only one physician or qualified healthcare professional can claim the transitional care codes 99495 and 99496 per episode of care.
Because the code covers a 30-day spectrum of patient discharge follow-up, the date of service on the claim must reflect the 30th day post-discharge.
Patient readmissions alter these 99495 billing guidelines. If a patient returns to the hospital before the required face-to-face visit takes place, the provider cannot bill TCM 99495. The practitioner must instead report standard evaluation and management codes for any services provided prior to the readmission. If the patient is readmitted after the face-to-face visit occurs, the provider can still submit code 99495, provided all other 30-day care coordination tasks were completed.
99495 vs 99496: differences in transitional care codes
Medical coders frequently evaluate CPT codes 99495 and 99496 together. Both represent transitional care services spanning a 30-day period. The distinction lies in the medical complexity of the patient’s case and the urgency of the required physical examination.
Requirement | CPT 99495 | CPT 99496 |
Medical decision making | Moderate complexity | High complexity |
Initial communication | Within 2 business days | Within 2 business days |
Face-to-face visit | Within 14 calendar days | Within 7 calendar days |
Patient profile | Stable chronic conditions | Complex, acute problems |
According to a September 2026 publication by Pabau, billing 99495 when the clinical documentation actually supports 99496 results in lost revenue. Conversely, submitting 99496 without documented high-complexity medical decision making creates severe audit risks.
99495 documentation requirements for medical records
Strict TCM documentation is necessary to secure reimbursement. Auditors from Medicare Administrative Contractors (MACs) frequently review these claims to verify compliance. An August 2025 bulletin from Noridian Medicare lists the minimum data points required in the patient’s chart.
A compliant 99495 medical record documentation file must explicitly state:
- The date the patient was discharged from the facility.
- The specific date and method of the initial interactive contact.
- The date of the face-to-face visit.
- Evidence supporting moderate medical decision making.
A November 2025 guide published by Optimantra recommends logging all non-face-to-face TCM work directly in the chart. This includes the time spent reviewing discharge paperwork, educating family members, and establishing referrals with community providers. Documenting the exact changes made during the medication reconciliation process is equally necessary to prove the provider executed the required clinical oversight.
Providers must also verify the patient’s discharge location. Eligible originating settings include acute care hospitals, inpatient rehabilitation facilities, long-term care hospitals, partial hospitalization programs, and skilled nursing facilities (SNFs).
99495 CPT code reimbursement and RVU
Reimbursement for transitional care management reflects the bundled nature of the service. Instead of paying separately for phone calls, chart reviews, and an office visit, payers issue a single payment based on the assigned Relative Value Unit (RVU).
The work RVU for 99495 is 2.11. For comparison, the higher-complexity 99496 code carries a work RVU of 3.05. Total 99495 reimbursement rates vary based on geographic locality, whether the service was performed in a facility or non-facility setting, and the annual Medicare Physician Fee Schedule (PFS) conversion factor.
The Centers for Medicare & Medicaid Services (CMS) allows concurrent billing of TCM alongside Chronic Care Management (CCM). Providers cannot, however, count the time spent on TCM activities toward the required time thresholds for CCM services.
Can you bill 99495 and 99214 together?
A frequent source of confusion among medical billers is whether 99214 and 99495 can be billed together. You cannot bill a standard evaluation and management code, such as 99214 (established patient, moderate complexity), to represent the required TCM follow-up visit. The payment for that specific clinical examination is already bundled into the 99495 reimbursement.
There is one specific exception. A provider can bill 99495 and 99214 on the same date only if the patient presents with a distinct, medically necessary problem that is entirely unrelated to their hospital discharge.
In this scenario, the medical coder must append modifier 25 to the 99214 code to indicate it was a separately identifiable service. Providers who mistakenly bill their post-discharge follow-up as a standard 99214 visit instead of utilizing the appropriate TCM code under-report their clinical effort by approximately 0.6 work RVUs.
Accurate application of the 99495 CPT code requires coordinated communication across the clinical team. Front-desk staff must secure the initial two-day contact, clinicians must perform moderate decision making within the 14-day window, and billing departments must hold the claim until the 30-day service period concludes. Proper execution of these steps ensures compliance with CMS regulations and secures accurate compensation for post-discharge care.