

Outpatient observation billing is an area of hospital revenue cycle management where small documentation mistakes can create payment problems. Incorrect observation hours, missing physician orders, outdated CPT codes, and inappropriate patient status classifications can affect Medicare reimbursement and increase the likelihood of claim denials.
This Outpatient Observation Billing Guide explains Medicare observation billing rules, CPT and HCPCS codes, revenue codes, documentation requirements, and claim submission procedures applicable in 2026. It also addresses common misunderstandings about observation duration and the distinction between outpatient observation and inpatient admission.
Healthcare providers, hospital billing teams, and medical coding students need to understand that observation services involve separate requirements for facility billing and professional services. Applying the correct rules to each claim is essential for accurate reimbursement.
What is outpatient observation billing?
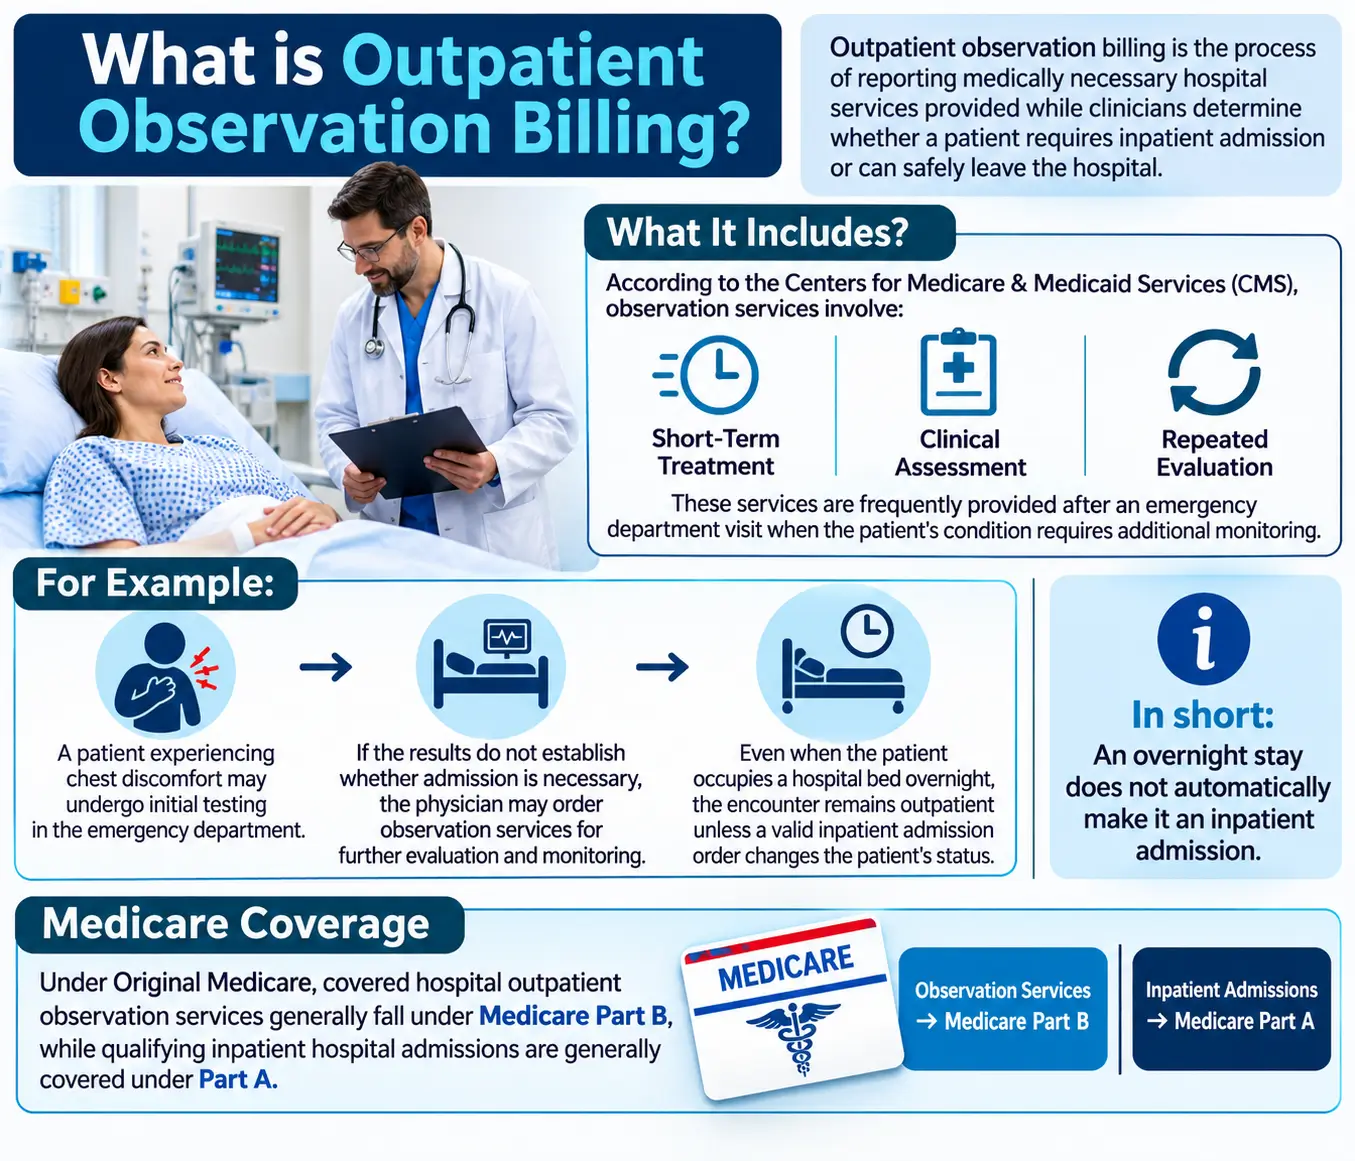
Outpatient observation billing is the process of reporting medically necessary hospital services provided while clinicians determine whether a patient requires inpatient admission or can safely leave the hospital.
According to the Centers for Medicare & Medicaid Services (CMS), observation services involve short-term treatment, clinical assessment, and repeated evaluation. These services are frequently provided after an emergency department visit when the patient’s condition requires additional monitoring.
For example, a patient experiencing chest discomfort may undergo initial testing in the emergency department. If the results do not establish whether admission is necessary, the physician may order observation services for further evaluation and monitoring.
Even when the patient occupies a hospital bed overnight, the encounter remains outpatient unless a valid inpatient admission order changes the patient’s status.
Under Original Medicare, covered hospital outpatient observation services generally fall under Medicare Part B, while qualifying inpatient hospital admissions are generally covered under Part A.
Medicare observation billing rules for 2026
The Medicare observation billing rules require hospitals to establish medical necessity, obtain an appropriate observation order, document clinical services, and accurately report the time spent receiving observation care.
CMS explains these requirements in the Medicare Claims Processing Manual, Chapter 4, Section 290.
Observation services must be ordered by a physician or another authorized practitioner acting within applicable state law and hospital bylaws. The order should correspond with documented clinical findings supporting the need for additional evaluation.
A patient’s continued presence in the hospital does not automatically establish medical necessity for observation services. Hospitals must show why continued assessment or treatment was needed to make an appropriate discharge or admission decision.
Observation services cannot simply replace routine recovery following outpatient surgery, administrative waiting periods, or inpatient services that are medically necessary.
For 2026, hospitals should also recognize that Medicare Administrative Contractors (MACs) conduct short-stay inpatient medical reviews under CMS’s Targeted Probe and Educate program. The transition of these reviews from Quality Improvement Organizations took effect September 1, 2025.
Observation CPT codes and HCPCS codes in 2026
Accurate observation coding begins with distinguishing physician evaluation and management services from hospital facility charges.
Physician observation CPT codes
Beginning January 1, 2023, CPT combined hospital inpatient and observation E/M services into a shared coding structure. These codes remain applicable under the 2026 Medicare observation coding guidelines.
CPT code | Description |
99221–99223 | Initial hospital inpatient or observation care |
99231–99233 | Subsequent hospital inpatient or observation care |
99234–99236 | Hospital inpatient or observation care involving qualifying same-day admission and discharge |
99238 | Hospital inpatient or observation discharge management, 30 minutes or less |
99239 | Hospital inpatient or observation discharge management, more than 30 minutes |
Previously used observation-specific codes, including 99217, 99218–99220, and 99224–99226, were deleted effective January 1, 2023.
Therefore, CPT 99217 is no longer the appropriate observation discharge code for services performed in 2026.
Physicians select the appropriate E/M level based on medical decision-making or qualifying practitioner time, following current CPT and Medicare requirements.
Hospital facility observation codes
Hospitals use HCPCS codes to report facility observation services rather than using physician E/M codes for the observation room charges.
HCPCS G0378 reports hospital observation services per hour. Facilities use this code to communicate the number of reportable observation hours.
HCPCS G0379 identifies a direct referral for hospital observation care. It applies to qualifying situations in which a patient is referred directly for observation after evaluation by a community physician, without an associated hospital emergency department or clinic encounter.
G0379 should not automatically be assigned to every observation encounter.
Observation revenue codes for hospital billing
Revenue codes identify the hospital department or service category associated with a charge.
For outpatient observation services, CMS recognizes revenue code 0760 as the general treatment or observation room classification and revenue code 0762 as the observation room classification.
Revenue code 0762 is commonly used with G0378 to report hospital observation charges.
The revenue code identifies the service category, while the HCPCS code provides more specific information about the service delivered.
Hospitals should also report separately identifiable ancillary services, such as laboratory testing and diagnostic imaging, under the applicable revenue and procedure codes when appropriate.
Correct revenue code selection helps ensure that observation charges are classified consistently within institutional claims.
G0378 billing guidelines and observation time calculation
Observation time is one of the most common sources of hospital outpatient billing errors.
Under CMS guidelines, observation time begins when observation care actually starts in accordance with an authorized practitioner’s order. The starting clock time must be supported by documentation in the medical record.
The observation period ends when all medically necessary observation-related services have been completed.
This may occur before the patient physically leaves the hospital. However, observation time can include medically necessary follow-up services performed after a discharge order if the patient continues to require observation-related care.
Waiting for transportation after treatment has finished cannot be counted as observation time.
CMS also instructs hospitals not to count routine preparation and recovery periods already included in another service. Observation time should not overlap with procedures for which active monitoring is included in the procedure itself.
Example of observation hours calculation
Consider a patient whose medically necessary observation care begins at 3:00 PM and ends at 10:30 PM.
The observation period totals seven hours and thirty minutes. Under CMS’s nearest-hour reporting instruction, the facility would report eight units of G0378, assuming the entire period meets observation billing requirements.
If observation services continue across midnight, hospitals generally report the total observation hours on one claim line using the date observation began.
Accurate nursing documentation and electronic timestamps help prevent unsupported observation units.
Medicare observation hours limit: 24, 48, and 72 hours
Medicare does not establish a universal 24-hour or 48-hour maximum that automatically terminates medically necessary observation care.
CMS explains that observation decisions can usually be made within 24 hours and generally within 48 hours. Observation extending beyond 48 hours is expected to be unusual and requires appropriate clinical justification.
The frequently discussed 48-hour observation rule is therefore a medical necessity consideration, rather than an absolute national billing limit.
Similarly, there is no general Medicare rule permitting every patient to remain under observation for 72 hours.
Extended observation services should prompt additional clinical review to determine whether continued outpatient monitoring is appropriate or whether inpatient admission is medically necessary.
Hospitals must document the clinical circumstances supporting the actual duration of observation care.
How the Medicare Two-Midnight Rule affects observation status
The Medicare Two-Midnight Rule helps determine when hospital inpatient admission is generally appropriate for Part A payment.
When the admitting practitioner reasonably expects medically necessary hospital care to span at least two midnights, inpatient admission is generally appropriate, provided the medical record supports that expectation.
Certain exceptions permit inpatient payment for shorter stays, depending on medical circumstances and applicable CMS policies.
Time spent receiving medically necessary hospital outpatient care before inpatient admission may be considered when evaluating the two-midnight benchmark.
However, an observation encounter does not automatically become an inpatient admission simply because the patient remains in the hospital across two midnights.
A valid inpatient order and supporting clinical documentation are necessary to establish inpatient status.
Observation discharge CPT code and same-day billing
Professional billing requirements depend partly on whether observation begins and ends on the same calendar date.
When observation begins and ends on the same date and lasts less than eight hours, the treating practitioner generally reports initial hospital inpatient or observation care using CPT 99221–99223. A separate discharge management code is not reported.
For qualifying same-day stays lasting at least eight hours but less than 24 hours, CPT 99234–99236 represents the combined admission and discharge service.
When observation begins on one calendar date and discharge occurs on another, the treating practitioner generally reports the appropriate initial hospital care code and discharge management code on their respective dates.
These rules involve practitioner billing and should not be confused with the separate eight-hour eligibility requirement for Medicare’s Comprehensive Observation Services APC.
Medicare payment for hospital observation services
Under Medicare’s Hospital Outpatient Prospective Payment System (OPPS), G0378 is generally assigned packaged payment status. This means hospitals do not receive a separate payment for each reported observation hour.
Qualifying observation encounters may instead be paid through Comprehensive APC 8011, which covers certain extended assessment and observation encounters.
Eligibility generally requires at least eight reported observation hours, an appropriate associated hospital visit or direct referral, and compliance with applicable procedure and documentation requirements.
Claims involving certain surgical procedures or services with designated payment status indicators may not qualify for Comprehensive APC 8011.
An observation encounter lasting fewer than eight hours may still be reportable when medically necessary, although it does not meet the eight-hour requirement for this comprehensive payment category.
Payment arrangements for critical access hospitals, Medicare Advantage plans, and other payers may differ.
Documentation required for outpatient observation billing
Observation medical necessity must be established through the clinical record rather than the billing code alone.
The documentation should identify the reason for observation, the practitioner’s order, patient symptoms, relevant examination findings, monitoring requirements, treatment provided, and reassessment findings.
The medical record should also establish observation start and end times and explain the decision to discharge the patient or admit them as an inpatient.
For instance, if observation is ordered because of persistent dizziness and unstable blood pressure, the record should describe the clinical findings, monitoring performed, response to treatment, and eventual disposition.
A statement indicating only that the patient was kept overnight is generally insufficient to establish medical necessity.
Hospitals should also meet Medicare Outpatient Observation Notice (MOON) requirements. Medicare beneficiaries receiving observation services for more than 24 hours must receive the required notice within the applicable CMS timeframe, generally no later than 36 hours after observation begins, or sooner when discharge, transfer, or inpatient admission occurs.
Common outpatient observation billing denials
Observation claims can encounter denials or payment reductions when billing information conflicts with clinical documentation or payer processing requirements.
One frequent problem involves observation hours that include routine recovery, administrative delays, or time after medically necessary monitoring has ended.
Another involves missing or unclear observation orders. Without evidence of an appropriate order, the facility may have difficulty establishing that observation services were authorized.
Outdated CPT codes also create processing problems, particularly when billing systems still contain observation codes deleted in 2023.
Incorrect reporting of G0379, unsupported diagnosis selection, and inappropriate inpatient-to-outpatient status changes can create additional billing complications.
Hospitals can reduce these problems by reviewing observation orders, nursing timestamps, physician notes, claim codes, and admission status before submitting claims.
Observation-to-inpatient denial management
When a patient’s condition requires inpatient admission after an observation period, documentation should explain the clinical change or new information supporting that decision.
The inpatient order must be supported by an appropriate assessment of the patient’s condition and anticipated need for hospital services.
If Medicare denies inpatient payment based on patient status, the hospital should examine the original admission decision, the information available to the treating practitioner, and the relevant medical necessity requirements.
Appeal documentation may include physician assessments, diagnostic findings, treatment records, comorbidities, and clinical explanations supporting the expected hospital stay.
Simply demonstrating that the patient remained in the hospital for two nights does not establish that every inpatient admission met Medicare payment criteria.
Frequently asked questions
What is the difference between outpatient observation and inpatient admission?
Observation is an outpatient service used for evaluation, treatment, and monitoring while determining the appropriate patient disposition. Inpatient admission requires a qualifying admission order and supporting medical necessity documentation.
What is the revenue code for observation services?
Revenue code 0762 identifies observation room services. CMS also recognizes revenue code 0760 for the general treatment or observation room category.
What is the observation discharge CPT code in 2026?
CPT 99238 and 99239 are used for qualifying discharge management services. CPT 99234–99236 applies to qualifying same-day admission and discharge encounters. CPT 99217 was deleted in 2023.
Can Medicare observation services exceed 48 hours?
Yes. However, CMS indicates that medically necessary observation services lasting beyond 48 hours should occur only in unusual circumstances. Extended observation requires adequate clinical justification.
How can hospitals prevent observation billing denials?
Hospitals should verify observation orders, medical necessity, time calculations, current procedure codes, revenue codes, patient status, and documentation before claim submission.
Accurate observation billing begins with clinical documentation
This Outpatient Observation Billing Guide explains why correct Medicare reimbursement depends on the relationship between clinical decisions, patient status, documentation, and claim reporting.
For 2026, hospitals should use the current observation E/M code ranges, report eligible facility hours with G0378, apply appropriate revenue codes, and follow CMS rules for observation duration and inpatient admission.
Consistent documentation, accurate observation-hour calculations, and pre-submission claim reviews can help healthcare organizations identify billing errors before they become denials.