

Cash flow dictates the financial survival of any medical practice. The metric that most accurately tracks this financial health is days in accounts receivable. Understanding how to calculate AR days in medical billing provides practice managers and billing students with a direct measurement of revenue cycle efficiency. It shows exactly how long it takes for a practice to turn services rendered into cash in the bank. When this number creeps upward, it signals bottlenecks in claims processing, coding inaccuracies, or patient collection workflows.
What is AR days in medical billing?
Accounts receivable days quantify the average number of days an invoice remains unpaid after a provider bills a patient or insurance company. In healthcare RCM (revenue cycle management), this metric serves as a primary diagnostic tool. Medical billing accounts receivable includes all outstanding balances owed to the practice. By measuring the average collection period, billing teams can identify if insurance payers are delaying reimbursements or if self-pay patients are ignoring paper statements.
Tracking this metric allows administrators to measure the daily effectiveness of their billing staff. A low number indicates that claims are clean, clearinghouses are processing files quickly, and follow-up teams are working denials aggressively.
How to calculate AR days in medical billing
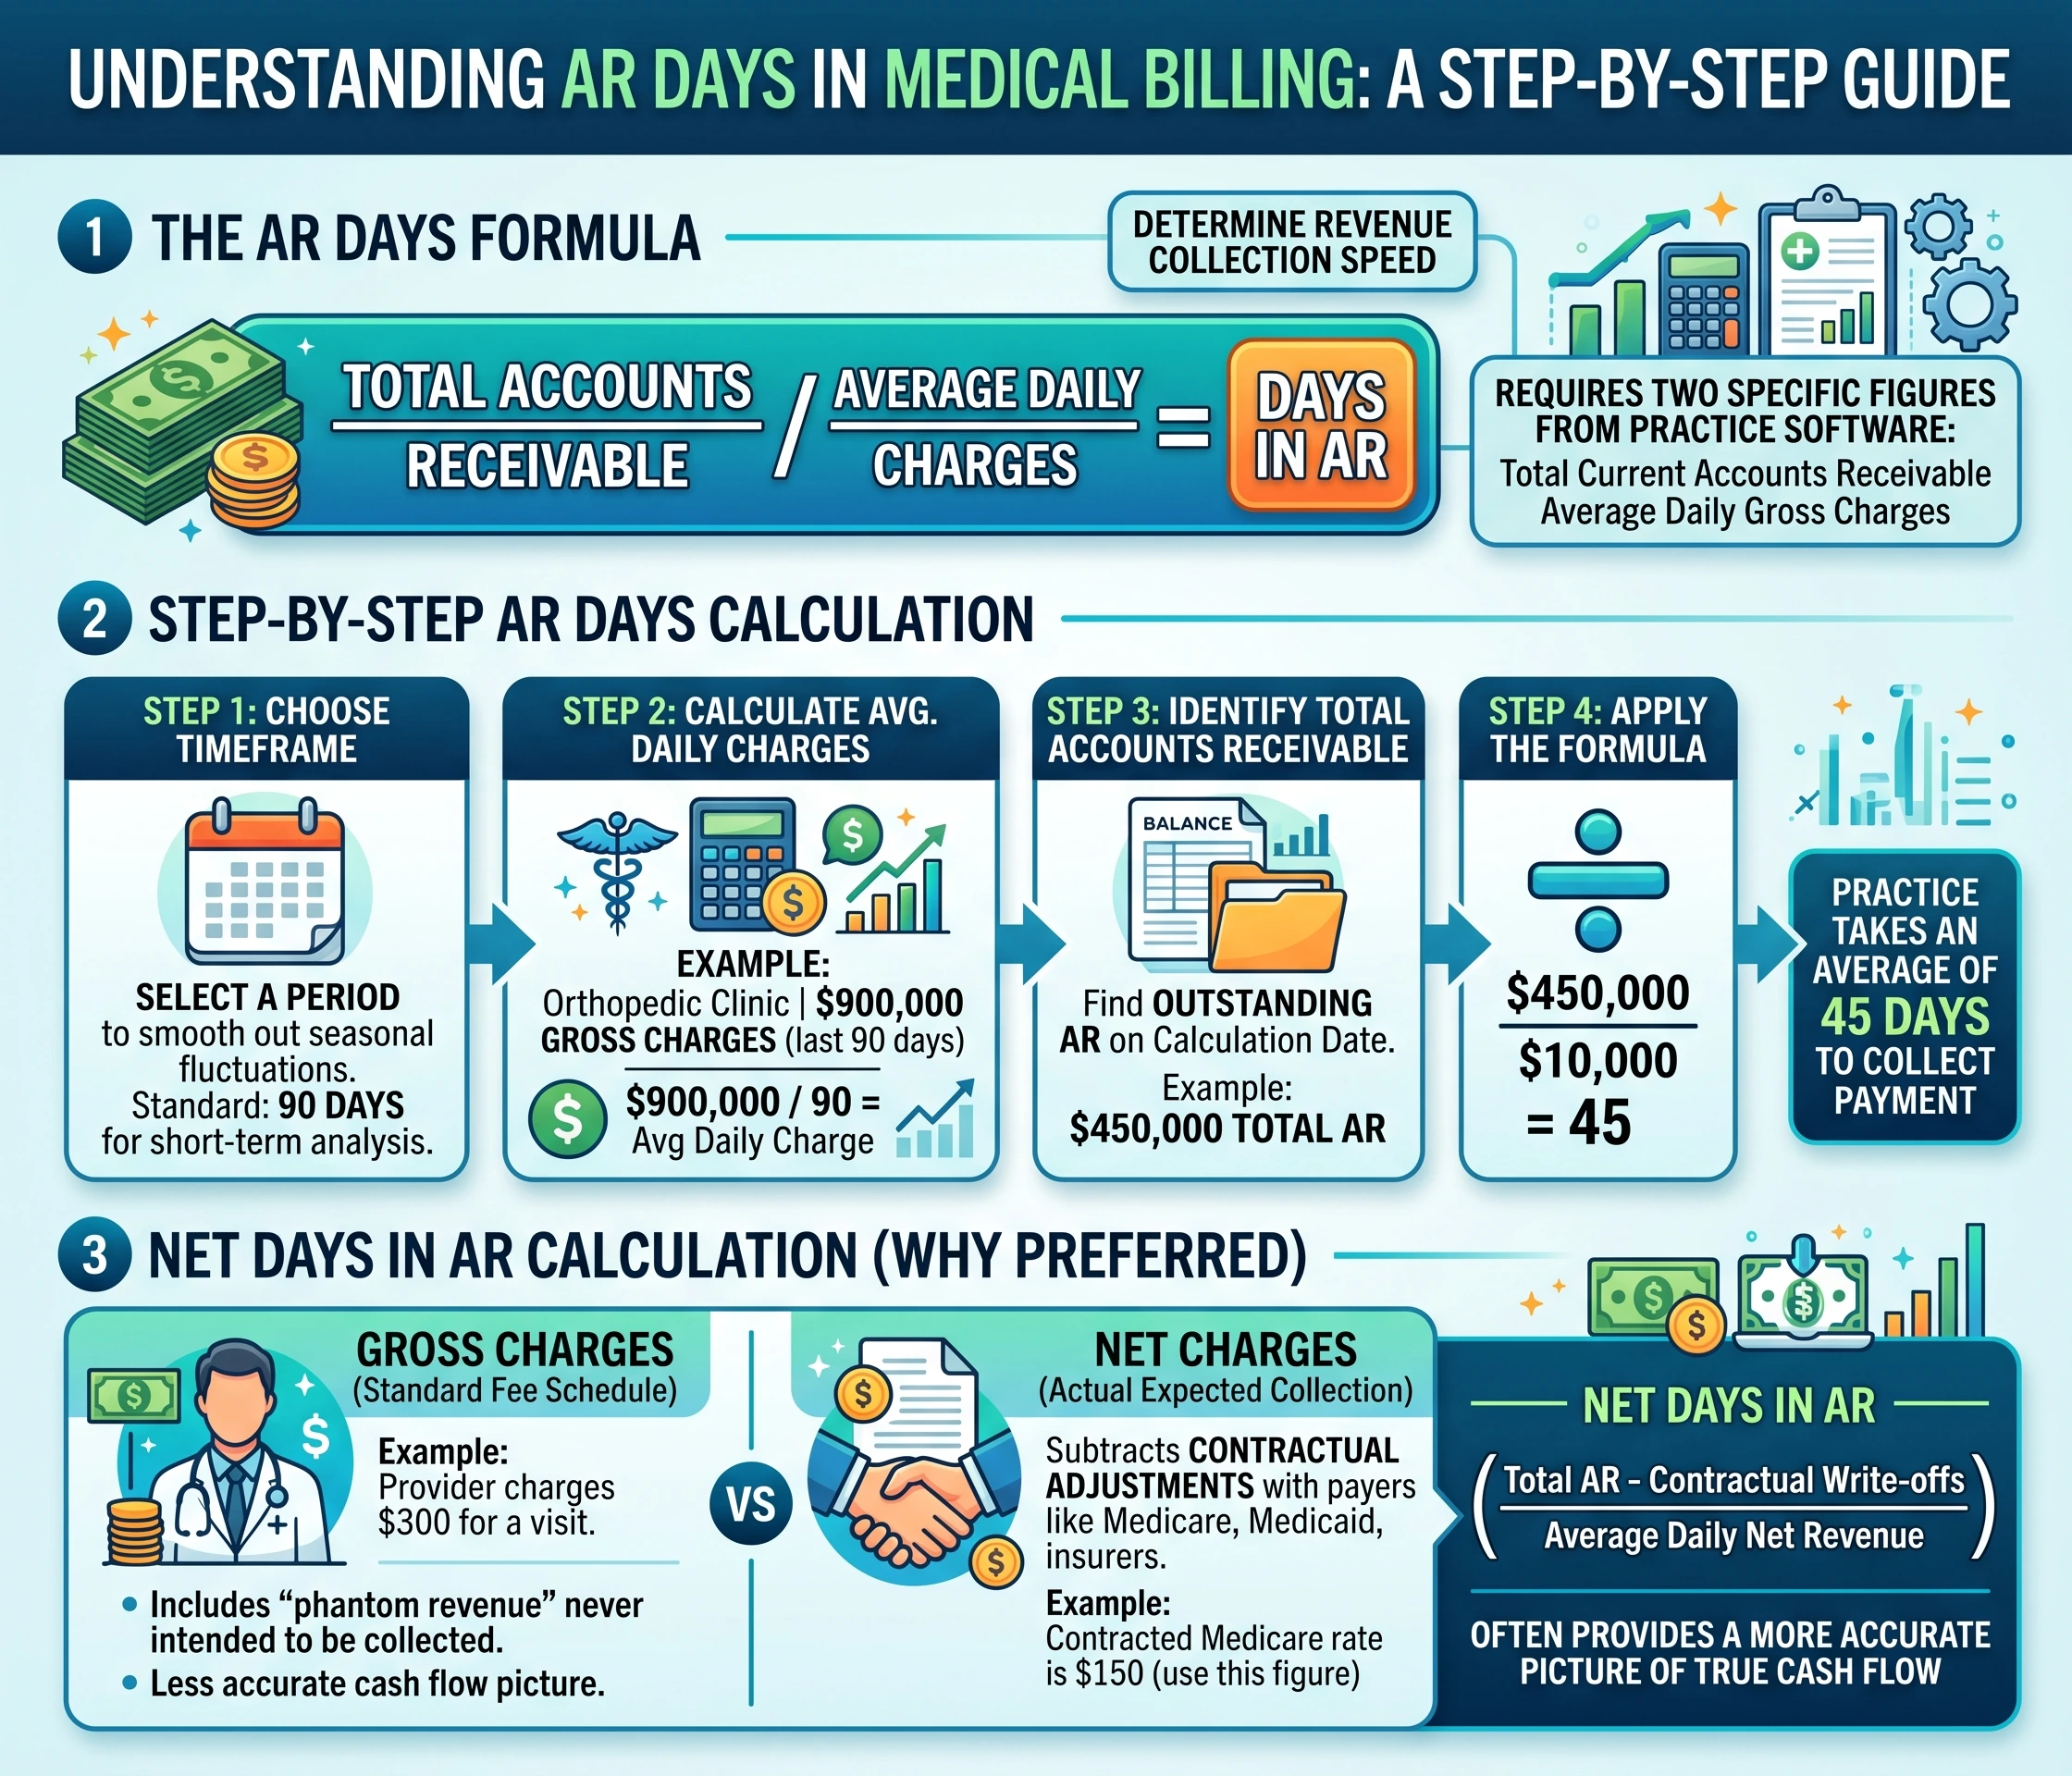
To determine how fast a clinic collects its revenue, you need two specific figures from the practice’s financial software. You need the total current accounts receivable and the average daily gross charges.
AR days formula in medical billing
The standard days in accounts receivable formula requires a straightforward division equation.
Total Accounts Receivable / Average Daily Charges = Days in AR
Step-by-step AR days calculation in medical billing
First, determine the timeframe. Most practices use a three-month, six-month, or twelve-month period to smooth out seasonal fluctuations in patient volume. A 90-day period is the standard length for short-term financial analysis.
Calculate the average daily charges for that specific period. If an orthopedic clinic billed $900,000 in gross charges over the last 90 days, divide $900,000 by 90. The average daily charge is $10,000.
Next, identify the total accounts receivable on the date of calculation. If the total outstanding AR on the balance sheet is $450,000, apply the AR days calculation formula.
Divide $450,000 by $10,000. The result is 45. The practice takes an average of 45 days to collect payment for its clinical services.
Net days in AR calculation for healthcare
Many financial analysts prefer using net charges rather than gross charges. Gross charges represent the provider’s standard fee schedule. Net charges represent the actual amount the practice expects to collect after subtracting contractual adjustments agreed upon with payers like Medicare, Medicaid, or commercial insurers.
To calculate net days in AR, divide the total accounts receivable (minus expected contractual write-offs) by the average daily net revenue. This net days in AR calculation often provides a more accurate picture of cash flow because it ignores phantom revenue that the practice never intended to collect. A practice charging $300 for a visit but contractually obligated to accept $150 from Medicare should base their internal financial projections on the $150 figure.
Target days in accounts receivable healthcare benchmarks
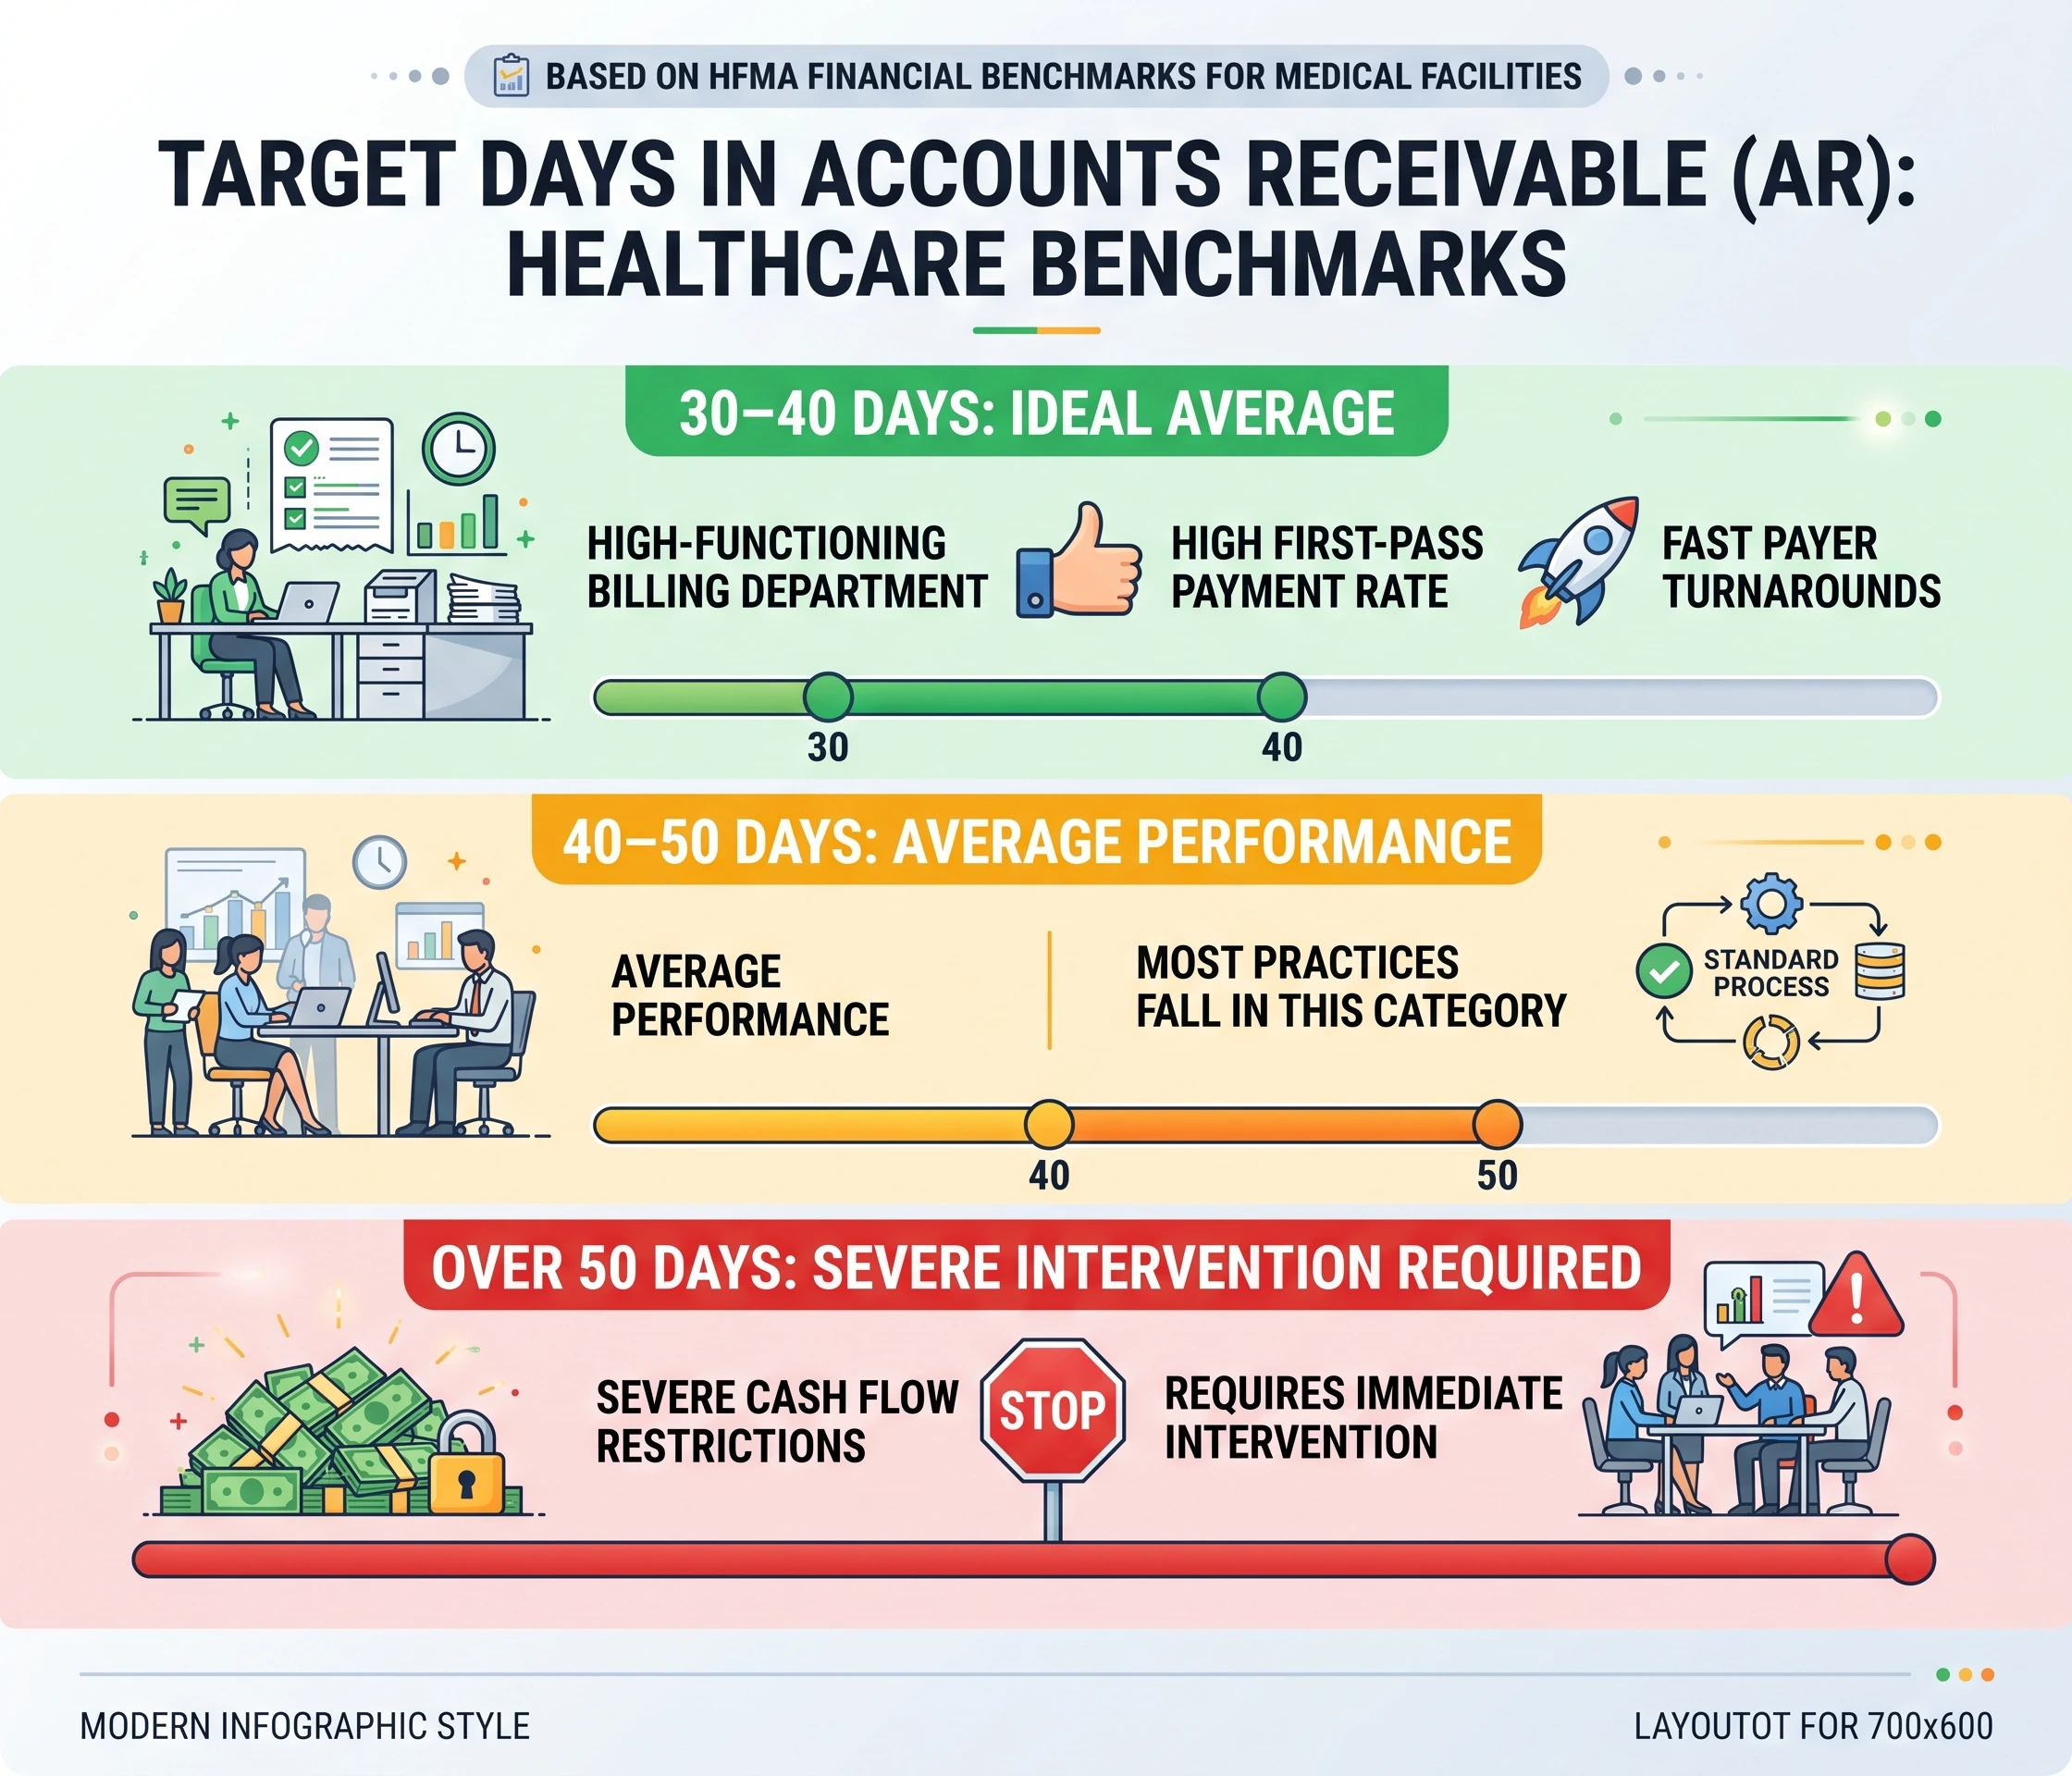
Billing coders and practice administrators need a baseline to evaluate their calculation results. The Healthcare Financial Management Association (HFMA) provides standard financial benchmarks for medical facilities.
An ideal days in AR average falls between 30 and 40 days. This indicates a highly functioning billing department with a high first-pass payment rate and fast payer turnarounds.
A healthcare AR benchmark of 40 to 50 days represents average performance. Most practices fall into this category.
If the calculation exceeds 50 days, the practice is experiencing severe cash flow restrictions and requires immediate intervention.
Variations by payer type and specialty
These targets vary by medical specialty and payer mix. High-volume primary care practices often maintain lower AR days than surgical specialties. Surgical claims frequently require complex medical coding, extensive operative documentation, and prior authorizations. If a surgeon performs a procedure without securing the correct prior authorization, the payer will deny the claim. The subsequent appeal process easily pushes that specific claim well past the 90-day mark.
The payer mix heavily influences the final calculation. Medicare dictates a mandatory 14-day payment floor for clean electronic claims. Clinics with a heavy Medicare patient base naturally have lower AR days. Clinics that handle a high volume of Workers’ Compensation or personal injury auto claims often see their AR days inflate drastically. These specialized claims require paper medical records, face frequent litigation, and routinely take over 100 days to pay.
What does a high number of days in A/R indicate?
When the days in A/R calculation exceeds 50, the medical practice faces specific operational failures. High AR days rarely stem from a single source.
Insurance claim denials are the most common culprit. If a coding team submits claims with incorrect modifiers, missing National Provider Identifiers (NPI), or insufficient documentation, payers reject them entirely. The time spent manually correcting and resubmitting these claims artificially inflates the average collection time.
Credentialing delays also drive up this metric. If a new physician joins a practice but the administrative team has not completed their enrollment with Medicare or commercial payers, the practice must hold those claims. The charges sit in accounts receivable, aging daily until the credentialing clears and the payer issues a welcome letter.
Ineffective patient accounts receivable processes contribute heavily to delayed payments. High-deductible health plans shift a larger portion of the financial burden directly to patients. If a practice mails paper statements once a month without offering digital payment portals, patient balances linger in the system. Collecting from individuals traditionally takes much longer than collecting from electronic insurance payers.
Managing AR days through AR aging analysis
Calculating the primary number is only the first step in medical AR management. To identify exactly where money is stuck, billers must break down the total receivables into specific timeframes. This process is called AR aging analysis.
Financial systems separate outstanding balances into standard AR aging buckets based on the date of service or the date the original claim was generated.
Aging Bucket | Expected Percentage of Total AR | Performance Indicator |
0 to 30 days | 60% or higher | Optimal. Indicates fast processing and clean claims. |
31 to 60 days | 20% or lower | Average. Usually contains claims requiring minor corrections. |
61 to 90 days | 10% or lower | Warning sign. Often involves patient balances or denied claims. |
91 to 120 days | 5% or lower | Severe risk. High likelihood of bad debt or timely filing denials. |
Over 120 days | Less than 5% | Critical. These funds are rarely collected without collections agencies. |
Monitoring these buckets allows billing managers to direct their staff effectively. Instead of working claims randomly, follow-up teams can focus exclusively on the 61 to 90-day bucket to prevent those balances from crossing into the uncollectible category.
Separating insurance AR from patient AR
Effective AR management requires separating payer balances from patient balances during analysis. An insurance claim in the 45-day bucket requires a phone call to a payer representative to check the claim status or submit an appeal. A patient balance in the 45-day bucket requires sending a final notice statement or setting up a monthly payment plan. Mixing these two distinct workflows slows down the billing staff and reduces total daily output.
How to reduce AR days in medical billing
Bringing a high days in accounts receivable metric down to the ideal target requires systemic changes in the revenue cycle workflow.
Implement claim scrubbing software. This technology analyzes electronic claims for coding errors, National Correct Coding Initiative (NCCI) edits, and missing demographic information before the clearinghouse receives them. Catching errors before submission guarantees a higher first-pass payment rate.
Enforce point-of-service collections. Front desk staff should collect copayments, coinsurance, and outstanding balances before the patient sees the physician. According to standard industry data, the probability of collecting a patient balance drops below 50% once the patient leaves the clinic. Shifting the collection effort to the front of the revenue cycle prevents small patient balances from aging in the system.
Establish strict timely filing protocols. Every insurance payer dictates a specific window during which a provider can submit a claim. Medicare requires submission within one calendar year of the service date. Some commercial payers limit this window to 90 days or even 60 days. If an unworked claim misses this deadline, the practice must write off the entire balance.
Conduct regular denial management audits. Track the most common denial codes returned by payers. If a commercial payer repeatedly denies claims for a specific unlisted procedure code, the coding team can adjust their documentation templates. Providing the required operative notes on the first submission prevents the denial entirely.
Respond to clearinghouse rejections immediately. Clearinghouse rejections occur before a claim even reaches the payer. These usually involve basic formatting errors, such as a missing digit in a subscriber ID or an invalid date of birth. Because the payer never received the claim, the timely filing clock continues to tick. Billing staff should correct clearinghouse rejections daily to prevent claims from aging out.
Tracking days in AR to secure practice revenue
Monitoring accounts receivable days forces medical practices to confront inefficiencies in their billing operations. The healthcare industry operates on tight profit margins. Delayed cash flow limits a facility’s ability to purchase medical equipment, hire nursing staff, or expand patient services.
By learning how to calculate AR days in medical billing accurately, financial administrators gain a precise measurement of their revenue cycle’s performance. Evaluating the days in A/R calculation alongside detailed AR aging buckets removes the guesswork from medical billing. When practice managers apply the AR days calculation formula monthly and compare their results against target industry benchmarks, they isolate specific payment bottlenecks. Addressing those administrative errors guarantees that healthcare providers receive full compensation for the medical care they deliver.