


Radiology billing requires agreement between several records: the referring clinician’s order, the examination performed, the radiologist’s report, the authorization, and the claim. A discrepancy between any of them can create additional work or a payment dispute.
The common challenges in radiology medical billing extend beyond incorrect codes. They include incomplete clinical information, authorization mismatches, confusion over professional and technical components, and payments accepted without checking the contracted allowance.
For providers and billing students, understanding where an error begins helps determine the appropriate correction. This guide focuses on diagnostic imaging, with practical controls for each stage of revenue cycle management.
Where common challenges in radiology medical billing begin

An effective review follows the examination from scheduling through payment. Organize that review around four questions:
- Does the documentation support the examination?
- Does the claim accurately describe the service and billing component?
- Did the payer receive and adjudicate it correctly?
- Does the payment match the applicable reimbursement terms?
Assign responsibility for each question. Scheduling staff can verify authorization details, while coders resolve documentation discrepancies and payment specialists investigate contractual differences. A shared work queue should show the owner, deadline, and next action for every unresolved account.
1. Incomplete orders and medical necessity documentation
An imaging order may identify the requested examination without explaining the clinical reason for it. Billing staff then lack the information needed to evaluate coverage or respond to a records request.
CMS’s Medicare Benefit Policy Manual, Chapter 15, explains diagnostic test ordering requirements. Medicare requires documentation confirming that the treating practitioner intended to order the test and that it was medically necessary. A missing signature on an order is not automatically equivalent to a missing valid order; the surrounding medical record matters.
How to fix it
Create an intake review that checks the requested examination, clinical indication, ordering practitioner, and supporting records. For scheduled services, request missing information early enough for the referring office to respond.
Use specific queries. “Please provide the documented symptoms and relevant examination findings supporting this MRI” gives the office a clearer task than “Please send medical necessity.”
Keep clinical records accessible to the billing team. An authorization number alone does not supply the clinical evidence needed to answer a documentation request.
2. Prior authorization that does not match the examination
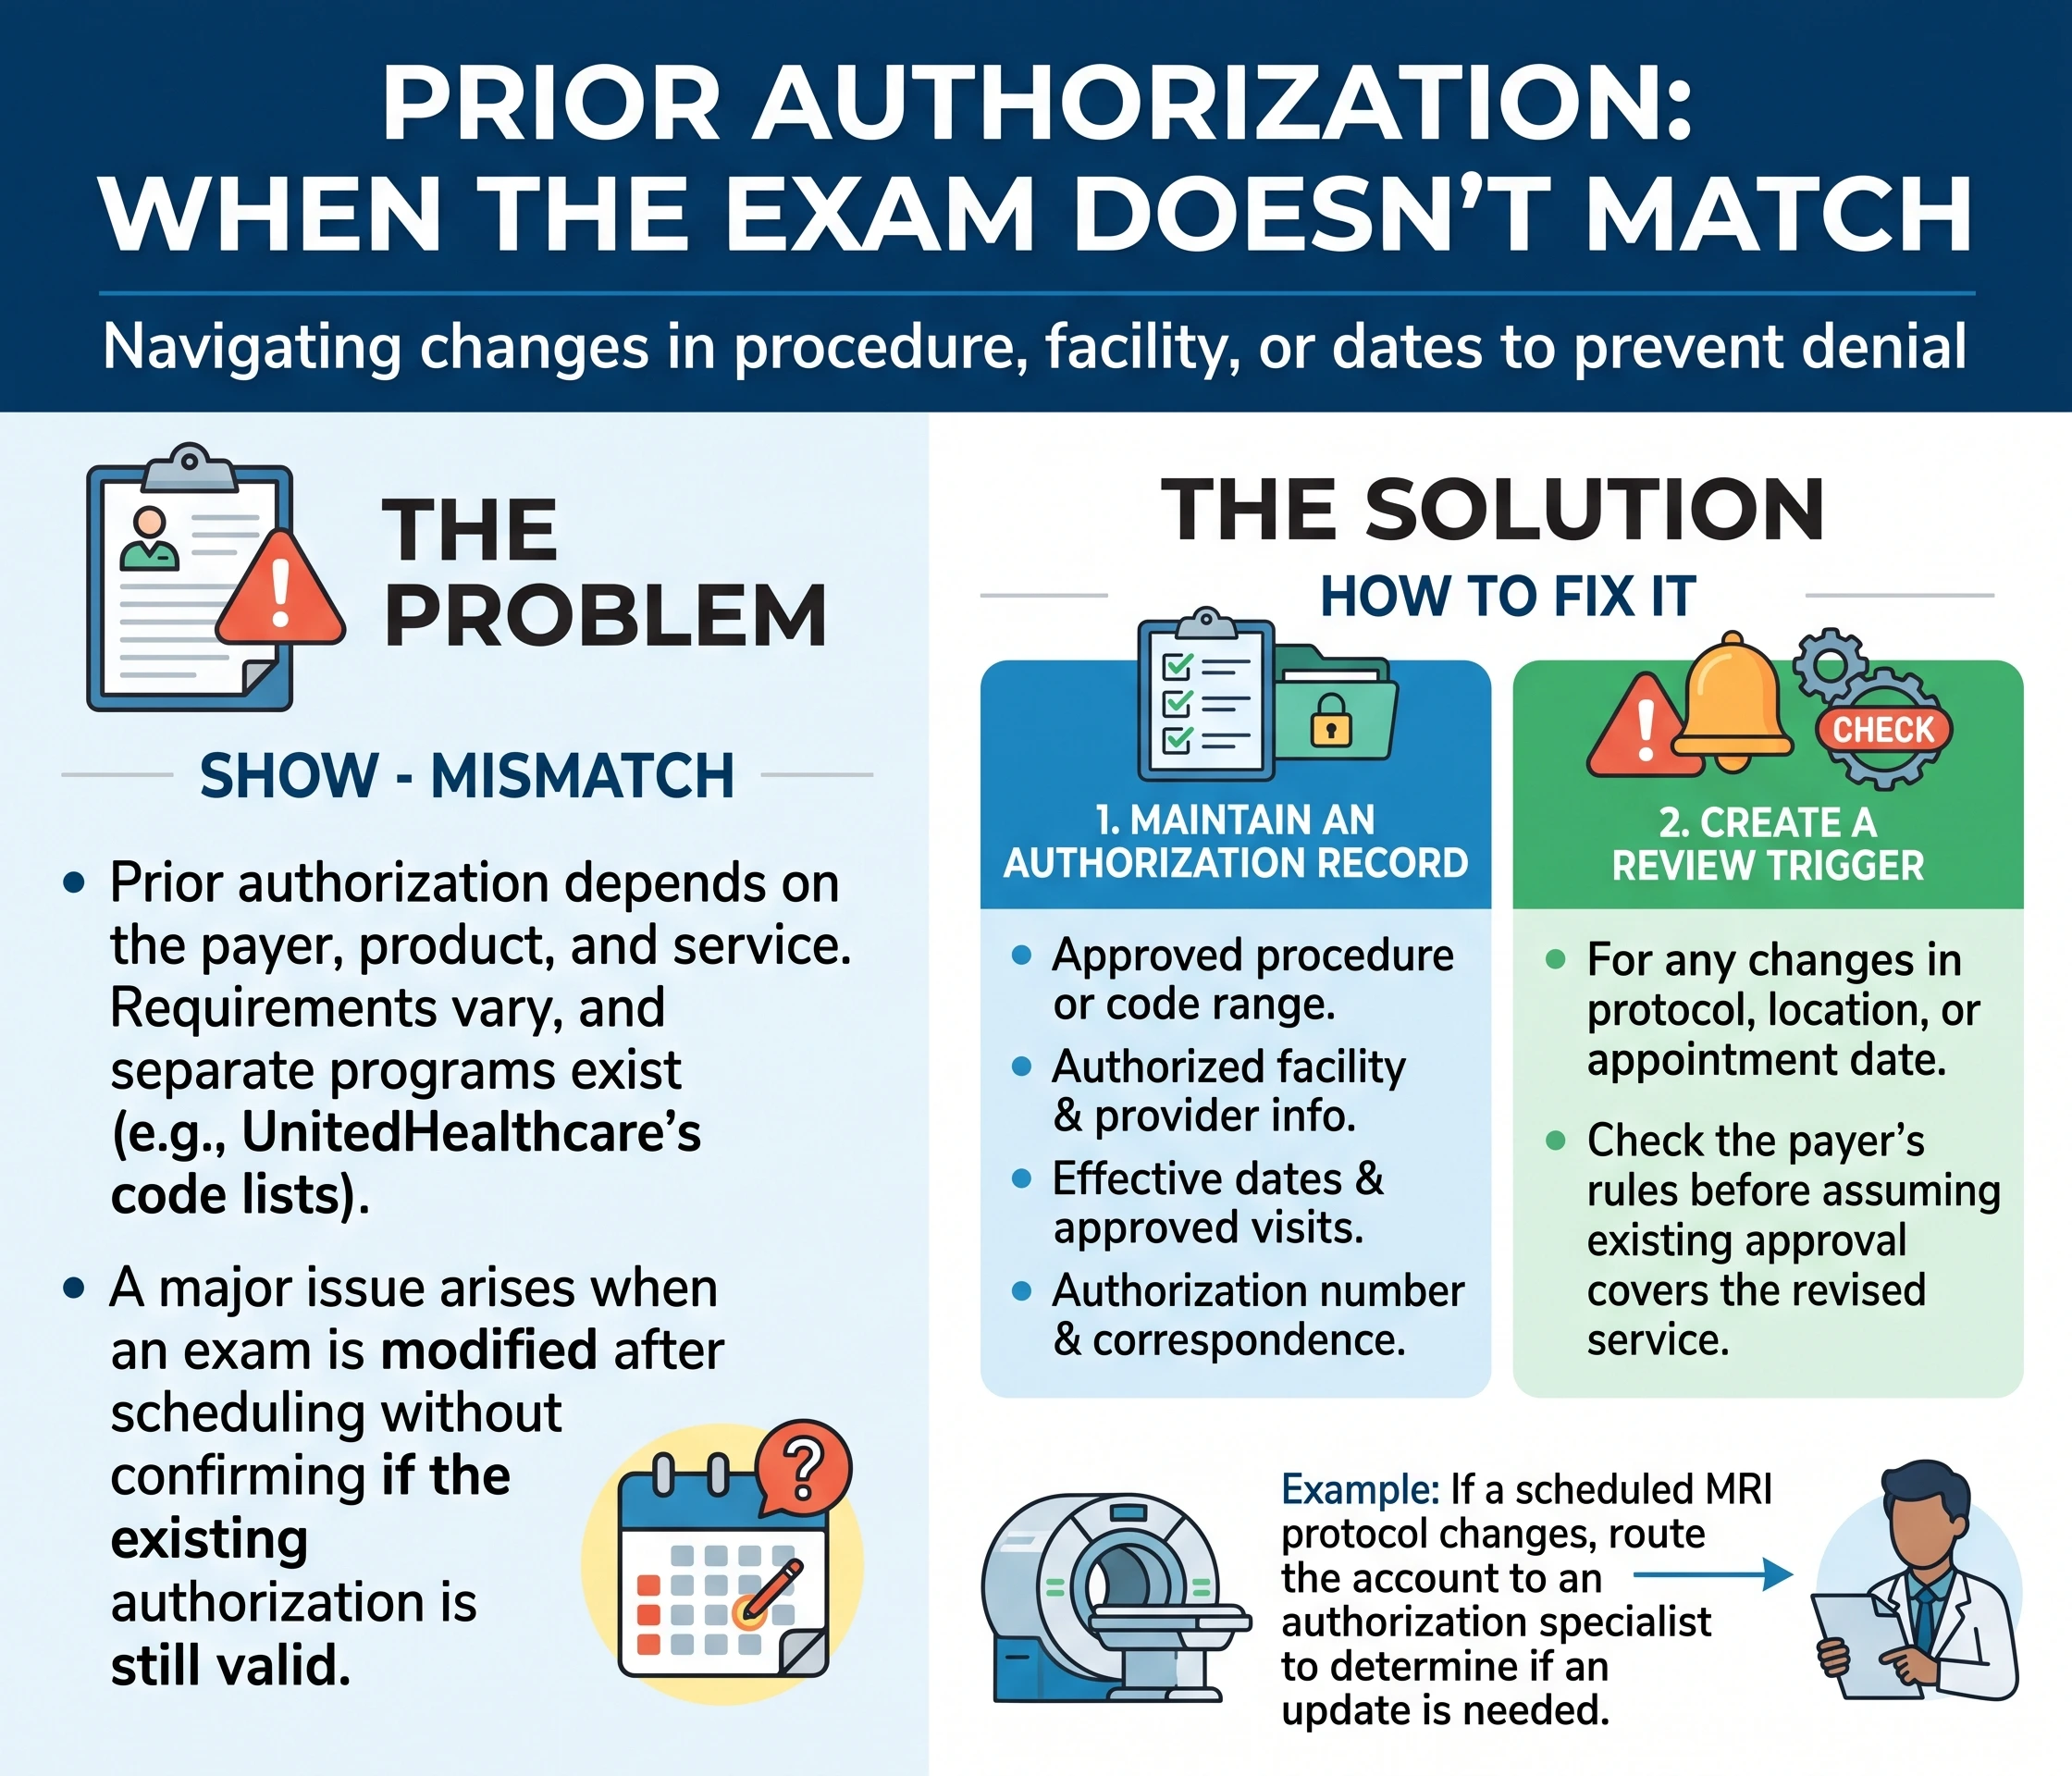
Prior authorization requirements depend on the payer, product, and service. UnitedHealthcare’s radiology resources, for example, publish separate program information and code lists rather than one universal requirement for every member. Its Medicare Advantage radiology FAQ also addresses changes to existing authorizations and communication between ordering and rendering professionals.
A potential issue occurs when an examination is modified after scheduling without verifying whether the existing authorization remains valid.
How to fix it
Maintain an authorization record containing:
- Approved procedure or code range.
- Authorized facility and applicable provider information.
- Effective dates and approved visits or units.
- Authorization number and supporting correspondence.
Create a review trigger for changes in protocol, location, or appointment date. Check the payer’s rules before assuming that an existing approval covers the revised service.
For example, if the scheduled MRI protocol changes, route the account to the authorization specialist to determine whether an update is necessary. This is a workflow example, not a rule that every protocol change requires new approval.
3. Incorrect professional and technical component billing
Some radiology services have separately billable professional and technical components. The professional component covers physician interpretation and reporting; the technical component covers the technical portion of the examination.
Noridian’s modifier 26 guidance, updated May 9, 2025, explains professional component reporting. CMS’s Physician Fee Schedule indicators identify whether a code supports component billing. Modifiers 26 and TC do not apply to every procedure code.
How to fix it
Build billing rules around the service arrangement and setting.
Billing situation | Review before submitting |
Interpretation only | Confirm that modifier 26 is appropriate for the code and service |
Technical service only | Verify technical component eligibility and the applicable claim format |
Both components | Confirm entitlement to bill the complete service |
Hospital-based service | Check facility payment rules and the physician’s separately reportable work |
Do not apply an independent imaging center’s claim configuration to hospital services without review. CMS specifically identifies restrictions on separate carrier payment for radiology technical components furnished during an inpatient stay.
4. Diagnosis coding that overstates the findings
Outpatient radiology coding requires care when the order contains a suspected condition. A referral for “rule out fracture” does not establish a confirmed fracture.
The FY 2027 ICD-10-CM Official Guidelines for Coding and Reporting, effective October 1, 2026, prohibit coding uncertain outpatient diagnoses as established conditions. For interpreted diagnostic tests, confirmed diagnoses documented in an available final report should be coded according to the guidelines.
How to fix it
Review the clinical indication alongside the final interpretation. If no definitive diagnosis is established, use the documented symptoms, findings, or other appropriate reason for the examination under outpatient rules.
Never replace the documented diagnosis with a covered condition simply to obtain payment.
CPT and ICD-10 code validation should also check the version applicable to the service date. CDC specifies that FY 2027 ICD-10-CM codes apply to services from October 1, 2026, through September 30, 2027.
5. Procedure coding and bundling mistakes
Radiology CPT codes distinguish services by details such as anatomy, examination extent, and contrast use. Selecting a code from the appointment label without reconciling the completed study creates an avoidable discrepancy.
CMS’s 2026 Medicare NCCI Policy Manual, Chapter IX, revised January 1, 2026, requires reporting the procedure performed with the greatest supported specificity. It also prohibits reporting multiple codes when a single code describes the services.
How to fix it
Compare the order, technical documentation, and final report before releasing questionable charges. Send inconsistencies for clarification rather than guessing which record is correct.
Review bundling edits against the actual clinical circumstances. For example, the same NCCI chapter states that a CT scan used for localization with specified PET services is not separately reportable. It also limits separate reporting of imaging guidance already included in another service.
Do not add a distinct-service modifier merely because software flags an edit. Require documented support and an applicable coding exception.
6. Unbilled examinations and delayed charge release
Denial reports cannot flag an examination that was never entered into the claims system. A useful control is to reconcile completed studies with final reports and billing records.
How to fix it
Use an examination identifier, such as the accession number, to compare:
- Completed examinations.
- Finalized interpretations.
- Released charges.
- Submitted claims and acknowledgments.
Investigate exceptions separately. A completed examination awaiting a report needs a different response from a finalized report whose charge failed to transfer.
Track canceled studies and corrected records as well, so reconciliation does not generate inappropriate duplicate charges. This approach gives managers visibility into work before it becomes aged accounts receivable.
7. Repeated submissions without resolving the denial
Before resubmitting a radiology claim, determine whether it was rejected before adjudication, denied after processing, or paid incorrectly. Review both the transaction response and the payer’s instructions.
CMS’s payment and remittance guidance explains that claim adjustment reason codes and remittance advice remark codes communicate payment adjustments and related explanations. Read the codes together with the claim details.
How to fix it
Choose the response that addresses the actual problem:
Finding | Appropriate next step |
Invalid submitted data | Correct the error and follow the applicable submission process |
Incorrect information on an adjudicated claim | Check the payer’s corrected-claim requirements |
Disputed coverage decision | Prepare an appeal supported by records and policy |
Apparent duplicate | Locate the original claim and review its status |
Track submission and appeal deadlines independently. CMS’s Medicare billing training states that claims generally must reach the correct contractor within one calendar year after the service date, subject to limited exceptions. Commercial payer deadlines require separate verification.
8. Underpayments hidden by routine payment posting
A paid claim still deserves review. Radiology underpayment identification requires comparing the adjudicated allowance with the expected allowance under the applicable contract.
How to fix it
Configure payment review by payer, procedure, modifier, location, and contract effective date. Separate insurer payment from patient responsibility and contractual adjustments.
Consider a hypothetical account with a $120 expected allowance, an $80 insurer payment, and $40 assigned to the deductible. Those figures alone do not establish an underpayment. The comparison must include the entire adjudication.
Place unexplained differences in an exception queue instead of automatically writing them off. For radiology payment posting, retain the remittance detail and reconcile posted payments with deposits; CMS describes the electronic remittance advice as the explanation of claim payment and adjustment activity.
9. Patient balances released without adequate review
Before sending a statement, verify that the balance represents valid patient responsibility. Review payer processing, contractual obligations, and applicable billing protections.
CMS’s No Surprises Act guidance explains that radiology is an ancillary service for which the notice-and-consent exception is unavailable in covered non-emergency situations at participating facilities. A routine consent form does not waive those protections.
How to fix it
Route disputed or unexplained balances for review before collection activity. Patient statements should identify the examination, service date, insurance processing, and the reason an amount remains due.
Measure whether the fixes are working
Use consistent internal definitions to track first-submission denials, authorization discrepancies, unbilled completed studies, unresolved underpayments, and accounts approaching filing deadlines. Separate results by payer and modality to identify where corrective work belongs.
The common challenges in radiology medical billing require controls at specific points: documentation review before coding, authorization reconciliation after changes, component validation before submission, and allowance verification after payment. Assign each exception an owner and measure whether the same error returns.