


Medical billers and coders face specific compliance requirements when processing upper gastrointestinal procedures. CPT Code 43239 represents an upper gastrointestinal endoscopy (EGD) that includes the esophagus, stomach, and duodenum or jejunum, accompanied by a biopsy. Proper reimbursement for this procedure depends on precise modifier application, correct diagnosis linking, and strict adherence to National Correct Coding Initiative (NCCI) edits.
What is CPT code 43239?
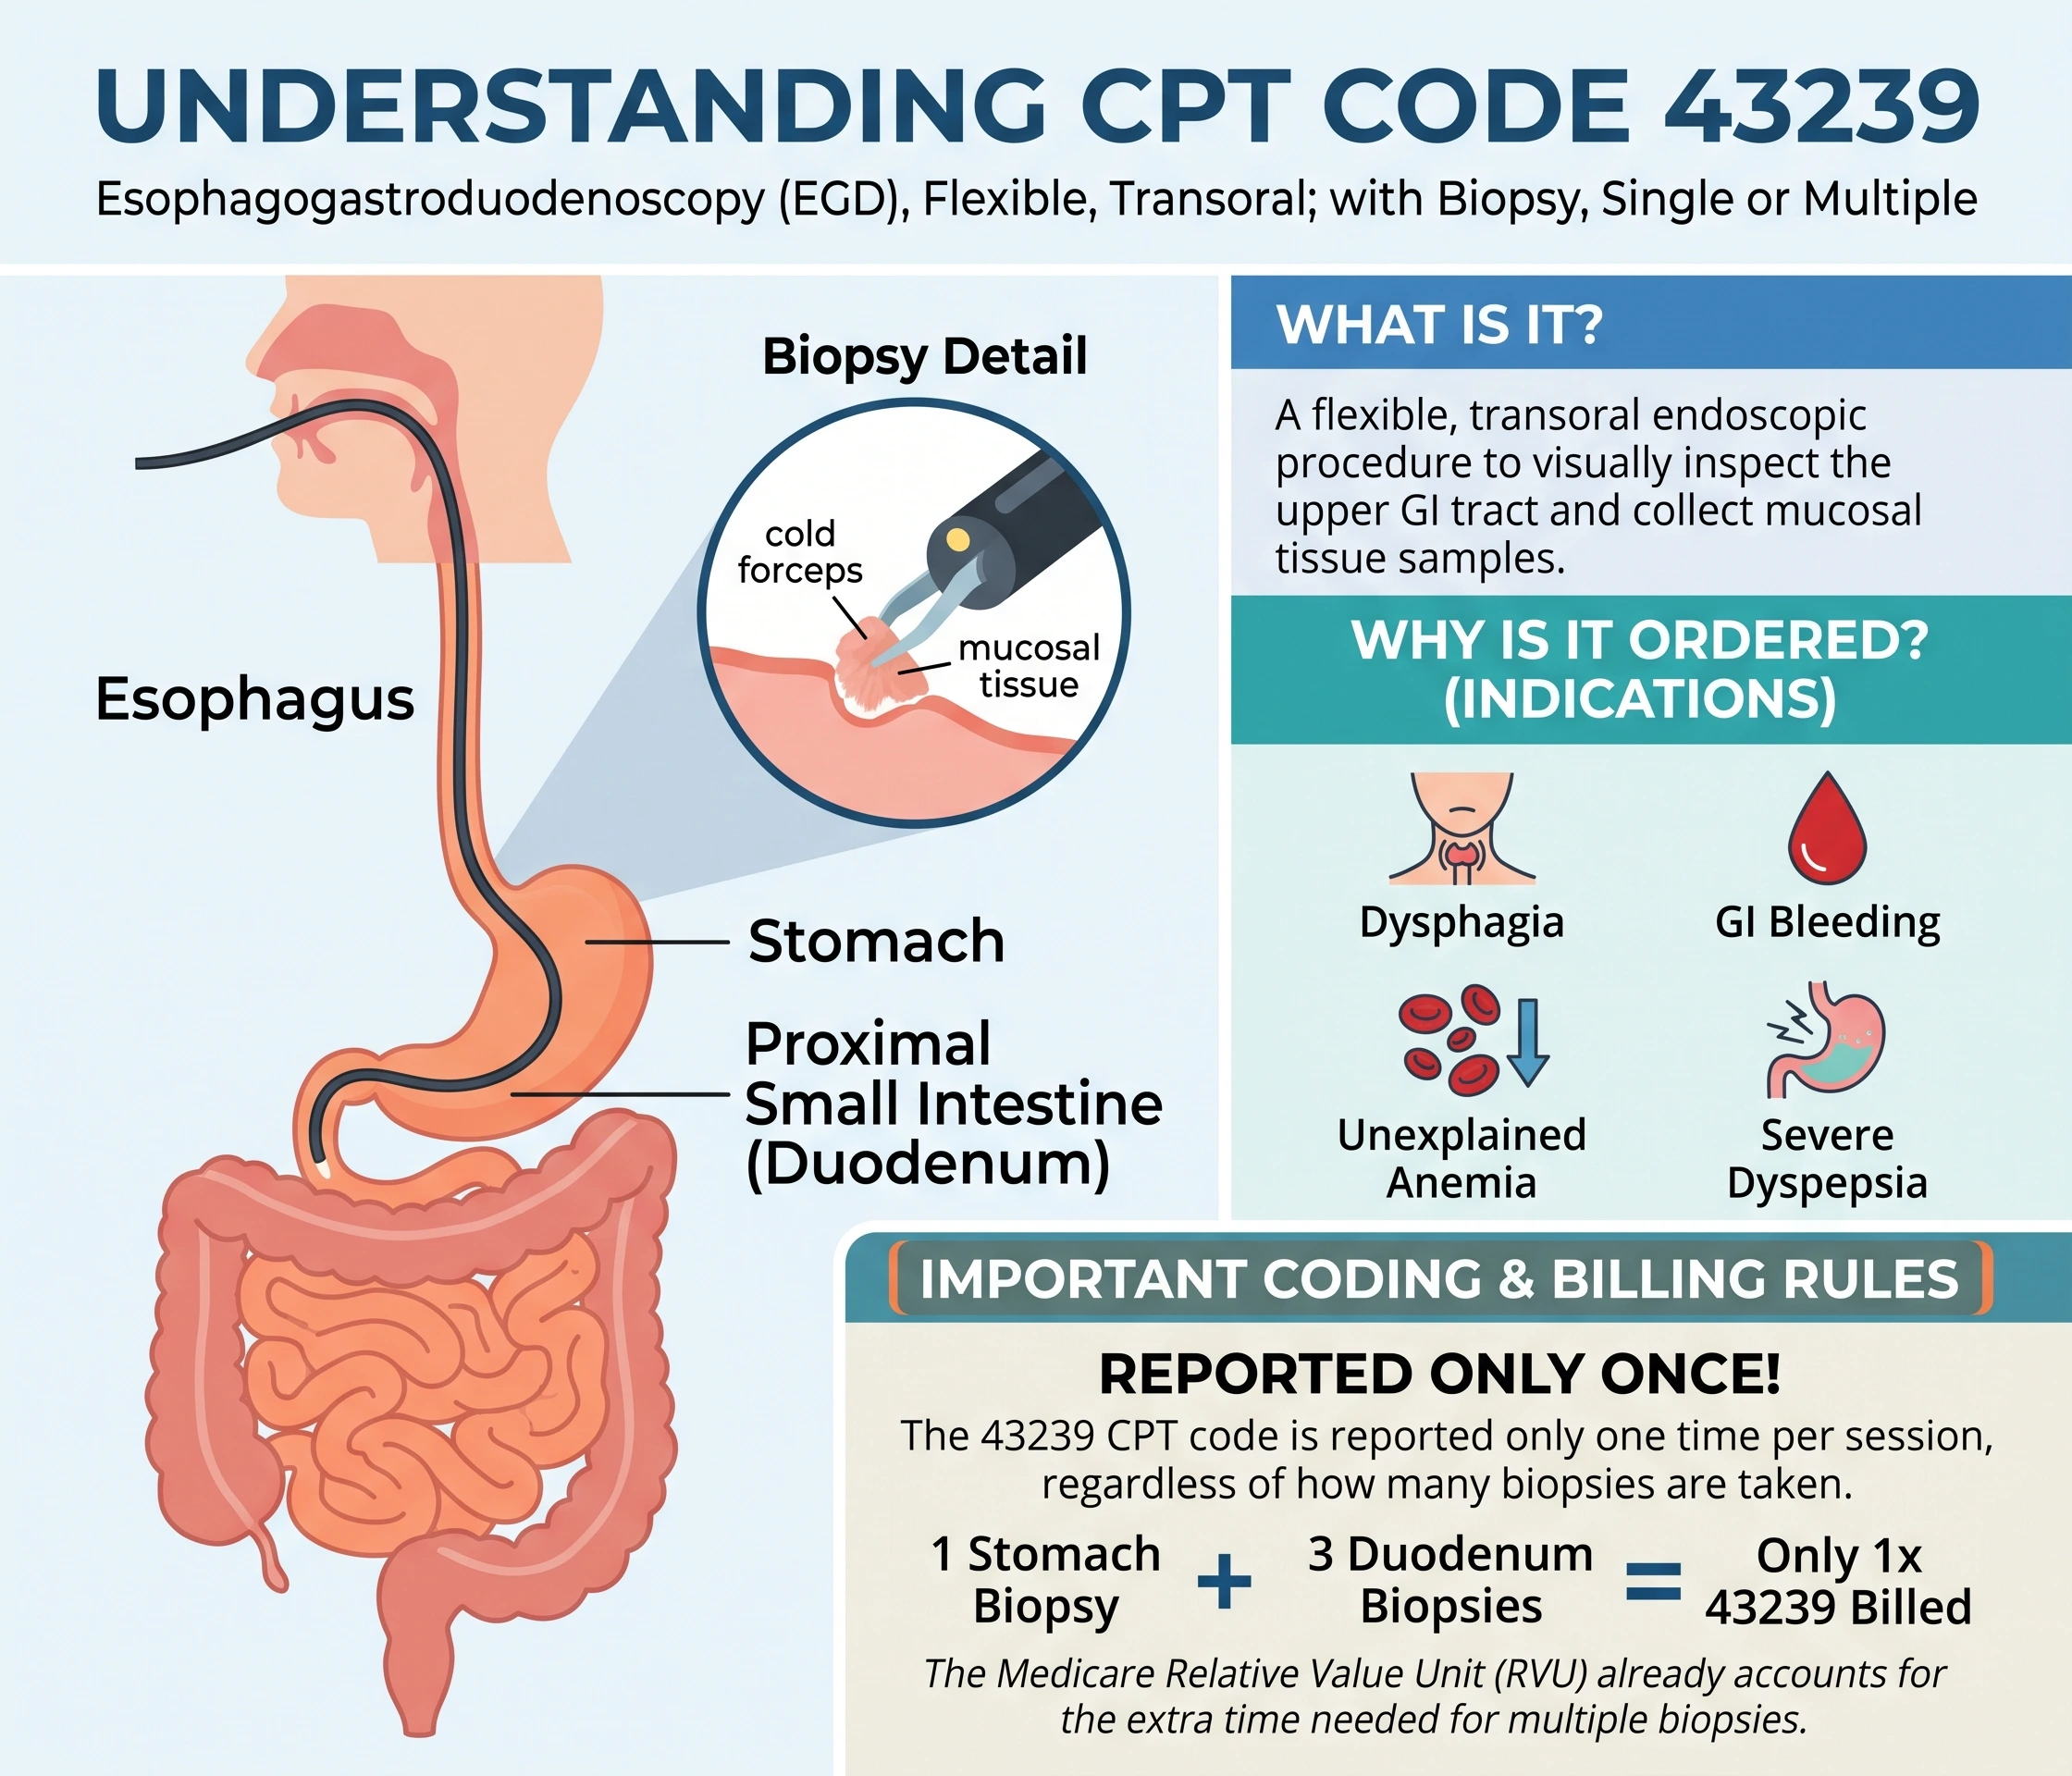
The American Medical Association (AMA) created the 43239 procedure code to categorize a specific surgical endoscopy. The official CPT code 43239 description defines it as an esophagogastroduodenoscopy, flexible, transoral; with biopsy, single or multiple.
Physicians perform this procedure to visually inspect the upper gastrointestinal tract and collect mucosal tissue samples. The endoscope passes through the mouth. It travels down the esophagus, enters the stomach, and continues into the proximal small intestine. Providers order this intervention to evaluate persistent symptoms such as dysphagia, gastrointestinal bleeding, unexplained iron deficiency anemia, or severe dyspepsia.
A biopsy involves passing cold forceps through the working channel of the endoscope to grasp and tear a small piece of tissue. If a physician performs multiple biopsies during the same endoscopic session, the 43239 CPT code is reported only once. The AMA guidelines explicitly state that this code covers all biopsies taken during the encounter. A provider taking one biopsy from the gastric antrum and three biopsies from the duodenum bills 43239 one time. The Relative Value Unit (RVU) assigned by Medicare accounts for the extra time required to perform multiple biopsies during a single session.
CPT 43239 global period explained
The Centers for Medicare and Medicaid Services (CMS) assigns a zero-day global period to CPT code 43239. The standard global period for 43239 dictates that the surgical package covers the day of the procedure itself. All routine pre-operative preparation, the intra-operative procedure, and standard post-operative recovery care provided on the day of the endoscopy are included in the base reimbursement fee.
This classification impacts how medical practices bill for follow-up care. If a patient returns the following day for an evaluation and management (E/M) visit related to the procedure, providers can bill for that visit separately. No global period modifier is required for E/M services performed on subsequent days. For example, if a patient presents to the clinic 48 hours after a biopsy to discuss pathology results and initiate a treatment regimen for a Helicobacter pylori infection, the provider bills a standard established patient office visit code.
CPT 43239 modifier rules
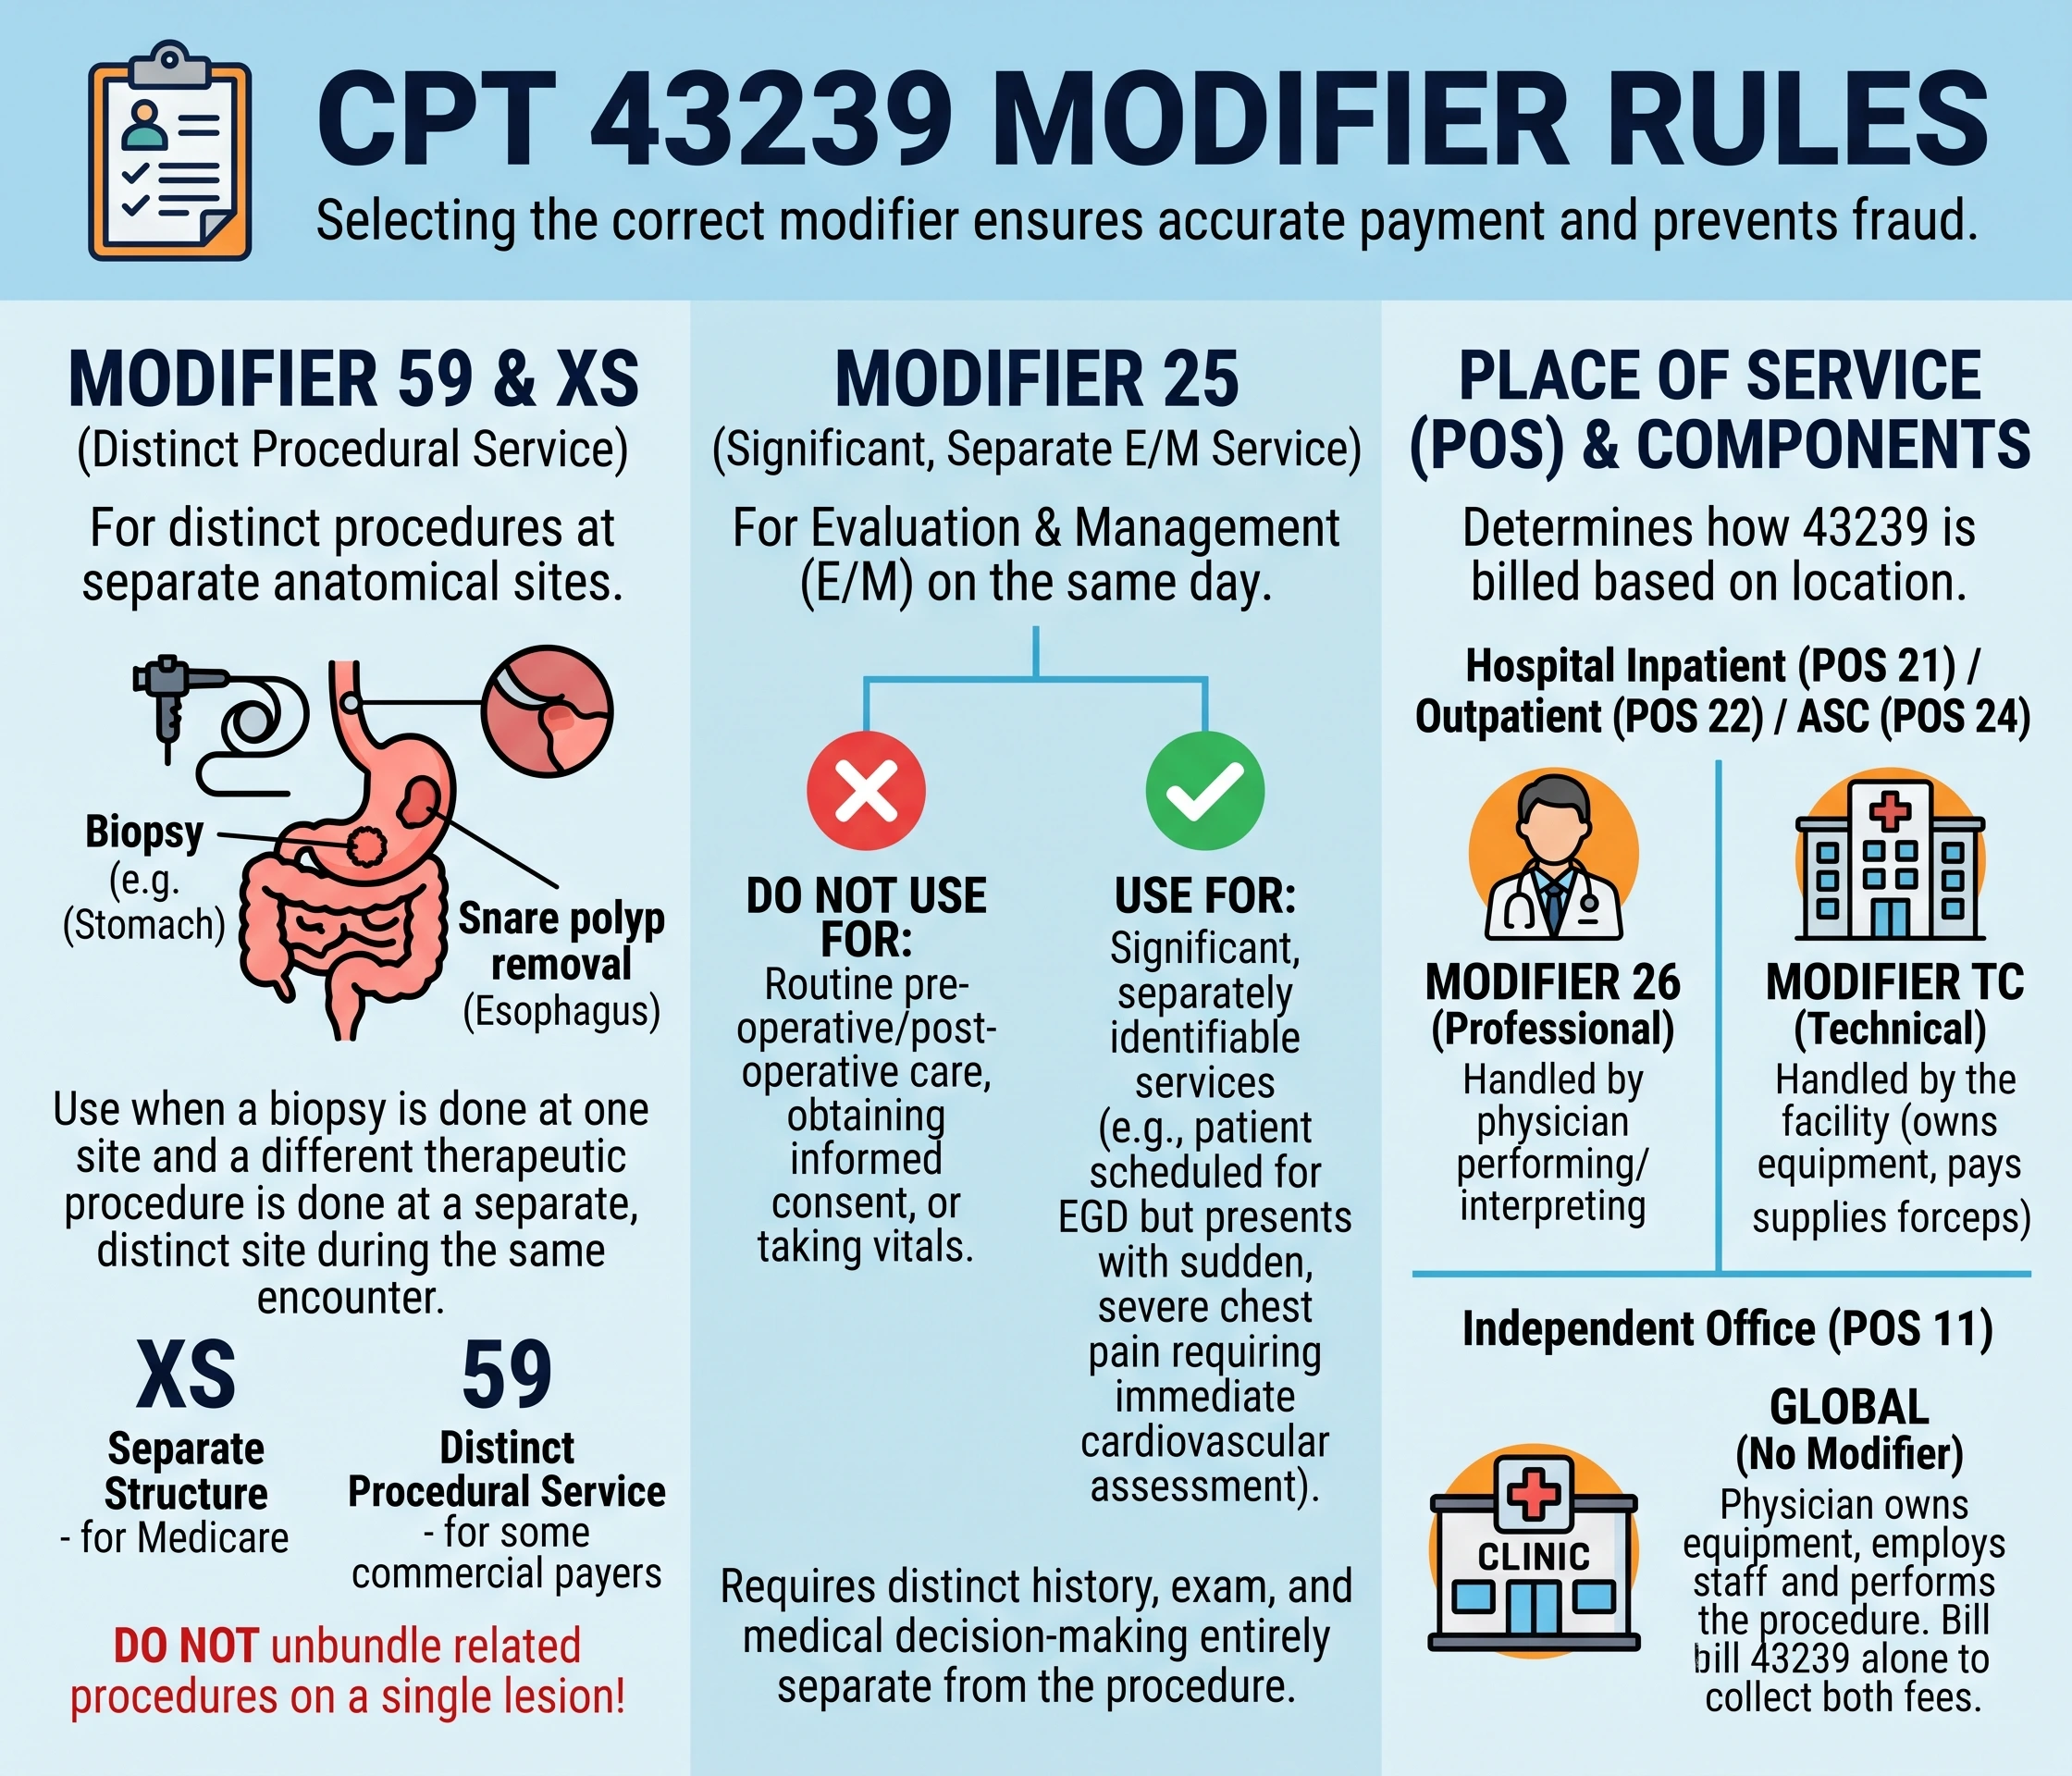
Selecting the correct modifier for CPT 43239 ensures accurate payment and prevents fraud investigations. Medical coders must append 43239 modifiers to clarify the clinical circumstances of the procedure without altering the primary code’s anatomical definition.
Modifier 59 with 43239
Modifier 59 indicates a distinct procedural service. Coders use modifier 59 with 43239 when a provider performs a biopsy on one site and a different therapeutic procedure on a separate, distinct anatomical site during the exact same encounter. The CMS NCCI Policy Manual for Medicare Services forbids unbundling related procedures on a single lesion.
CMS established the X-modifiers (XE, XS, XP, XU) to provide greater documentation specificity than modifier 59. When submitting claims to Medicare, coders should use modifier XS (Separate Structure) instead of 59 if the physician biopsies a lesion in the stomach and uses a snare technique to remove a polyp in the esophagus. Commercial payers vary on their acceptance of X-modifiers, and some still require the traditional modifier 59.
Modifier 25 with 43239
Billing departments frequently ask how to correctly report an E/M service on the same day as an endoscopy. Modifier 25 applies to a significant, separately identifiable evaluation and management service performed by the same physician on the same day as the procedure. The medical record must prove that the E/M service went beyond the standard pre-operative and post-operative care associated with the endoscopy.
If a patient is scheduled for a routine EGD biopsy, the provider cannot bill an E/M service simply for obtaining informed consent and taking vitals. If a patient scheduled for an EGD presents with sudden, severe chest pain requiring an immediate cardiovascular assessment prior to sedation, the provider can bill the appropriate E/M code with modifier 25 attached. The documentation must feature a distinct history, exam, and medical decision-making process completely separate from the gastrointestinal complaint.
Place of service modifiers
Reimbursement for a gastrointestinal endoscopy depends heavily on the Place of Service (POS) code. Providers must distinguish between the professional component and the technical component when billing CPT 43239.
Modifier 26 designates the professional component. It indicates that the physician only performed the physical procedure and interpreted the visual findings. Coders append modifier 26 to 43239 when the physician performs the endoscopy in a hospital inpatient setting (POS 21), a hospital outpatient department (POS 22), or an ambulatory surgical center (POS 24).
In these settings, the facility owns the endoscopic equipment, purchases the biopsy forceps, and pays the nursing staff. The facility submits a separate claim for the technical component using modifier TC. This covers the overhead costs associated with operating the procedure room. If a gastroenterologist owns their equipment, employs the staff, and performs the procedure in an independent, office-based endoscopy suite (POS 11), they bill the code without either modifier. This indicates a global service, allowing the physician to collect both the professional and technical reimbursement fees.
Comparing upper GI endoscopy codes
Billing multiple endoscopy codes requires strict adherence to NCCI edits. The structure of the CPT manual organizes endoscopy codes in a hierarchical family, with diagnostic procedures acting as the foundation.
43235 vs 43239
Code 43235 represents a diagnostic esophagogastroduodenoscopy without a biopsy. When evaluating CPT 43235 and 43239, coders must recognize that a biopsy inherently includes the diagnostic visualization of the tract. NCCI edits bundle 43235 into 43239. You cannot bill both codes for the same session. If a provider starts a diagnostic EGD (43235), observes an area of suspected mucosal metaplasia, and takes a biopsy, the entire procedure converts to 43239.
Can 43239 and 43251 be billed together?
CPT code 43251 describes an EGD with the removal of a tumor, polyp, or other lesion by snare technique. According to chapter six of the CMS NCCI Policy Manual, providers can bill 43239 and 43251 together only if the procedures occur at distinct anatomical sites or involve physically separate lesions.
If a physician biopsies a polyp with forceps and then immediately removes that exact same polyp using a snare technique, only the snare removal (43251) is billed. Billing a biopsy and a removal for the exact same lesion constitutes unbundling. The biopsy is considered a necessary preliminary step to the complete removal.
If the physician biopsies an ulcerated lesion in the duodenal bulb and uses a snare to remove a polyp in the gastric body, both codes apply. In this scenario, the coder appends modifier 59 or XS to the 43239 code to clear the NCCI edit. This signals to the claims processor that the biopsy occurred at a separate site from the snare removal.
CPT Code | Procedure Description | NCCI Bundling Status |
43235 | Diagnostic EGD (inspection only) | Bundled into 43239 and 43251 |
43239 | EGD with single or multiple biopsies | Bundled into 43251 if performed on the exact same lesion |
43251 | EGD with snare removal of lesion | Primary code when performed on the same lesion as a biopsy |
CPT 43239 documentation requirements
Submitting CPT 43239 clean claims requires strict adherence to payer policies. The physician’s operative report must align directly with the billed codes. According to guidelines published by the American Society for Gastrointestinal Endoscopy (ASGE) in 2023, high-quality endoscopy reports must document specific procedural elements.
The documentation must explicitly state the clinical indications for the procedure. It must detail the exact anatomical landmarks visualized, including the gastroesophageal (GE) junction and the Z-line. The provider must record the specific sites biopsied, the number of specimens retrieved, and the exact instrument used.
Failure to describe the biopsy technique triggers audits. If the report states “polyp removed” without specifying whether cold forceps or a hot snare was used, a coder cannot determine whether to assign 43239 or 43251.
CPT 43239 medical necessity
Establishing medical necessity requires an appropriate ICD-10 diagnosis code. Local Coverage Determinations (LCDs) published by Medicare Administrative Contractors outline which diagnoses justify upper endoscopies. Acceptable diagnoses typically include K21.00 (Gastro-esophageal reflux disease with esophagitis, without bleeding), D50.0 (Iron deficiency anemia secondary to blood loss), or R13.10 (Dysphagia, unspecified). Claims submitted with non-covered diagnosis codes face immediate rejection.
Common CPT 43239 denial reasons
Medical practices lose revenue when endoscopy claims fail initial processing. The Office of Inspector General (OIG) regularly audits gastrointestinal billing for upcoding and unbundling errors. Understanding common CPT 43239 denial categories allows practice managers to correct workflows before billing.
Missing CPT 43239 authorization
Many commercial health maintenance organizations (HMOs) and Medicare Advantage plans require prior authorization for elective EGD procedures. Performing the biopsy without securing this approval results in a CPT 43239 denial. Insurance verification teams must secure this authorization before the patient enters the procedure room.
Invalid modifier usage
Applying modifier 59 to bypass an NCCI edit without supporting documentation in the operative report triggers audits. Payers employ automated claims software to flag instances where 43239 and 43251 are billed together frequently by the same provider. If a retrospective review reveals that the provider biopsied and removed the same lesion, the payer will demand a refund for the overpayment.
Incomplete anatomic descriptions
Payer policies require alignment between the clinical report and the pathology report. If the pathology report mentions tissue from the esophagus but the endoscopy report fails to document an esophageal biopsy, the payer will deny the claim due to conflicting records. The physician must amend the operative note to reflect the actual physical procedure performed.
Exceeding frequency limits
Certain commercial payers limit how often a patient can undergo upper GI endoscopies for surveillance purposes. Guidelines from the American College of Gastroenterology state that patients with Barrett’s esophagus without dysplasia require surveillance endoscopy every 3 to 5 years. Billing CPT 43239 billing for a patient with this history one year after their last clear endoscopy requires specific clinical justification in the medical record. Without documentation of new or worsening symptoms, the payer will deny the claim as not medically necessary.
Accurate coding for upper gastrointestinal procedures requires matching the physician’s exact technique to the CPT manual definitions. A single forceps biopsy changes a diagnostic EGD into a surgical CPT 43239 procedure. Applying NCCI edits correctly prevents unbundling, while appropriate modifier usage accurately describes complex encounters involving multiple lesions or separate evaluation and management services. By maintaining detailed operative reports and verifying medical necessity policies prior to the procedure, medical billers ensure compliance and secure exact reimbursement for endoscopic services.