


Medical billers, coders, and healthcare providers process thousands of ophthalmology claims annually. Proper reimbursement relies on exact medical coding. Understanding CPT code 92014 ensures accurate billing for eye care providers managing ongoing patient conditions. The American Medical Association (AMA) defines this service code 92014 as an ophthalmological service involving a medical examination and evaluation. It requires the initiation or continuation of a diagnostic and treatment program for an established patient. The evaluation must be a comprehensive ophthalmic examination.
Applying this procedure code 92014 requires adherence to specific clinical and administrative criteria. This guide explains what constitutes an established patient, details the examination components, compares similar codes, and outlines the documentation requirements necessary to prevent claim denials.
What is CPT 92014?
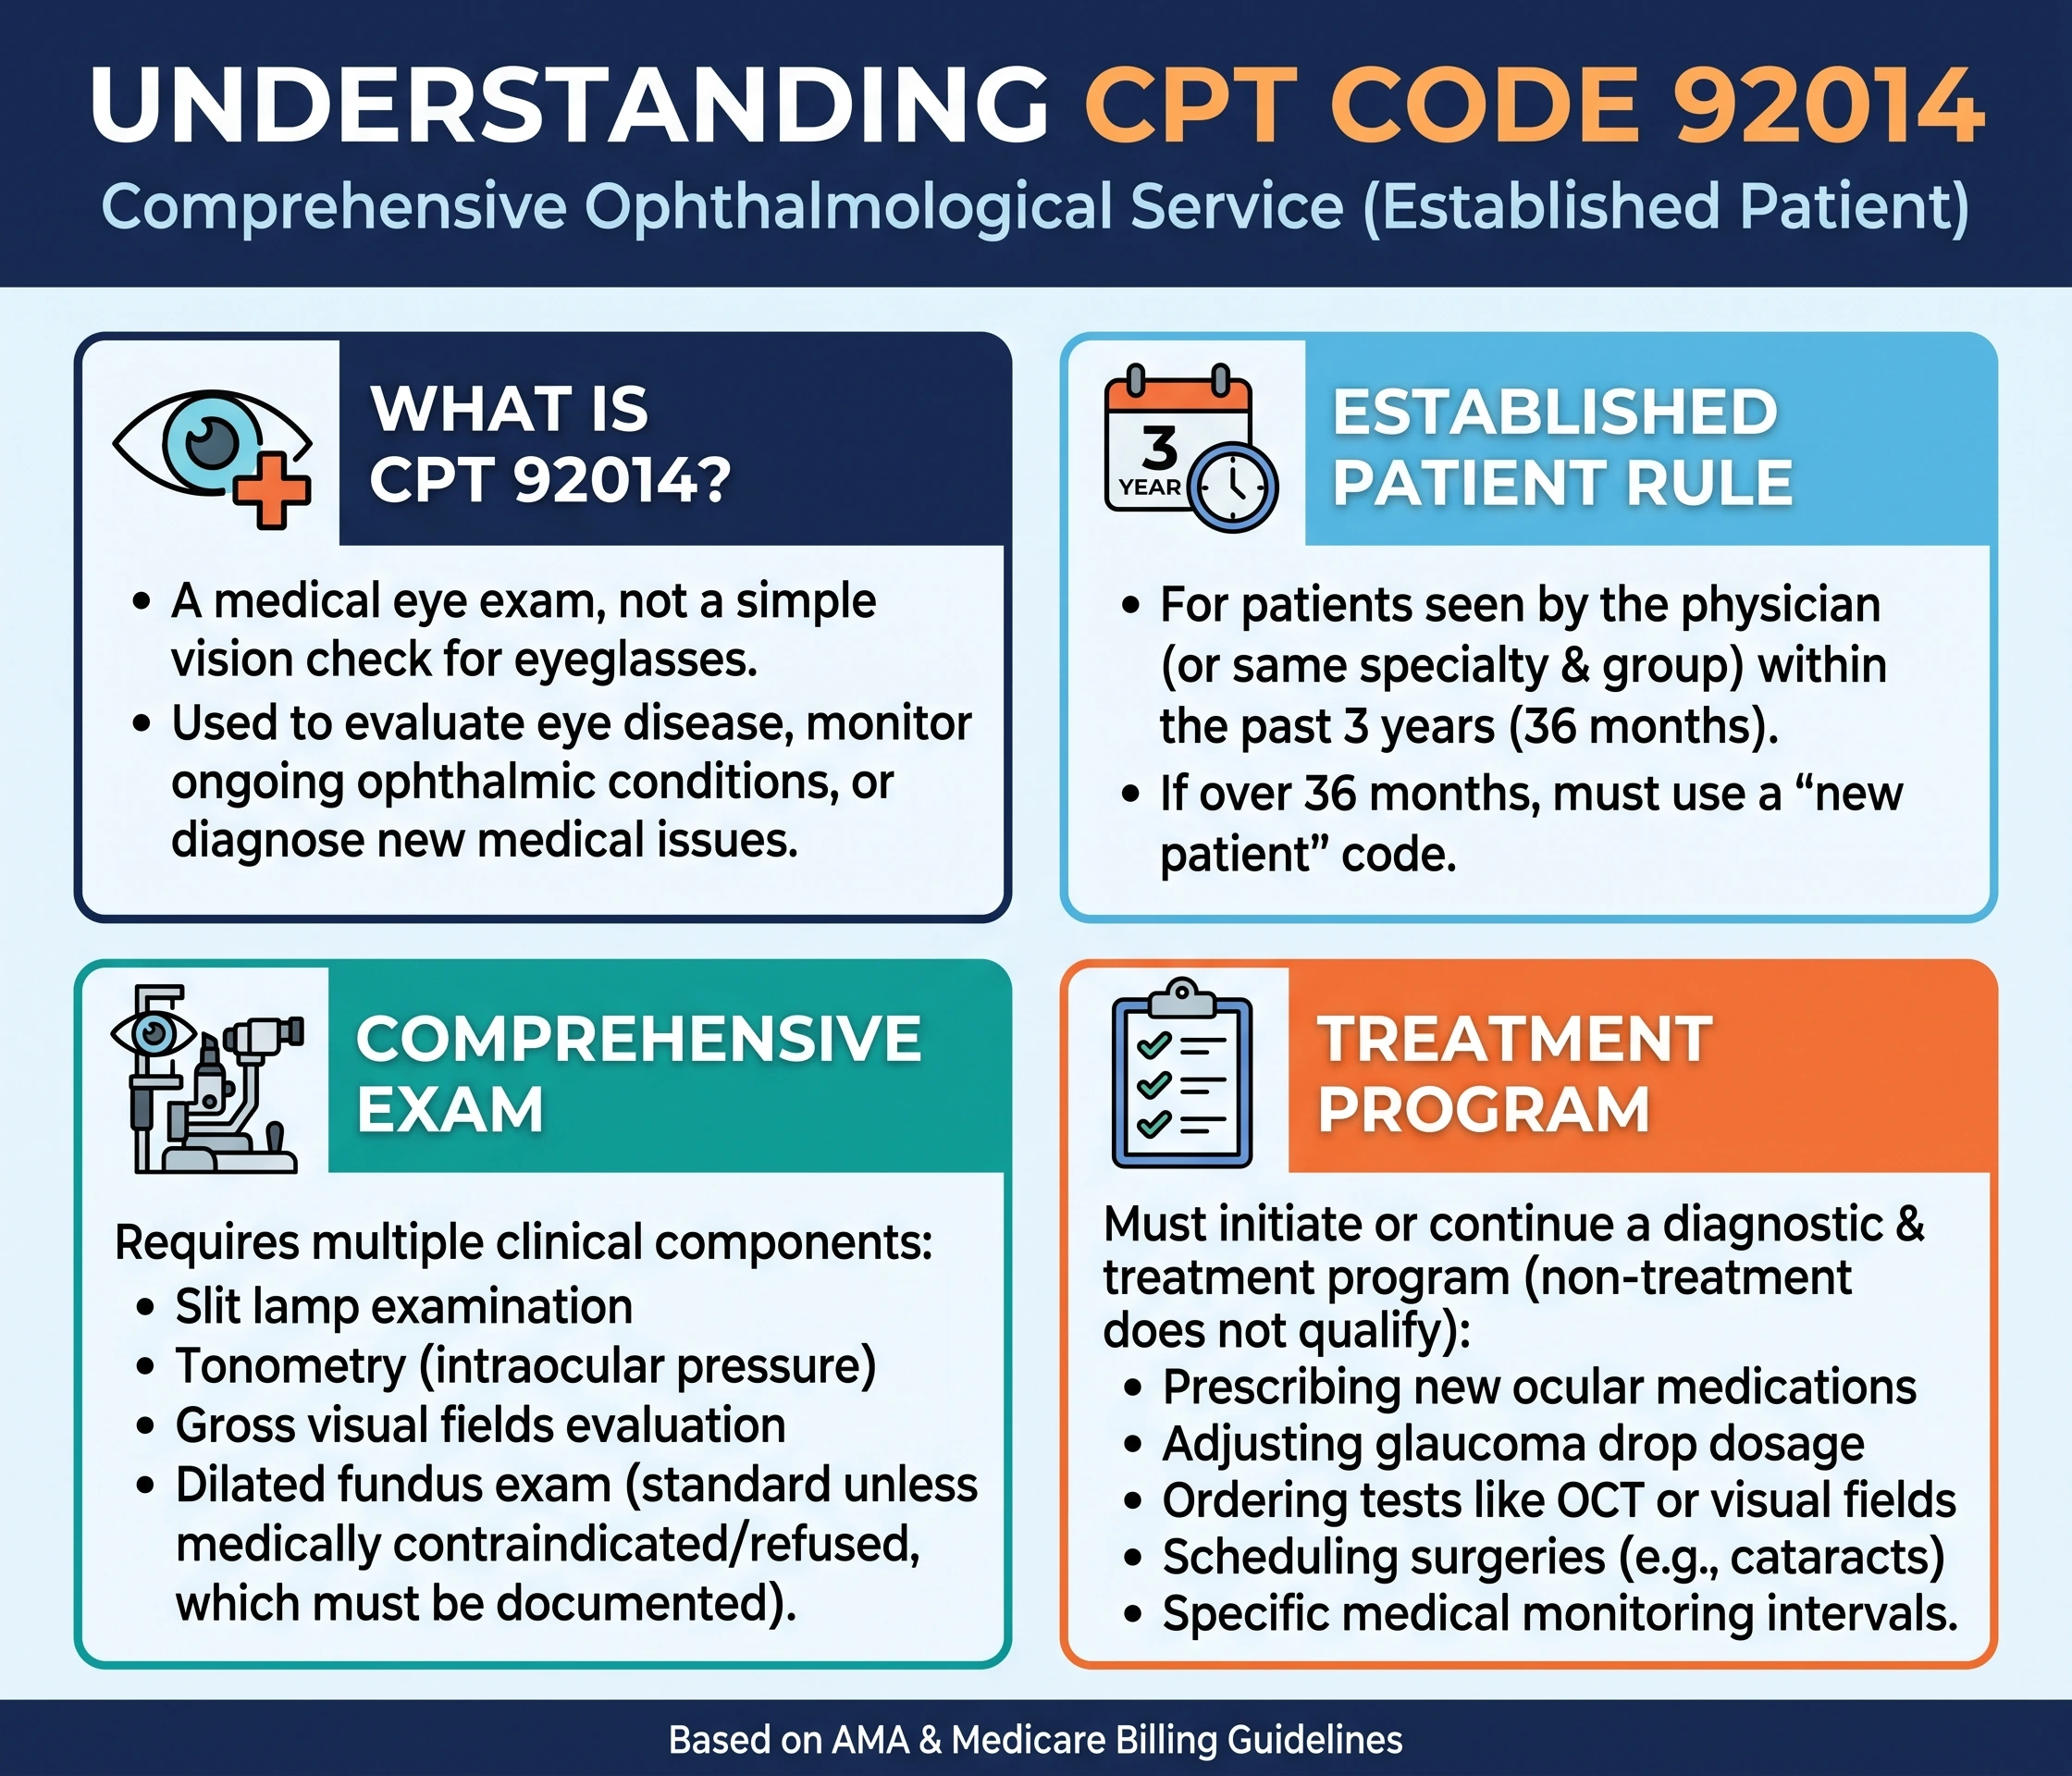
To answer what is CPT code 92014, coders must look at the official 92014 CPT code description provided by the AMA. The code represents a comprehensive ophthalmological service performed on an established patient. It includes a general evaluation of the complete visual system.
A 92014 eye exam is not a simple vision check for eyeglasses. It is a medical code 92014 used when a physician evaluates an eye disease, monitors an ongoing ophthalmic condition, or diagnoses a new medical issue within the visual system.
The established patient rule
CPT 92014 applies strictly to established patients. The AMA defines an established patient as someone who has received professional services from the physician, or another physician of the exact same specialty and subspecialty who belongs to the same group practice, within the past three years. If the patient has not been seen within this 36-month window, the provider must use a new patient code.
The comprehensive examination requirement
A comprehensive ophthalmologic examination evaluates the entire visual system. The 92014 code description mandates multiple clinical components. While the exact sequence varies based on clinical judgment, providers typically perform a slit lamp examination, tonometry to measure intraocular pressure, and an evaluation of the gross visual fields.
A dilated fundus examination is often a standard component. The dilated fundus exam CPT code guidelines indicate that dilation should be performed unless medically contraindicated. If a patient refuses dilation, or if dilation poses a risk (such as in patients with narrow angles), the provider must clearly document the reason for omitting this step to support the CPT code 92014 requirements.
Initiation or continuation of a treatment program
The most heavily audited component of CPT 92014 billing guidelines is the requirement to initiate or continue a diagnostic and treatment program. An examination without medical management does not qualify.
According to Medicare guidelines, acceptable documentation for a diagnostic and treatment program includes:
- Prescribing new ocular medications.
- Adjusting the dosage of existing eye drops for glaucoma.
- Ordering further diagnostic tests, such as optical coherence tomography (OCT) or visual field testing.
- Scheduling the patient for cataract surgery or laser trabeculoplasty.
- Recommending specific medical monitoring intervals for macular degeneration.
Writing “return to clinic in one year” without specifying a medical rationale for the ongoing monitoring often fails to meet this requirement during a payer audit.
Differentiating 92014 from other ophthalmology CPT codes
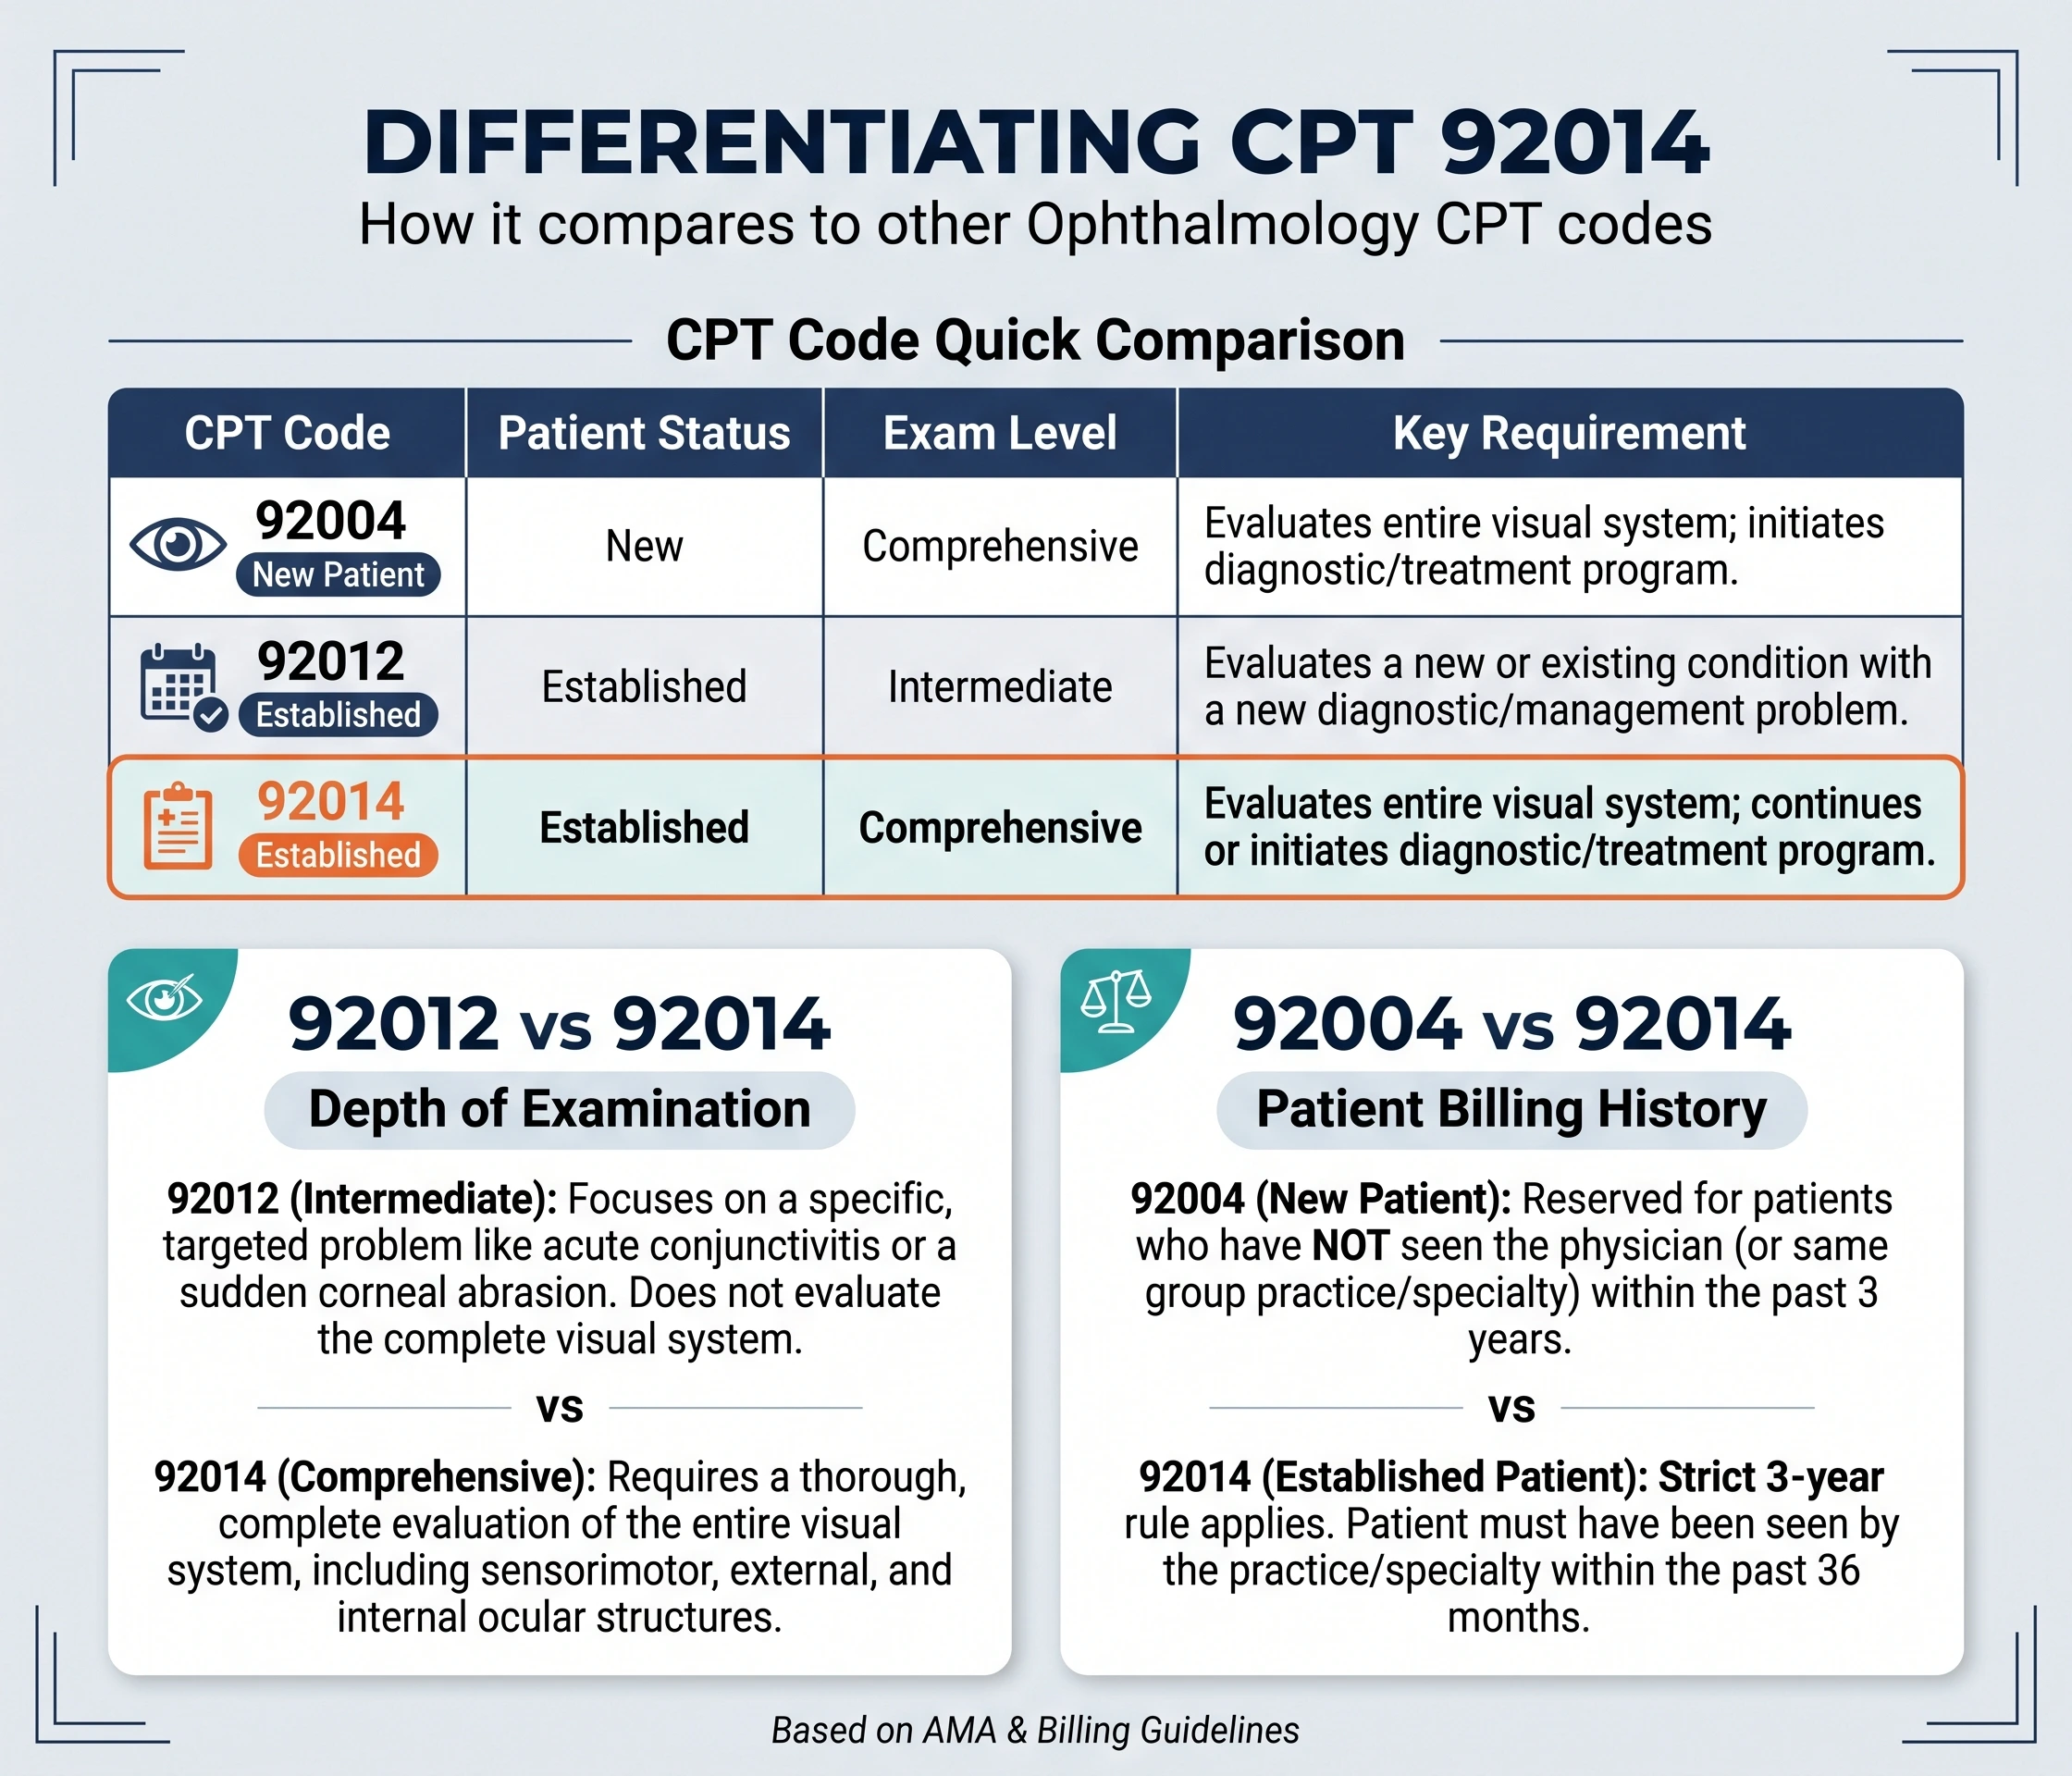
Medical coders frequently choose between several eye exam billing codes. Selecting the correct ophthalmology CPT codes depends on patient status and the scope of the evaluation.
CPT Code | Patient Status | Examination Level | Key Requirement |
92004 | New | Comprehensive | Evaluates the entire visual system; initiates a diagnostic/treatment program. |
92012 | Established | Intermediate | Evaluates a new or existing condition complicated by a new diagnostic/management problem. |
92014 | Established | Comprehensive | Evaluates the entire visual system; continues or initiates a diagnostic/treatment program. |
92012 vs 92014
The choice between 92012 vs 92014 centers on the depth of the examination. CPT 92012 is an intermediate service. A provider uses 92012 to evaluate a specific problem, such as acute conjunctivitis or a sudden corneal abrasion. It does not require an evaluation of the complete visual system. CPT 92014 requires a comprehensive evaluation of the basic sensorimotor system, the external eye, and the internal ocular structures.
92004 vs 92014
The distinction between 92004 vs 92014 relies entirely on the patient’s billing history. Both are comprehensive exams requiring medical management. CPT 92004 is billed for new patients, while CPT 92014 is reserved for established patients.
Handling refraction: Can 92014 and 92015 be billed together?
Refraction is the process of determining a patient’s prescription for eyeglasses or contact lenses. The AMA uses a separate code for this service. The 92015 CPT code description is defined as the determination of refractive state.
Coders frequently ask: can 92014 and 92015 be billed together? Yes, they can be billed on the same date of service. The CPT 92014 code covers the medical examination, while CPT 92015 covers the measurement of visual acuity and the optical prescription.
Providers must understand payer coverage rules regarding the refraction CPT code. The Centers for Medicare & Medicaid Services (CMS) strictly classifies CPT 92015 as a non-covered service under Section 1862(a)(7) of the Social Security Act. Medicare will reimburse the physician for the medical code 92014 if supported by a medical diagnosis, but the patient remains financially responsible for the 92015 charge. Ophthalmology practices should collect payment for CPT 92015 directly from Medicare beneficiaries at the time of service.
Commercial insurance policies vary. Some vision-specific plans cover both the comprehensive eye exam CPT code and the refraction, while standard medical plans often mirror Medicare rules.
Medical necessity and insurance coverage
Reimbursement for billing code 92014 depends on medical necessity documentation. Final CPT and ICD selections must align logically on the CMS-1500 claim form.
Medical vs. routine eye exams
A routine eye exam CPT code is typically submitted with a primary diagnosis of a routine vision check (such as ICD-10 code Z01.00 or Z01.01). Many medical insurance plans exclude routine care.
To secure payer coverage for the 92014 procedure code under a medical benefit, the provider must link the service to a medical diagnosis code. Common ICD-10 codes supporting medical necessity for an established patient eye exam include conditions such as primary open-angle glaucoma (H40.11-), age-related macular degeneration (H35.30), or age-related cataracts (H25.-).
Medicare billing rules
Medicare coverage for ophthalmologic examination codes requires strict adherence to Local Coverage Determinations (LCDs). Medicare contractors review claims to ensure the frequency of visits matches the severity of the patient’s condition. Billing 92014 every three months for stable, early-stage cataracts will likely trigger an audit, as the frequency exceeds standard clinical necessity. Monitoring advanced glaucoma with frequent medication adjustments justifies more frequent comprehensive evaluations.
92014 documentation requirements
Accurate ophthalmology coding requires a detailed documentation checklist. Auditors review medical records to confirm the provider performed and recorded all mandatory elements of the CPT 92014 description.
The medical record must include:
- Chief complaint: A clear medical reason for the visit.
- History: An updated review of the patient’s medical and ocular history.
- General medical observation: Notes on the patient’s orientation and physical state.
- Visual acuity: Documented in both eyes.
- External examination: Evaluation of the eyelids, lashes, and lacrimal apparatus.
- Basic sensorimotor examination: Assessment of ocular motility and alignment.
- Slit lamp examination CPT code components: Detailed findings of the cornea, anterior chamber, iris, and lens.
- Ophthalmoscopy: Evaluation of the optic nerve, macula, and peripheral retina.
- Intraocular pressure: Tonometry readings.
- Medical management: Specific details regarding the diagnostic and treatment program.
If a physician cannot complete a specific component due to physical limitations (such as a patient in a wheelchair unable to reach the slit lamp), the chart must document the limitation.
Claim denial prevention and claim submission
Claim denial disrupts cash flow and creates administrative burdens. Submitting clean claims for service code 92014 requires attention to coding requirements and modifier usage.
When billing CPT 92014 alongside other procedures on the same day, a modifier needed flag may appear in the billing software. For example, if a physician performs a minor surgical procedure (like an intravitreal injection, CPT 67028) on the same day as the 92014 exam, the provider must append Modifier 25 to the 92014 code. Modifier 25 indicates that the evaluation and management service was significant, separately identifiable, and above the standard preoperative care required for the injection.
Failure to append Modifier 25 when performing concurrent minor surgeries is a primary cause of denial. Another common denial occurs when billers use 92014 for an annual eye exam CPT code under a patient’s medical insurance, but the patient only has a routine refractive diagnosis (like myopia or astigmatism) without a qualifying medical disease. Verifying the patient’s insurance coverage type before the visit prevents this specific denial.
Summary of CPT code 92014 guidelines
Understanding CPT code 92014 protects ophthalmology practices from compliance risks and revenue loss. The code demands an established patient relationship, a comprehensive evaluation of the visual system, and clear documentation of an ongoing or newly initiated diagnostic and treatment plan. By differentiating medical eye exams from routine vision checks, applying modifiers correctly, and billing refraction separately when required, medical coders can ensure accurate reimbursement and maintain strict adherence to AMA and CMS coding standards.