

An ENT operative note may document multiple anatomical sites, various instruments, and several distinct surgical steps. Translating that record into a claim requires deciding which services stand alone, which belong within another procedure, and which details support the diagnosis.
Otolaryngology (ENT) coding mistakes often result from subtle differences, such as suctioning mucus versus excising tissue, inspecting both nasal passages versus performing a separately billable bilateral procedure, or conducting an evaluation that extends beyond the services included in an endoscopy.
The following errors deserve focused review in ENT billing and coding. Each section explains the relevant distinction and offers a practical way to check the claim before submission.
1. Selecting a procedure code from the appointment label
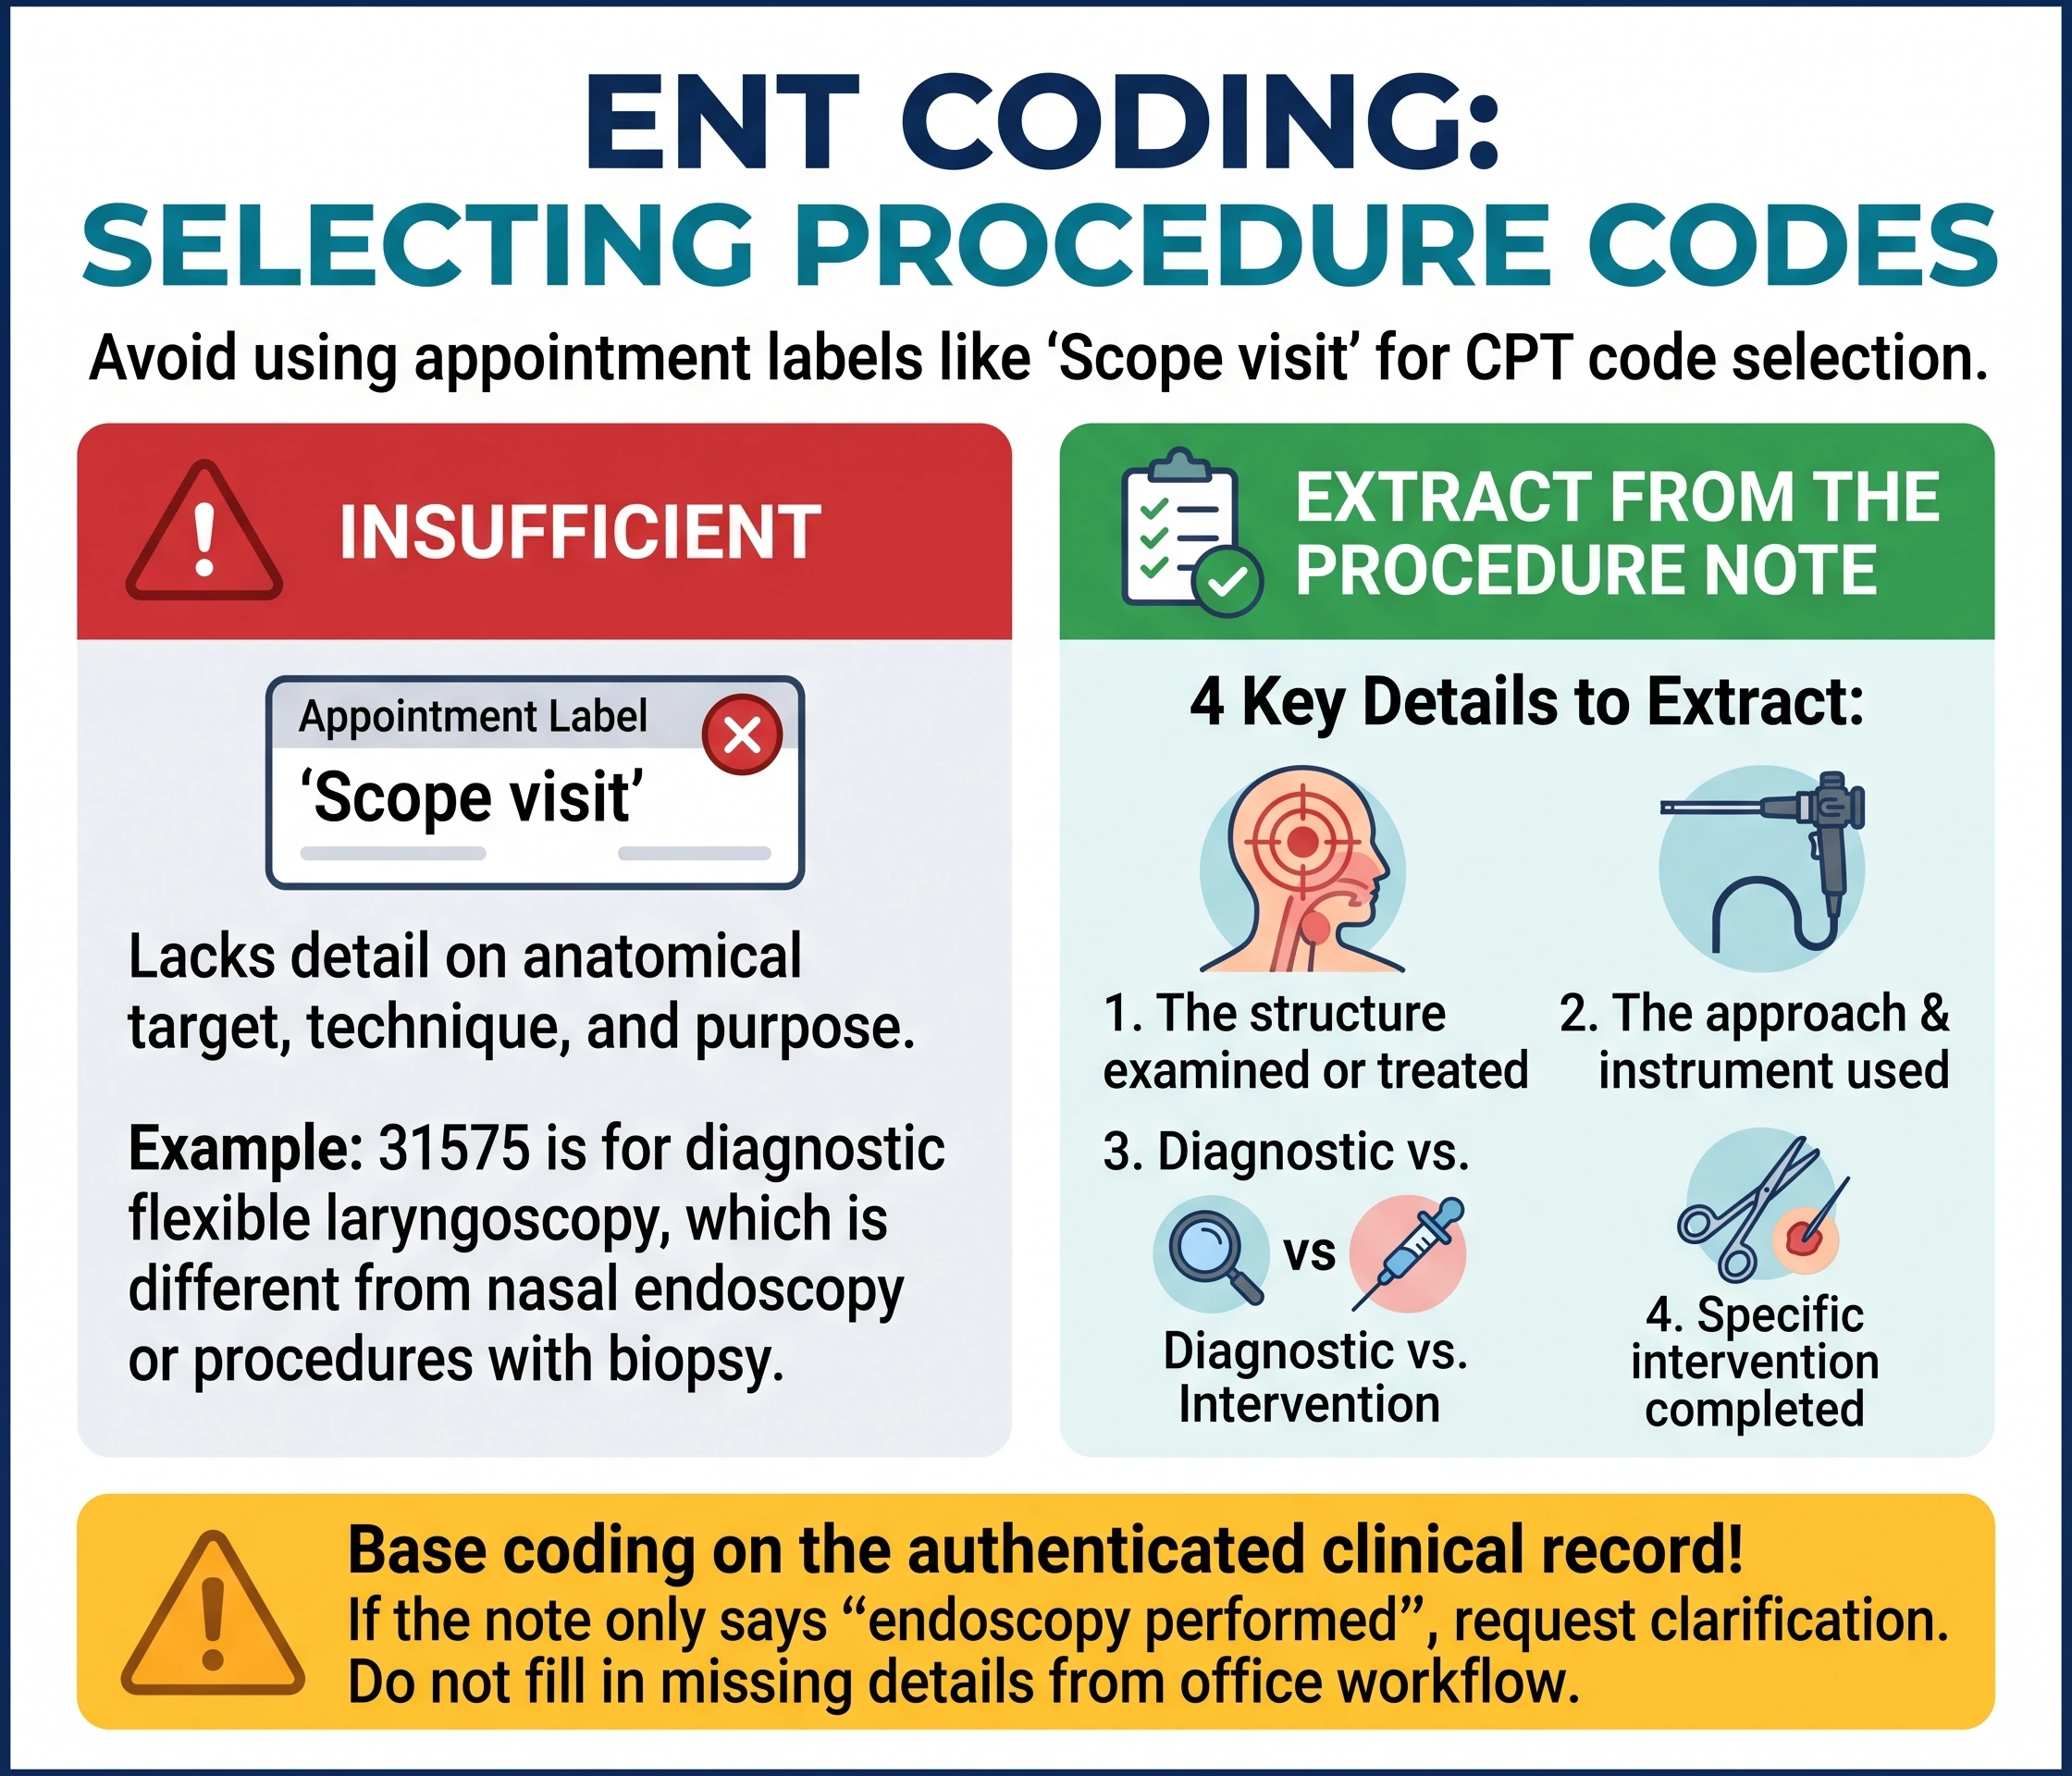
“Scope visit” is insufficient for CPT code selection. The completed procedure, anatomical target, technique, and purpose determine the appropriate code.
For example, diagnostic nasal endoscopy and diagnostic flexible laryngoscopy represent different services. AAO-HNS’s Clinical Indicators: Laryngoscopy/Nasopharyngoscopy, dated January 1, 2015, identifies 31575 for diagnostic flexible laryngoscopy and distinguishes it from procedures involving biopsy, lesion removal, or stroboscopy.
Before selecting ENT CPT codes, extract four details from the procedure note:
- The structure examined or treated.
- The approach and instrument used.
- Whether the service was diagnostic or involved an intervention.
- The specific intervention actually completed.
Use scheduling information to locate the encounter. Base coding on the authenticated clinical record. If the note says only “endoscopy performed,” request clarification instead of filling in missing details from the usual office workflow.
2. Automatically adding modifier 25 to an office visit
An office visit and a procedure on the same date do not automatically justify two separately payable services.
In its July 23, 2026 article CPT for ENT – Modifier 25, the American Academy of Otolaryngology–Head and Neck Surgery (AAO-HNS) explains that the evaluation and management service must extend beyond the usual work associated with the procedure. Modifier 25 belongs on the E/M code, and its use requires supporting documentation.
Consider a hypothetical patient evaluated for persistent nasal symptoms who also undergoes nasal endoscopy. The reviewer should identify the assessment and management performed beyond the procedure’s usual preparation and associated care.
Do not rely on note length. Instead, ask: What separately identifiable clinical work supports this office visit?
Likewise, a new-patient designation alone does not justify a separate E/M service with a minor procedure. CMS’s January 1, 2026 Medicare NCCI Policy Manual, Chapter V, also states that separate diagnoses are not required.
3. Separately billing diagnostic work included in surgical endoscopy

A diagnostic examination may occur before an endoscopic intervention during the same encounter. That sequence does not necessarily create two reportable procedures.
The 2026 CMS NCCI manual states that diagnostic endoscopy is included in surgical endoscopy. It also identifies control of bleeding caused by an endoscopic procedure as integral to that procedure.
For instance, when auditing a surgical nasal endoscopy claim, verify whether a separately billed diagnostic endoscopy simply represents the examination performed before the procedure.
A useful audit question is: Does this additional code represent independent work, or a necessary part of the principal procedure?
Review the operative narrative alongside the claim. A charge-entry template that lists every documented step can produce unbundling unless someone evaluates how those steps relate.
4. Reporting nasal endoscopy and laryngoscopy without a distinct-service basis
Passing a flexible laryngoscope through the nose does not automatically support a separate diagnostic nasal endoscopy charge.
AAO-HNS addresses this distinction in CPT for ENT: Nasal Endoscopy and Laryngoscopy on the Same Date of Service, dated December 19, 2023. The guidance outlines specific situations in which a separate rigid nasal endoscopy may be medically necessary when a flexible endoscope cannot sufficiently visualize the relevant anatomical structures.
When reviewing both services, look for documentation explaining:
- The clinical reason for each examination.
- Why a separate instrument was necessary.
- The structures examined and findings from each procedure.
Choosing to use two instruments based on preference alone does not justify medical necessity. Check the applicable edit and payer requirements before reporting both codes, even when the procedure notes appear separately in the chart.
5. Treating modifier 59 as a general denial remedy
Adding modifier 59 after a denial requires a documented coding basis.
CMS’s April 2026 booklet, Proper Use of Modifiers 59, XE, XP, XS & XU, clarifies the role of National Correct Coding Initiative procedure-to-procedure edit indicators.
Edit indicator | Meaning for claim review |
0 | An NCCI-associated modifier cannot bypass the edit. |
1 | A modifier may bypass the edit only when the documented circumstances qualify. |
An indicator of 1 is permission to evaluate an exception, not automatic permission to unbundle. CMS also instructs providers to use modifier 59 only when another modifier does not better describe the relationship between services.
Build a short explanation into the review process: identify the separate encounter, anatomical site, or other qualifying circumstance. If the reviewer cannot explain the distinction using the medical record, hold the modifier for further review.
6. Coding mucus suction as tissue removal
The material removed during sinus work can change the code selection.
In CPT for ENT: Sinusectomy Codes, dated December 19, 2023, AAO-HNS distinguishes aspiration of mucus or pus from removal of tissue or necrotic material. Diagnostic endoscopy with aspiration alone does not support surgical debridement simply because suction was used.
For a hypothetical note stating “purulent secretions suctioned during endoscopic examination,” do not infer that tissue debridement occurred.
Ask the surgeon to describe what was removed, its location, and the intervention performed. Avoid templates that substitute “debridement” for any postoperative cleaning.
This documentation check also helps distinguish sinus procedures that include tissue removal from those that do not. The operative report should support the actual code elements rather than merely repeat the selected procedure name.
7. Missing combination codes and bilateral rules
Sinus surgery coding requires a side-specific account of the work completed.
AAO-HNS’s December 19, 2023 article on the FESS and balloon sinus dilation code families describes combination codes. For example, 31253 encompasses total ethmoidectomy with frontal sinus exploration on the same side. Reporting component procedures separately can conflict with the combination-code instructions.
Create a right-and-left procedure map before choosing the final code set. Identify each sinus treated and whether the documented work includes tissue removal.
Bilateral coding needs a separate check. AAO-HNS’s CPT for ENT: Nasal Sinus Endoscopy, dated December 19, 2023, identifies 31231 as covering unilateral or bilateral diagnostic examination. Examining both sides therefore does not justify doubling the service or adding modifier 50 to that code.
Do not apply one bilateral reporting pattern to every otolaryngology CPT code.
8. Reporting an unconfirmed outpatient diagnosis
ENT diagnosis codes must reflect the certainty and detail documented for the encounter.
The FY 2027 ICD-10-CM Official Guidelines for Coding and Reporting, issued by CMS and CDC’s National Center for Health Statistics for the period beginning October 1, 2026, instruct outpatient coders not to report uncertain diagnoses as established. Instead, code the signs, symptoms, or other findings representing the highest degree of certainty.
For example, “possible Ménière’s disease” in an outpatient assessment does not support coding confirmed Ménière’s disease.
Also review laterality and documented diagnostic detail. Avoid choosing an unspecified ENT ICD-10 code when the record supports a more specific one. Conversely, do not invent specificity.
Verify the selection in both the Alphabetic Index and Tabular List, including applicable instructions. An electronic search result is a starting point, not the complete ICD-10-CM coding review.
9. Overlooking the postoperative global period
Postoperative encounters require review of the original procedure and its global surgery indicator.
CMS’s Global Surgery booklet, dated December 2025, explains that routine recovery care and specified related services fall within the surgical package. It distinguishes unrelated postoperative E/M services, potentially reported with modifier 24, from unrelated procedures, potentially reported with modifier 79.
Do not assume every ENT operation has the same postoperative period. Look up the actual procedure.
During an ENT billing audit, place the surgical date, procedure code, global indicator, and reason for the subsequent encounter together. This makes it easier to identify both inappropriate separate billing and separately reportable services that were overlooked.
A postoperative appointment label alone cannot settle the coding decision.
10. Documenting the procedure without supporting medical necessity
A technically accurate procedure code does not establish coverage.
Anthem’s CG-SURG-24 Functional Endoscopic Sinus Surgery, reviewed May 14, 2026, illustrates how coverage can depend on documented symptoms, previous treatment, and objective findings. Its requirements vary by clinical circumstance and should not be treated as universal rules for every insurer.
For ENT medical necessity documentation, build a checklist from the policy applicable to the patient’s plan and service date. Locate the supporting history, examination, imaging, treatment response, and procedure indication.
Replace vague entries such as “failed treatment” with the actual treatments and documented responses. Keep coding review and coverage review as separate checkpoints so neither is overlooked.
How to avoid otolaryngology (ENT) coding errors through focused audits
Use a recurring ENT coding audit to review selected endoscopy claims, modifier use, sinus operations, and postoperative encounters. Include paid claims alongside denials so the review does not depend entirely on payer feedback.
Record the specific defect, the correction, and who will address its source. A missing anatomical detail needs clinician clarification; an incorrect default modifier needs a charge-entry correction.
Preventing otolaryngology (ENT) coding errors requires matching each claim line to the documented service, applicable coding instructions, and relevant coverage policy. That claim-by-claim discipline gives the practice a concrete way to identify repeated mistakes and verify whether corrections are working.