


The 99386 CPT code designates an initial comprehensive preventive medicine evaluation and management service for a new patient between the ages of 40 and 64 years. Medical coders and healthcare providers use this specific code to report routine physical examinations, wellness visits, and preventive health screenings that do not focus on treating an acute illness. Proper application of this code requires meeting strict criteria set by the American Medical Association (AMA) regarding patient age, visit history, and documentation standards.
CPT 99386 description and primary use
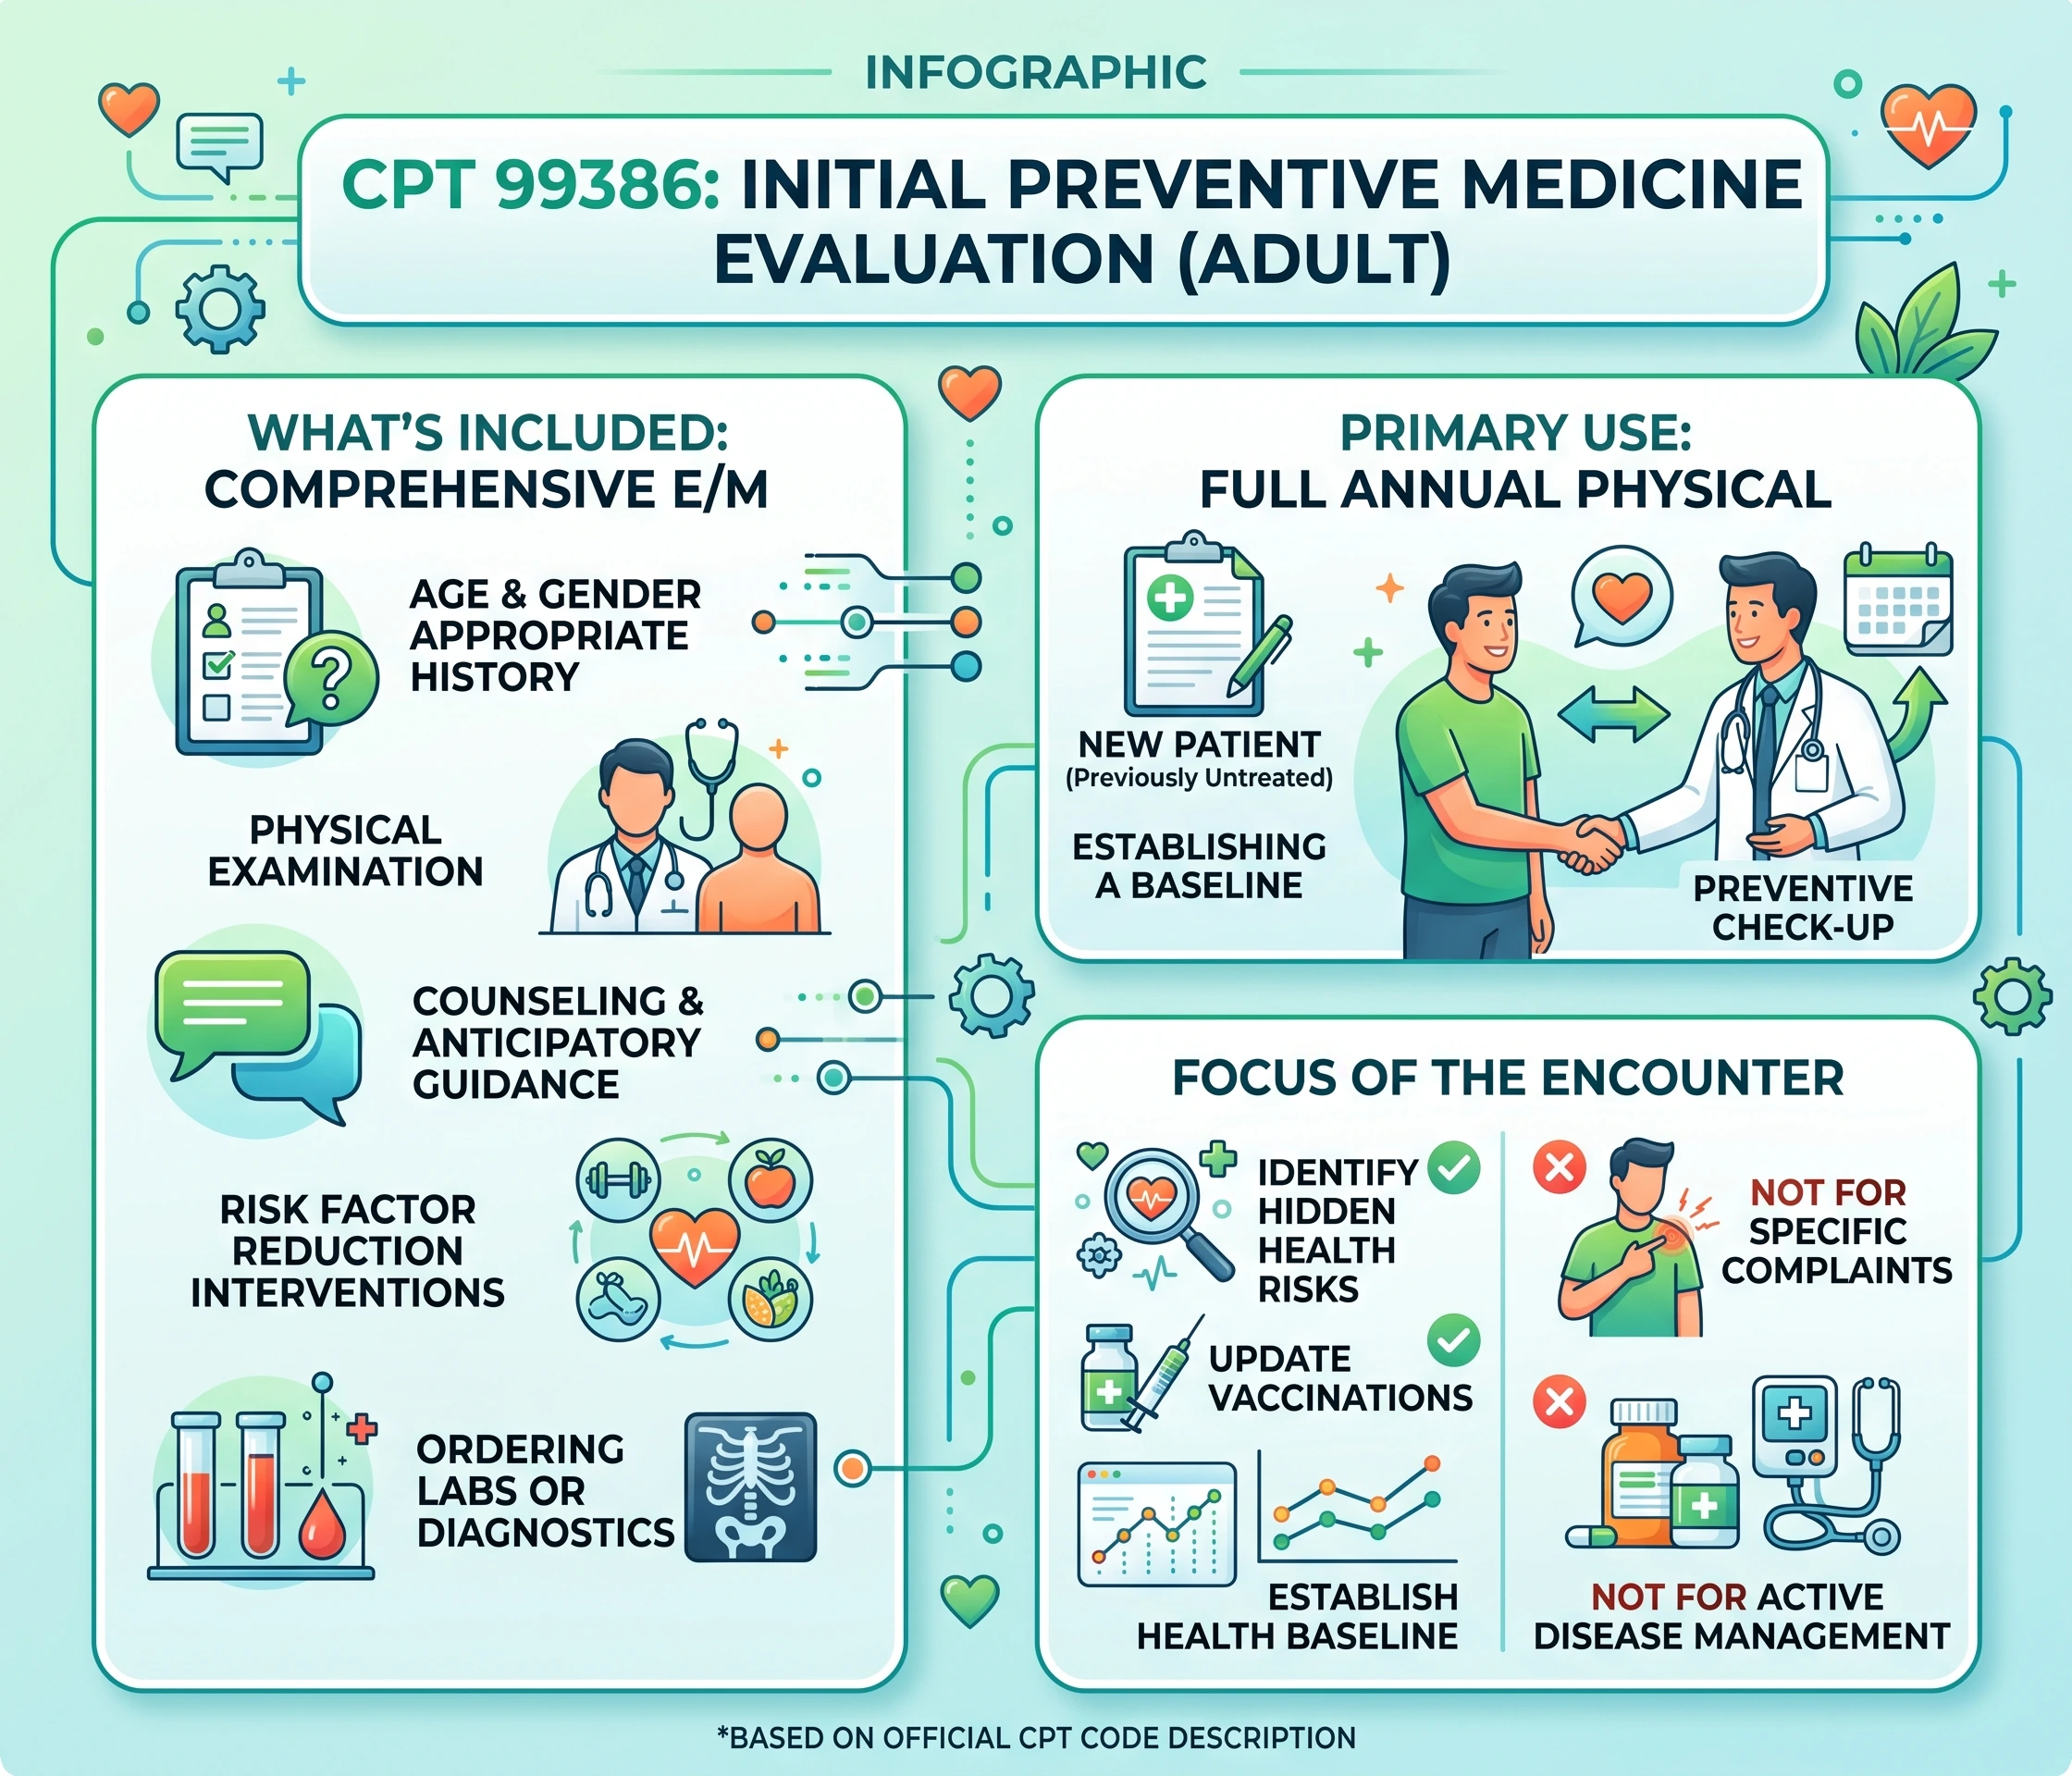
The official 99386 CPT code description outlines the service as an initial comprehensive preventive medicine evaluation and management of an individual. This encounter includes an age and gender-appropriate history, examination, counseling, anticipatory guidance, risk factor reduction interventions, and the ordering of laboratory or diagnostic procedures.
Providers bill this code when they perform a full annual physical on an adult patient they have not treated previously. The service focuses on identifying hidden health risks, updating vaccinations, and establishing a baseline of health rather than managing a specific complaint or active disease.
99386 age limit and patient eligibility
The CPT 99386 age limit strictly restricts this code to patients who are 40 through 64 years of age on the exact date of service. Age verification prevents immediate claim denials. If a patient is 39 years old on the day of the exam, the provider must bill CPT 99385. If the patient is 65 or older, the correct code is 99387.
Who is eligible for CPT 99386? Beyond the age requirement, the patient must meet the AMA definition of a new patient. A new patient is an individual who has not received any face-to-face professional services from the billing physician, or another physician of the exact same specialty and subspecialty within the same group practice, during the past three years.
What is the difference between 99386 and 99396?
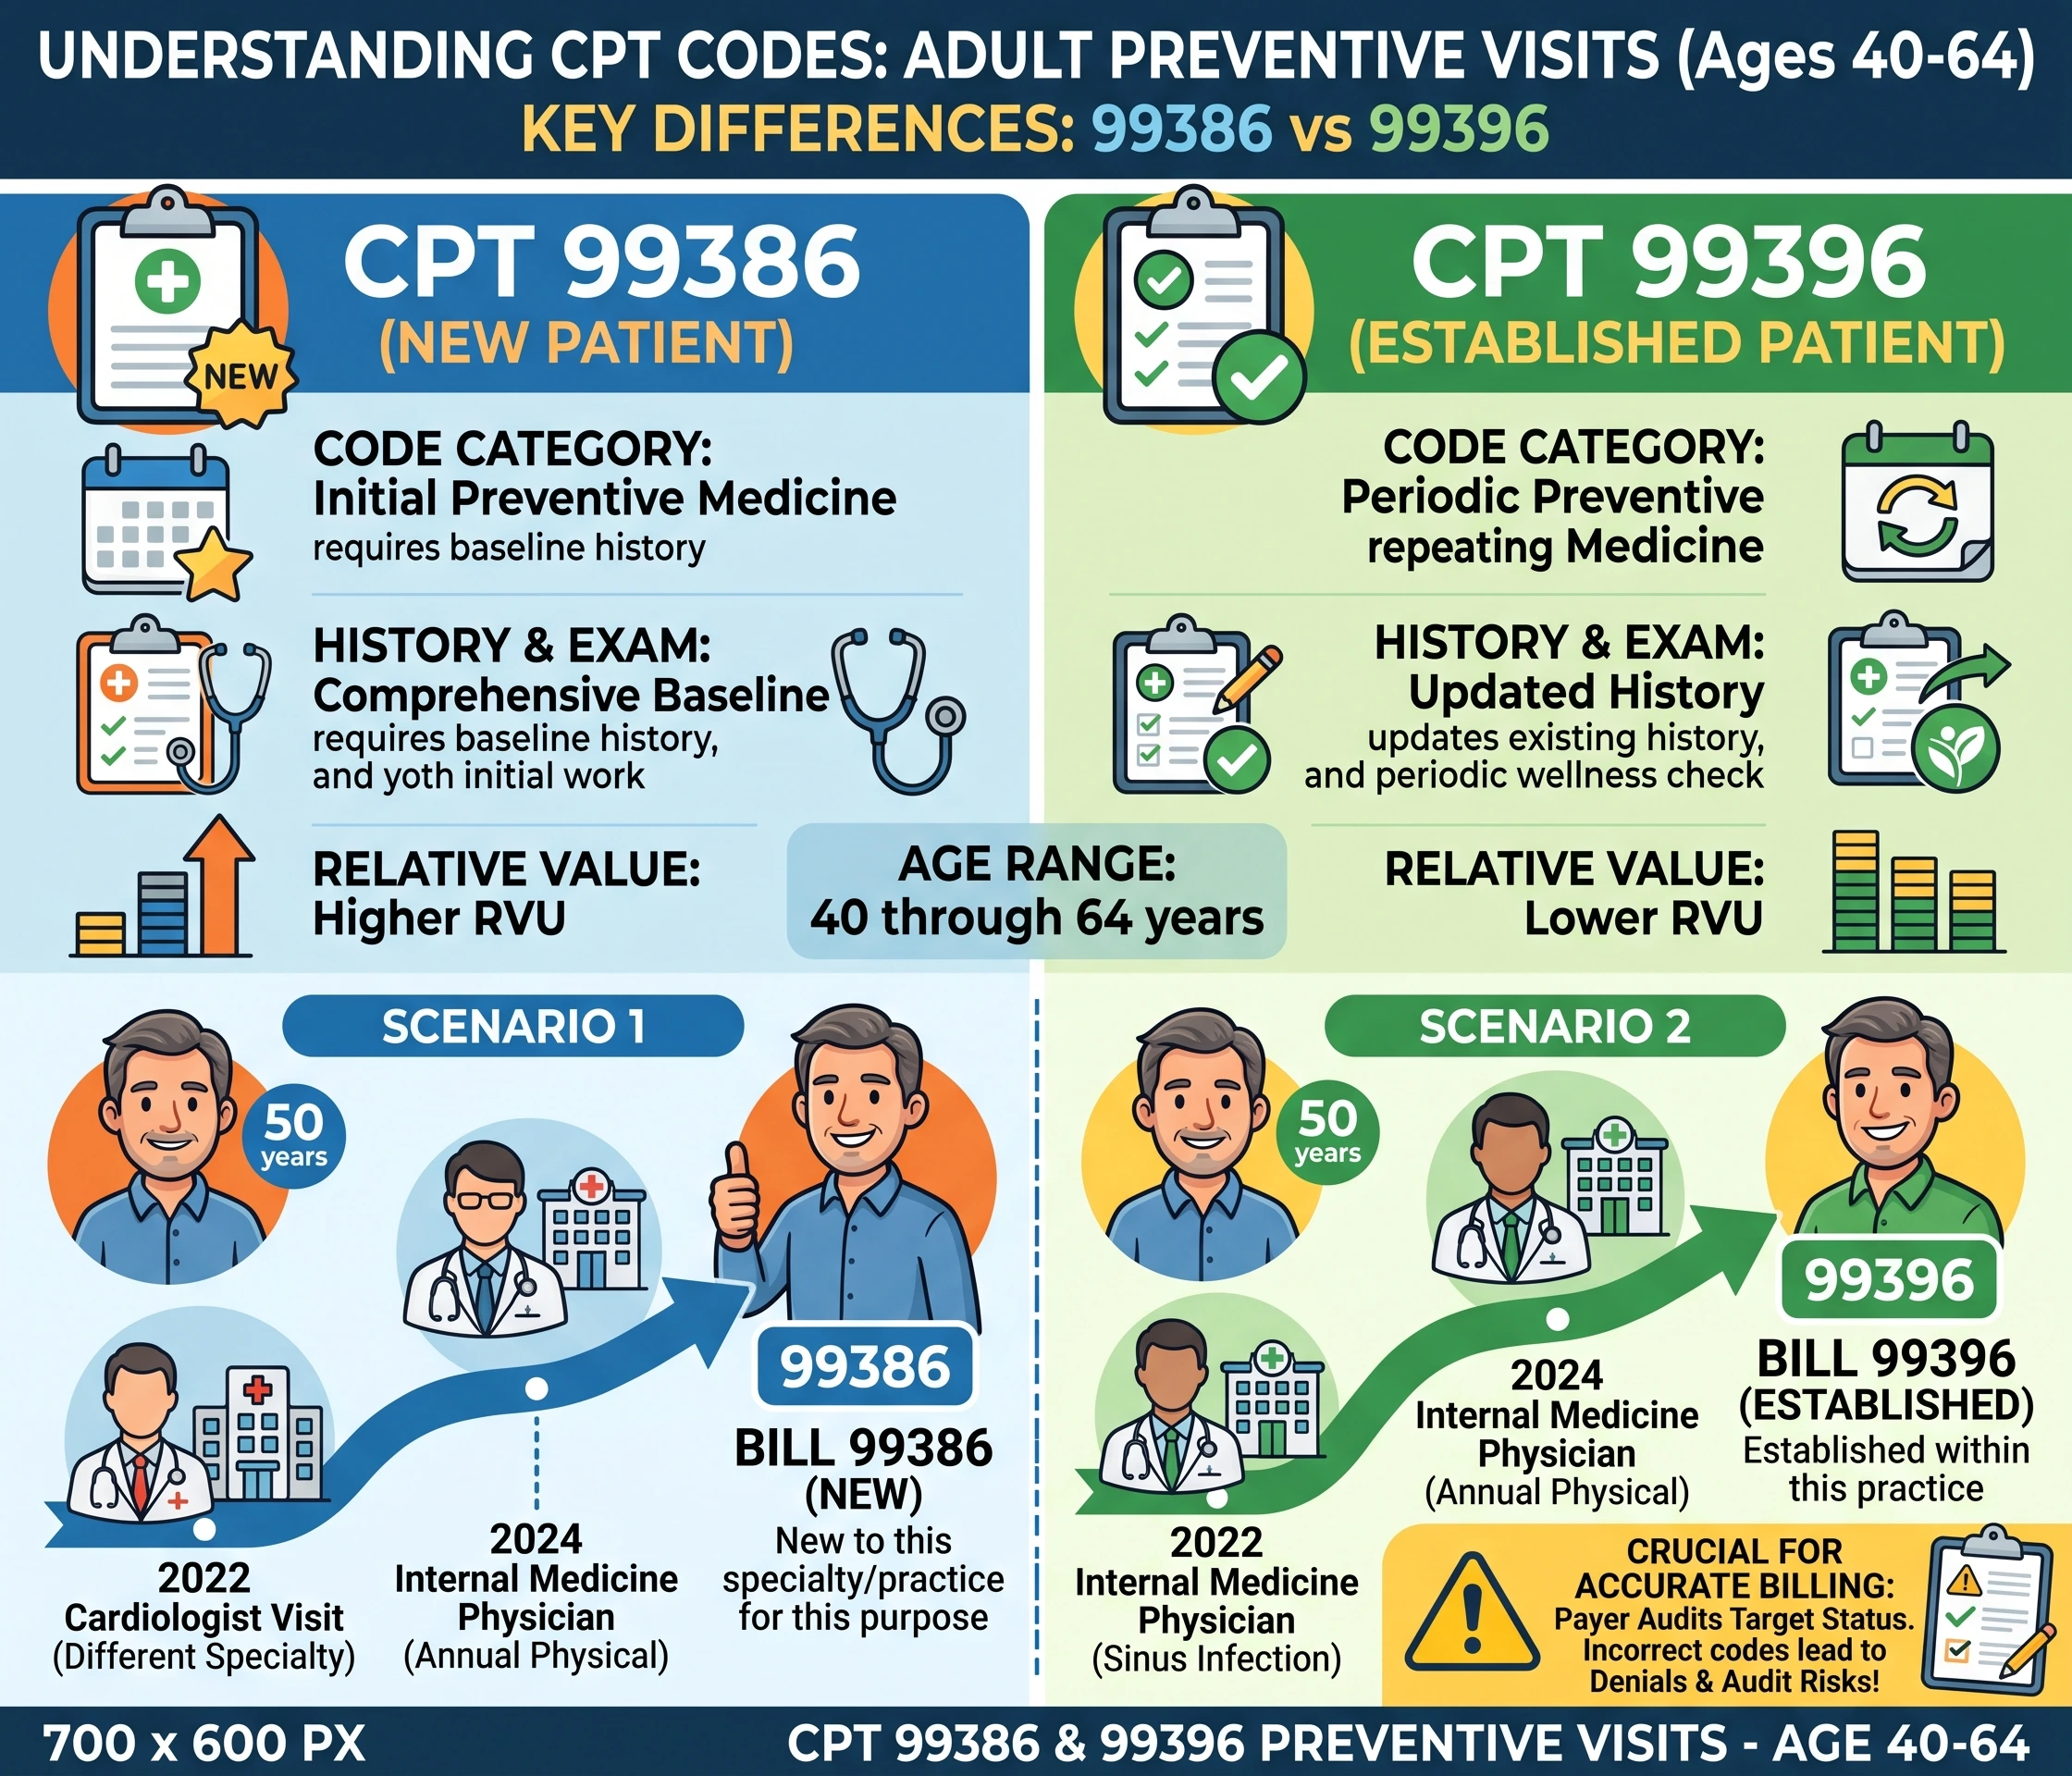
Coders frequently choose between 99386 and 99396 when billing for adult preventive visits. The distinction relies entirely on the patient’s billing history within the medical practice. Payer audits routinely target these records to verify patient status.
Feature | CPT Code 99386 | CPT Code 99396 |
Patient Status | New Patient | Established Patient |
Age Range | 40 through 64 years | 40 through 64 years |
Code Category | Initial preventive medicine | Periodic preventive medicine |
Relative Value | Higher (requires baseline history) | Lower (updates existing history) |
Consider a 50-year-old patient who visits a multispecialty clinic. The patient saw a cardiologist at the clinic in 2022. In 2024, the patient schedules an annual physical with an internal medicine physician within the same organization. Because cardiology and internal medicine are different specialties, the patient is new to the internal medicine physician. The coder correctly reports the 99386 new patient code.
Conversely, if the patient saw an internal medicine physician in the practice for a sinus infection in 2022 and schedules a physical with a different internal medicine physician in the same practice in 2024, the patient remains established. The coder must report 99396.
99386 documentation requirements
To withstand payer audits, the medical record must reflect all components of a comprehensive preventive service. The AMA documentation requirements for 99386 differ from problem-oriented Evaluation and Management (E/M) codes. Preventive medicine codes do not follow the 2021 Medical Decision Making (MDM) or time-based guidelines used for sick visits like 99203 or 99214.
A compliant 99386 clinical note must contain:
- Comprehensive history: A full review of the patient’s past medical, family, and social history, alongside a complete review of systems.
- Comprehensive examination: A physical exam appropriate for the patient’s age, gender, and identified risk factors.
- Counseling and anticipatory guidance: Discussion regarding diet, exercise, substance use, sexual activity, or injury prevention.
- Orders: Any age-appropriate screening labs or diagnostic procedures requested during the encounter.
The history gathering establishes the patient’s baseline. The provider must record past surgeries, current medications, drug allergies, and chronic conditions. The family history should identify hereditary diseases, particularly cardiovascular disease and cancers common in the 40 to 64 age bracket. The social history must document occupational hazards, tobacco use, alcohol consumption, and physical activity levels.
The physical examination requires a multi-system assessment. For a patient in this age group, the provider typically records vital signs, calculates body mass index (BMI), and examines the cardiovascular, respiratory, gastrointestinal, and musculoskeletal systems. A gender-appropriate exam involves a clinical breast exam and pelvic exam for females, or a testicular and prostate exam for males. If the provider skips the physical examination entirely, the service does not meet the CPT 99386 description.
Preventive risk factor interventions for ages 40 to 64
The 99386 age limit targets adults in middle age. The documentation of counseling and anticipatory guidance must match the specific health risks associated with this demographic. Stating “counseling provided” without detailing the subjects covered often leads to claim denials upon review.
A compliant chart note for a 40 to 64-year-old documents discussions regarding:
- Colorectal cancer screening options starting at age 45, following American Cancer Society guidelines.
- Breast cancer screening and mammography schedules for female patients.
- Prostate cancer screening discussions for male patients.
- Cardiovascular risk assessments, including lipid panels and blood pressure monitoring.
- Weight management and metabolic disease screening.
Providers order these tests during the 99386 encounter. The laboratory tests themselves are billed separately, but the physician’s work in assessing the need for the tests and ordering them is included in the preventive visit code.
Linking diagnosis codes to 99386
Medical billing rules require every CPT code to link to an appropriate ICD-10-CM diagnosis code. For a 99386 CPT code, the primary diagnosis must reflect a routine examination.
Coders typically assign Z00.00 (Encounter for general adult medical examination without abnormal findings) or Z00.01 (Encounter for general adult medical examination with abnormal findings). If the provider discovers a new condition during the physical, the coder lists Z00.01 as the primary diagnosis and adds the specific diagnosis code for the new condition as a secondary code. Using a sickness-related diagnosis as the primary pointer for a preventive medicine CPT code triggers an automatic claim denial from the payer.
99386 coverage, frequency limit, and payer policies
Is CPT 99386 billable? Yes, but reimbursement depends entirely on the patient’s insurance type. Most commercial insurance plans cover preventive medicine services at 100% without patient cost-sharing, complying with Affordable Care Act mandates.
What insurance covers CPT 99386? Commercial payers (Blue Cross Blue Shield, UnitedHealthcare, Aetna, Cigna) and Medicaid programs accept this code.
Medicare operates under different federal statutes. Section 1862(a)(7) of the Social Security Act excludes routine physical checkups from Medicare coverage. Medicare does not cover routine preventive physical examinations billed under 99386 or 99396. When a provider performs a comprehensive preventive medicine examination on a Medicare Part B beneficiary and bills 99386, Medicare denies the charge. The patient becomes financially responsible for the visit.
To provide preventive care for Medicare patients, providers must bill the Annual Wellness Visit (AWV) using HCPCS codes G0438 for the initial visit or G0439 for subsequent visits. These G-codes do not require a comprehensive physical examination. They focus on health risk assessments, functional ability checks, and creating a personalized prevention plan.
The standard 99386 frequency limit for commercial payers is one visit per 12-month period. Some payers define this strictly as 365 days from the previous preventive visit. Others allow one visit per calendar year regardless of the exact date. Billing staff must verify the specific payer’s frequency rules prior to the appointment.
Billing requirements and Modifier 25
Patients often present for a preventive examination and bring up a new or existing medical problem that requires active management. When a provider addresses a significant, separately identifiable problem during the 99386 encounter, the coder can report an additional problem-oriented E/M code (e.g., 99213 or 99214).
To bypass National Correct Coding Initiative (NCCI) edits, the coder must append Modifier 25 to the problem-oriented E/M code. The documentation must clearly separate the preventive service from the diagnostic workup and medical decision-making for the acute or chronic problem.
Routine prescription refills do not justify a separate E/M code. If a provider refills a stable patient’s maintenance blood pressure medication during an annual physical without performing an independent evaluation of the condition, billing a 99213 with Modifier 25 creates a compliance risk. However, if the patient presents with new onset abdominal pain requiring a separate history, examination, and diagnostic plan, reporting both codes is appropriate.
Billing 99386 with immunizations and screenings
Preventive visits frequently include the administration of vaccines and routine screening tests. The 99386 CPT code covers the provider’s time spent recommending these services, but it does not cover the clinical staff’s time administering vaccines or the cost of the vaccine products.
Coders report vaccine products using specific medicine codes (e.g., 90686 for the quadrivalent flu vaccine). The clinic also bills the vaccine administration code (e.g., 90471). A common billing error involves appending Modifier 25 to the 99386 code when the only additional service is a vaccine. NCCI guidelines dictate that Modifier 25 is not required on the preventive visit code when billing vaccine administration codes alone.
If the provider performs a screening electrocardiogram during the physical, the coder reports 93000 (Electrocardiogram, routine ECG with at least 12 leads). Because an EKG is a separate diagnostic procedure, it generates its own reimbursement line on the claim.
Telehealth coverage rules
The shift toward virtual care introduced limitations for preventive medicine codes. CPT 99386 inherently requires a comprehensive physical examination. Most physical exam elements, such as palpation, auscultation of the lungs, and reflex testing, cannot occur over a video connection.
Current billing rules from commercial payers generally exclude 99386 from telehealth coverage. Payers require an in-person, face-to-face encounter to satisfy the examination requirement. If a provider performs a virtual wellness check that lacks a physical exam, they must use different codes.
Time-based billing exclusions
The 2021 evaluation and management coding updates overhauled how providers bill for standard office visits. Those codes now rely on total time spent on the date of service or the level of Medical Decision Making.
These updates do not apply to preventive medicine codes. Providers cannot use time or MDM to bill CPT 99386. The code requires the completion of all documented components: history, examination, and counseling. If a provider spends 60 minutes counseling a new 50-year-old patient on diet and exercise but does not perform a physical examination, the provider cannot bill 99386. The coder relies on preventive medicine counseling codes (99401-99404) to capture face-to-face counseling time without a physical exam.
99386 CPT code reimbursement and RVU data
The Centers for Medicare & Medicaid Services (CMS) assigns Relative Value Units (RVUs) to CPT codes to determine standard compensation rates. Even though Medicare does not pay for 99386, CMS maintains the RVU valuation. Commercial payers use these RVU weights to build their specific fee schedules.
For 99386 wRVU (Work RVU), CMS allocates 2.29 units to reflect the physician’s time, skill, and effort. The total RVU for 99386 in a non-facility setting (a private medical office) typically ranges from 4.70 to 4.90, depending on the annual CMS practice expense calculations and the Geographic Practice Cost Index (GPCI).
Reimbursement varies heavily by state and commercial contract. Based on standard RVU multiplication against national conversion factors, the unadjusted baseline payment rate sits near $155 to $165. Medical practice administrators negotiate direct fee schedules with regional payers, resulting in actual reimbursements that range from $120 to over $200 per encounter.
Accurate reporting of the 99386 CPT code requires precise alignment of patient age, visit history, and clinical documentation. Providers must verify the patient is between 40 and 64 years old and has no prior billing history with the same specialty in the practice for three years. With a wRVU of 2.29, this code compensates physicians for the extensive history, physical exam, and counseling required for middle-aged adults. By applying correct diagnosis codes like Z00.00 and routing Medicare patients to specific G-codes, medical practices prevent denials and secure accurate payment for initial preventive care.