


Billers and coders run into the 99395 CPT code constantly in family medicine, internal medicine, and OB/GYN practices, yet it still generates more denials than it should. Part of the confusion comes from how differently Medicare and commercial payers treat it. Part of it comes from billers applying office-visit logic (history, exam, medical decision-making) to a code that isn’t built that way. This guide works through what CPT 99395 actually covers, who qualifies, how often it can be billed, what it pays, and where claims tend to fall apart.
What is CPT code 99395?

CPT code 99395 sits inside the American Medical Association’s Preventive Medicine Services section, itself a subset of Evaluation and Management Services. The code describes a periodic, age and gender appropriate history and physical examination for an established patient aged 18 through 39, along with counseling, anticipatory guidance, risk factor reduction, and the ordering of appropriate labs or diagnostic tests.
In plain language, this is the code for an adult’s annual physical, billed when the adult has already established care with the practice. A biller in a family medicine or internal medicine office will run into it often: it covers the entire working-age adult population under 40 who already has a relationship with the provider or group.
A few identifying facts worth keeping on hand:
- Code: 99395
- Category: Preventive Medicine Services, Established Patient
- Age range: 18 through 39 years, determined by the patient’s age on the date of service
- Patient status: Established (not new)
- Typical frequency: Once per 12-month period for most payers
- E/M leveling: Not required; the code isn’t selected by history, exam, or medical decision-making complexity
Where 99395 fits among the preventive visit codes
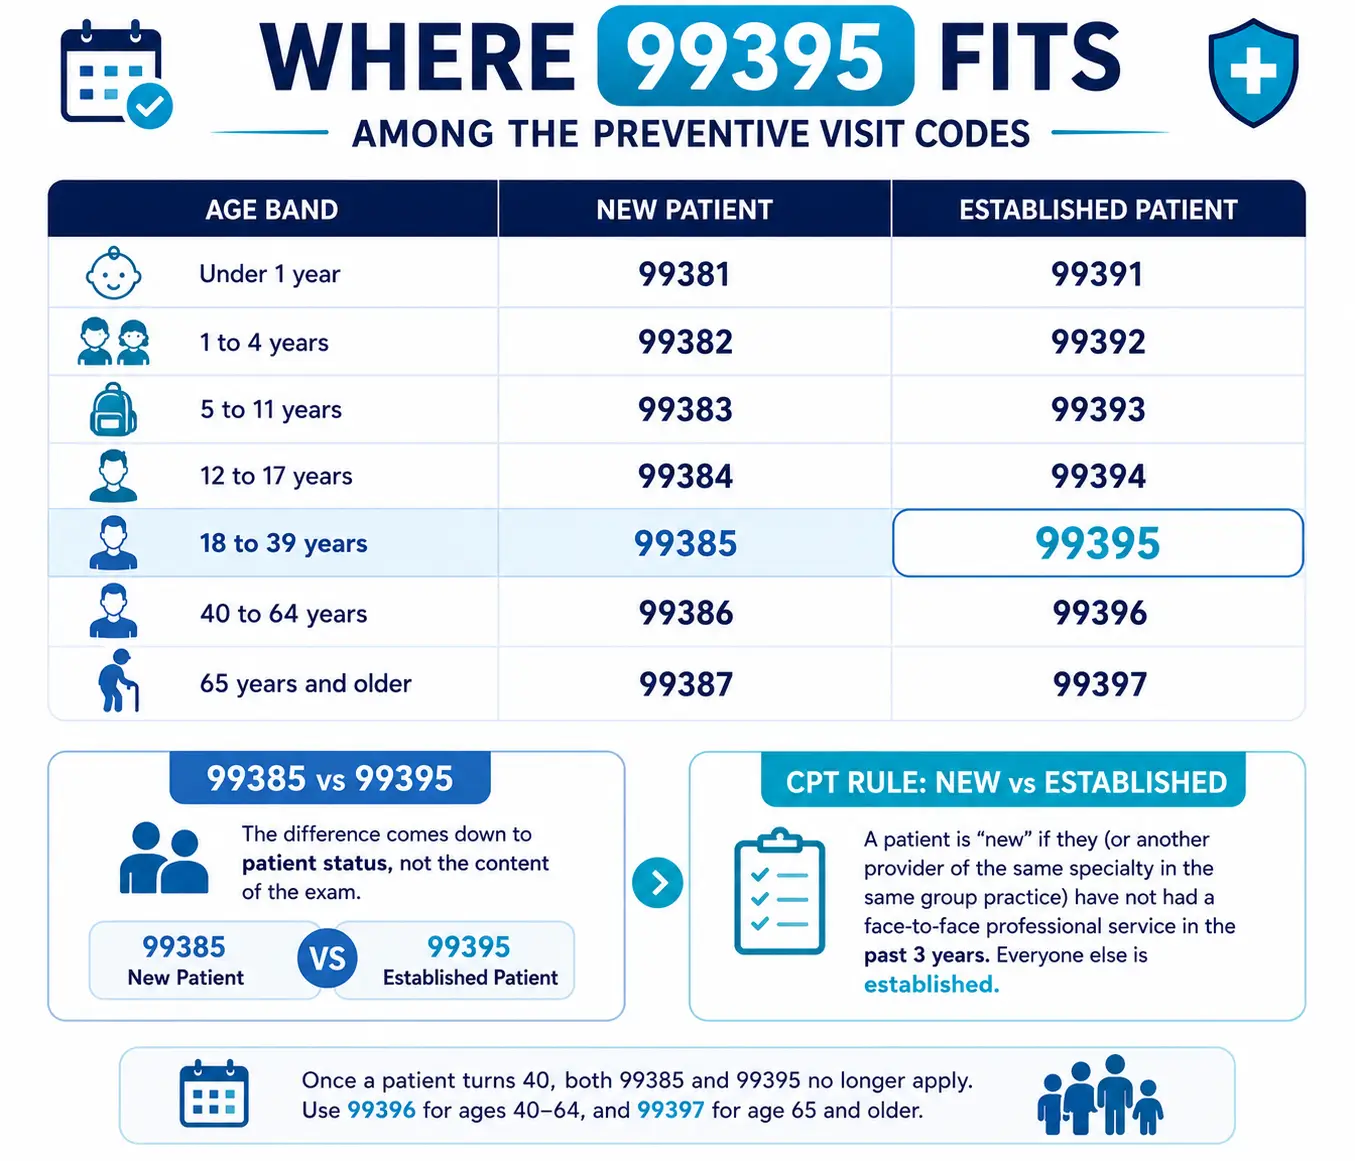
CPT organizes preventive medicine codes into two parallel ladders, one for new patients and one for established patients, both broken out by age band.
Age band | New patient | Established patient |
Under 1 year | 99381 | 99391 |
1 to 4 years | 99382 | 99392 |
5 to 11 years | 99383 | 99393 |
12 to 17 years | 99384 | 99394 |
18 to 39 years | 99385 | 99395 |
40 to 64 years | 99386 | 99396 |
65 years and older | 99387 | 99397 |
The difference between 99385 and 99395 comes down to patient status alone, not the content of the exam. Under CPT rules, a patient counts as new if that patient (or another physician or qualified health care professional of the same specialty and subspecialty in the same group practice) has not provided a face-to-face professional service within the past three years. Everyone else is established. The moment a patient turns 40, both 99385 and 99395 stop applying, and the practice shifts to 99396 for every visit after that, until age 65 triggers the move to 99397.
What has to be documented
Because 99395 is a preventive medicine code rather than a standard office visit code, it doesn’t get leveled the way 99202 through 99215 do. There’s no checklist of organ systems or MDM elements to satisfy. What payers do expect is a note that actually demonstrates the visit was preventive, covering:
- An age and gender appropriate history, updated from the prior visit rather than copied forward unchanged
- A physical exam scaled to the patient’s age and individual risk factors, not organized around a symptom
- Counseling and anticipatory guidance on topics relevant to this age group: diet, physical activity, substance use, sexual and reproductive health, mental health screening, and injury prevention
- Orders for age-appropriate labs, screenings, or immunizations
A note structured like a problem-oriented visit (a chief complaint, a history of present illness built around one symptom, an assessment and plan tied to a diagnosis) undercuts the preventive classification even when 99395 is the code on the claim. Payers and auditors specifically look for that mismatch between the code billed and the shape of the documentation, and it’s one of the more common reasons a preventive claim gets downcoded or denied on review.
99395 frequency limit: how often can it be billed?
Most commercial and ACA marketplace plans allow one preventive visit per 12-month period, and most claims systems apply roughly an 11-to-13-month window rather than counting exactly 365 days, which accommodates normal scheduling drift. Billing 99395 twice inside that window, even for a legitimate second concern, usually gets treated as a duplicate preventive service and denied. A genuinely necessary second visit within the interval generally needs to go out as a problem-oriented E/M code with documentation supporting medical necessity, not as a second preventive exam, and some payers require prior authorization before they’ll consider a second preventive visit at all.
99395 CPT code coverage and reimbursement
Commercial and ACA marketplace plans
Preventive services rated A or B by the U.S. Preventive Services Task Force fall under the Affordable Care Act’s preventive services mandate, which requires most private group and individual plans to cover them without cost-sharing: no copay, coinsurance, or deductible applied to the patient. A routine adult physical billed under 99395 typically qualifies for that protection as long as the visit stays preventive in nature. That protection disappears for the portion of the visit spent on a separate problem, since problem-oriented care is billed and cost-shared like any other office visit.
Medicare and CPT 99395
This is where billers most often go wrong. Medicare Part B excludes routine physical examinations from coverage under the Social Security Act, and 99395 falls squarely inside that exclusion. Submitting 99395 to traditional Medicare doesn’t result in a reduced payment; it results in a denial. Medicare instead uses its own set of preventive visit codes:
Scenario | Correct code | Note |
First 12 months of Part B enrollment | G0402 (Welcome to Medicare visit) | One-time only |
Enrolled over 12 months, no prior AWV | G0438 (Initial Annual Wellness Visit) | One-time only |
Any AWV after the first one | G0439 (Subsequent AWV) | Once every 12 months |
Established, non-Medicare patient, age 18 to 39 | 99395 | Standard commercial billing |
Because Medicare eligibility is largely limited to people 65 and older, with a smaller group of younger beneficiaries qualifying through disability or certain conditions, the 18-to-39 age band that 99395 covers rarely overlaps with Medicare in the first place. The confusion shows up more often with 99396 and 99397, where a Medicare Advantage or supplemental plan may process a claim differently than traditional Medicare would.
Medicaid
Adult preventive coverage under Medicaid varies by state, since states have latitude in designing adult benefit packages. One piece stays consistent nationally: Medicaid’s Early and Periodic Screening, Diagnostic, and Treatment benefit (EPSDT) requires full-scope preventive care for enrollees under age 21. That means the 18-to-20 slice of the 99395 age range is federally guaranteed under Medicaid, while coverage for enrollees 21 through 39 depends on the individual state’s adult benefit design.
99395 RVU and wRVU values
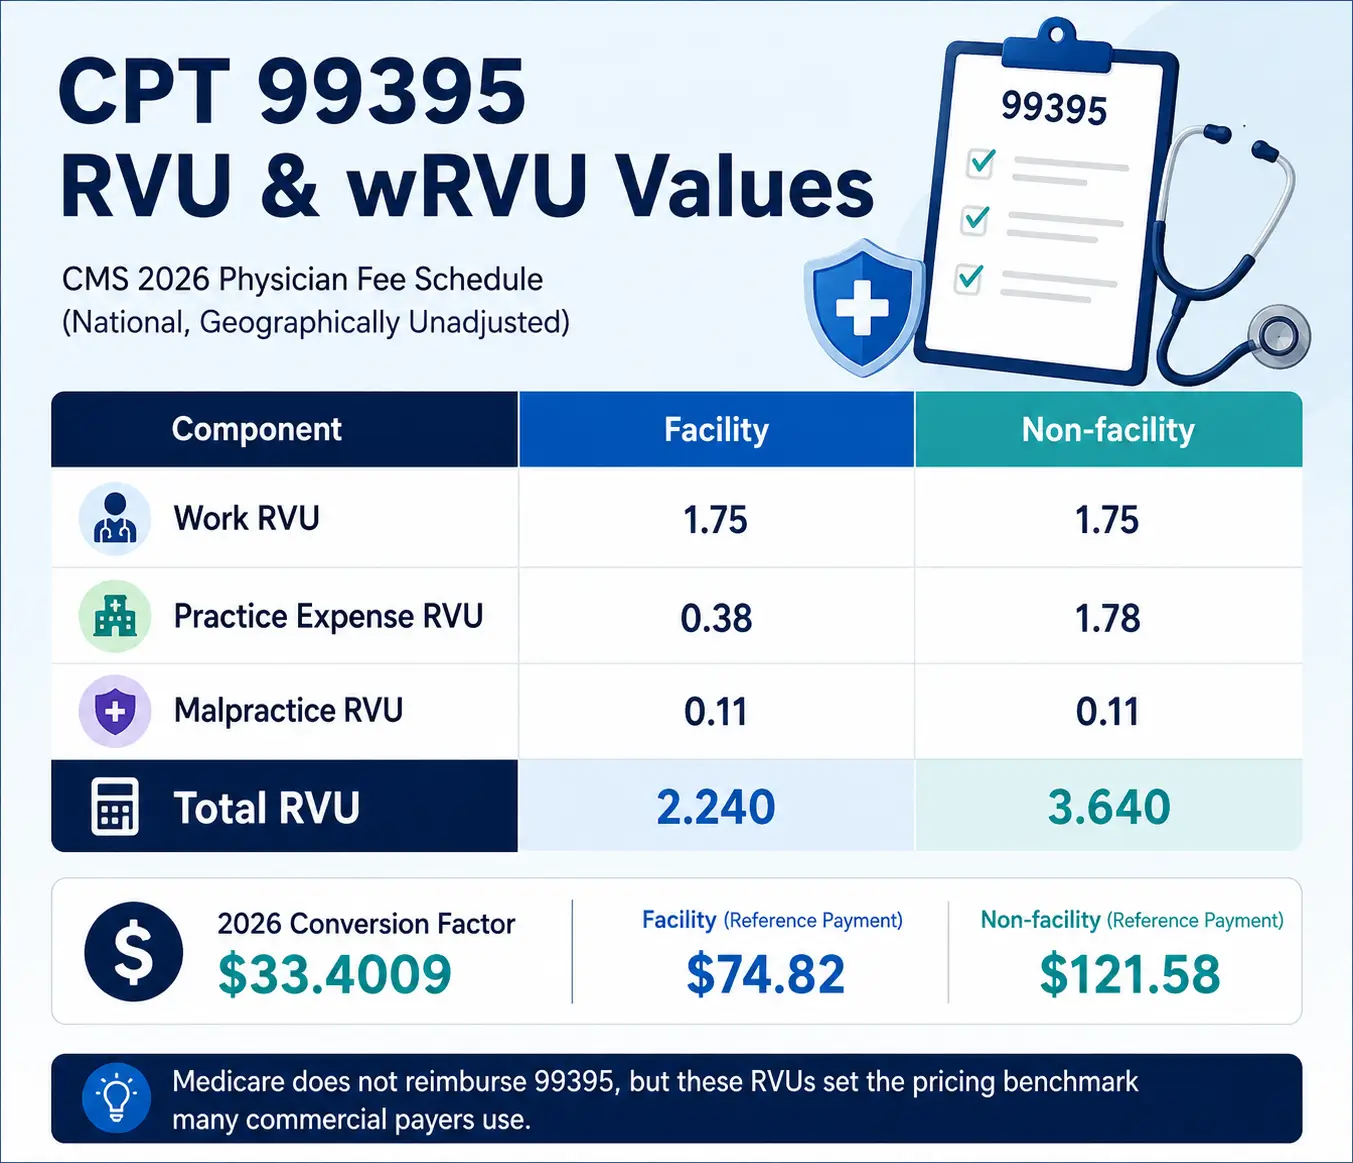
Relative value units drive both the Medicare-referenced price of a service and many physician compensation plans built around wRVU production. Under the CMS 2026 Physician Fee Schedule, 99395 carries these national, geographically unadjusted values:
Component | Facility | Non-facility |
Work RVU | 1.75 | 1.75 |
Practice expense RVU | 0.38 | 1.78 |
Malpractice RVU | 0.11 | 0.11 |
Total RVU | 2.240 | 3.640 |
Applying the 2026 conversion factor of $33.4009 works out to a national reference payment of roughly $74.82 in a facility setting and $121.58 in a non-facility (office) setting, before any geographic adjustment. Since Medicare doesn’t actually reimburse this code, those figures function as a pricing benchmark rather than a check Medicare cuts. Plenty of commercial payers and self-funded plans still peg preventive visit rates to the Medicare RBRVS structure, which is why a wRVU of 1.75 is worth knowing even for a code Medicare itself denies. Real-world commercial reimbursement for 99395 varies by payer, region, and contract terms, and can land well above or below the Medicare-referenced amount.
Modifier 25 and combining CPT 99395 with a problem-oriented E/M code
Is 99395 an E/M code?
Technically yes: it lives under the CPT Evaluation and Management Services heading. Functionally, though, it doesn’t behave like the E/M codes billers usually mean by that term. It isn’t leveled by history, exam, or medical decision-making, and it doesn’t compete with 99202 through 99215 for the same encounter unless a genuinely separate problem gets addressed.
Does CPT 99395 need a modifier?
Not on its own. A standalone preventive visit billed as 99395 needs no modifier. A modifier only becomes relevant when a separate, medically necessary problem is evaluated during the same visit, and in that case modifier 25 goes on the problem-oriented E/M code, not on 99395 itself.
Scenario | Codes billed | Modifier placement | Typical outcome |
Preventive exam only, no other issues addressed | 99395 | None | Paid as preventive, no cost-sharing |
Preventive exam plus a new complaint requiring real evaluation | 99395, 99213-25 or 99214-25 | Modifier 25 on the E/M code | Both payable when documentation shows two distinct services |
Preventive exam with a minor issue mentioned but not separately worked up | 99395 only | None | E/M code not separately payable |
So yes, 99395 and 99213 can be billed together, and so can 99395 and 99214, as long as the note supports a separately identifiable, medically necessary service beyond what the preventive exam already covers. Payers scrutinize this pairing closely because it’s a frequent source of overbilling, so the problem-oriented portion needs its own history, exam findings, and plan rather than a diagnosis code appended to the preventive note.
Common reasons 99395 claims get denied
- Wrong patient status: billing 99395 for a patient who actually qualifies as new (no visit with the group in the past three years), which should have gone out as 99385
- Age mismatch: the patient turned 40 (or was still under 18) on the date of service, requiring 99396 or 99394 instead
- Sent to the wrong payer: submitting 99395 to traditional Medicare instead of G0402, G0438, or G0439
- Frequency violation: billing 99395 again inside the payer’s 12-month window
- Misplaced modifier: attaching modifier 25 to 99395 itself instead of to the accompanying problem-oriented code
- Documentation mismatch: notes written like a problem-focused visit, which undermines the preventive classification even when the code choice is technically correct
Most of these are avoidable with a short verification step before the visit: confirm patient status, confirm age as of the date of service, and confirm the payer, since a Medicare beneficiary needs an entirely different code set. Catching those three details before the claim leaves the office resolves the majority of 99395 denials before they ever reach a claims scrubber, and it keeps a practice’s preventive visit revenue moving on the first submission instead of through an appeal.