


The 2026 CPT code set carries 418 editorial changes, including 288 new codes, 46 revisions, and 84 deletions, all effective January 1, 2026. Almost none of them touched pulmonary medicine. For anyone billing respiratory work, that is useful information, because it tells you where denials actually originate. They rarely come from a code you have never seen. They come from bundling rules, episode-of-care definitions, and payment status indicators that have been sitting in the National Correct Coding Initiative (NCCI) Policy Manual for years. This guide covers the CPT codes for respiratory services that generate the most edits, and the rule attached to each one.
How CPT codes for respiratory services are organized
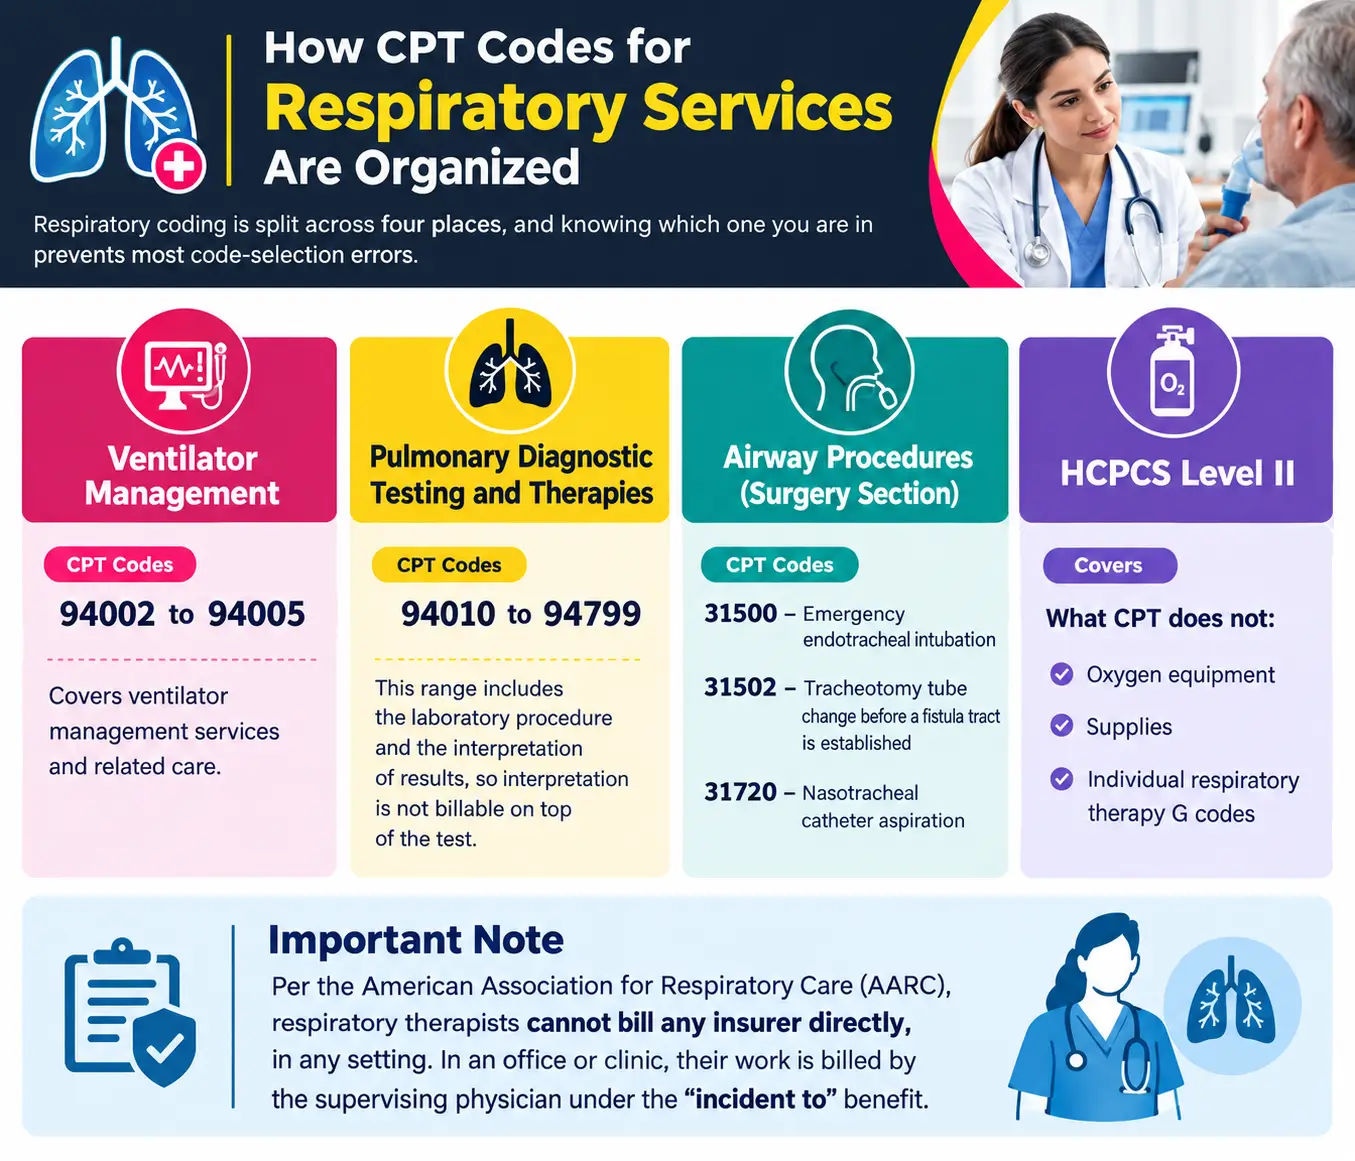
Respiratory coding is split across four places, and knowing which one you are in prevents most code-selection errors.
- Ventilator management: 94002 to 94005.
- Pulmonary diagnostic testing and therapies: 94010 to 94799. CPT states that this range includes the laboratory procedure and the interpretation of results, so interpretation is not billable on top of the test.
- Airway procedures in the Surgery section: 31500 (emergency endotracheal intubation), 31502 (tracheotomy tube change before a fistula tract is established), 31720 (nasotracheal catheter aspiration).
- HCPCS Level II, which covers what CPT does not: oxygen equipment, supplies, and the individual respiratory therapy G codes.
One structural point shapes everything below. Per the American Association for Respiratory Care (AARC), respiratory therapists cannot bill any insurer directly, in any setting. In an office or clinic, their work is billed by the supervising physician under the “incident to” benefit.
Mechanical ventilation CPT code selection and the E/M conflict
The mechanical ventilation CPT code you report depends entirely on place of service and day of care:
- 94002 is initial day, hospital inpatient or observation
- 94003 is each subsequent day in the same setting
- 94004 is nursing facility, per day
- 94005 covers home ventilator management supervision by a physician or other qualified health care professional
Now the part that costs practices money. Ventilator management CPT codes (94002 to 94004, along with 94660 and 94662) are not separately reportable with evaluation and management services. This is not a new NCCI position, either. It traces to the Federal Register, Volume 58, Number 230, December 2, 1993, pages 63640 to 63641. When a ventilator management CPT code and an E/M code appear on the same claim for the same date, only the E/M is payable. The same logic bundles ventilator management into critical care codes 99291 and 99292.
Two setting-specific traps follow from this. Do not report 94003 for a ventilator managed in the emergency department, since the ED is neither an inpatient nor an observation area. If that ED patient is admitted as an inpatient at the same facility, 94002 becomes reportable. Second, there is no CPT code that specifically describes noninvasive ventilation (BiPAP) in the hospital. Facilities split between 94660 and the ventilator management codes, so confirm your facility’s convention rather than assuming.
For home care, 99503 reports a home visit for respiratory therapy care and 99504 reports a home visit for mechanical ventilation care. Billing 99504 for a patient on supplemental oxygen who is not ventilated is a straightforward denial on record review.
Breathing treatment CPT code rules that drive nebulizer denials

CPT 94640 covers pressurized or nonpressurized inhalation treatment for acute airway obstruction, or inhalation used to induce sputum for diagnosis. It applies to aerosol generators, nebulizers, metered-dose inhalers, and IPPB devices.
The NCCI rule is stricter than most coders expect: 94640 shall be reported only once during an episode of care, regardless of how many separate inhalation treatments are given. An episode begins when the patient arrives at the facility and ends when the patient leaves. If it spans more than one calendar day, you still report one unit for the whole episode. Only when a patient leaves and returns for a genuinely separate episode on the same date may you report the second treatment with modifier 76 appended.
For longer therapy, the code changes rather than the units.
Total continuous treatment time | Codes to report |
Under 60 minutes | 94640 |
60 to 90 minutes | 94644 |
91 to 150 minutes | 94644 + 94645 |
151 to 210 minutes | 94644 + 94645 x 2 |
Medicare will not pay both 94640 and 94644/94645 on the same day for the same patient, so the coder picks one path. Start and stop times must be in the record to support 94644. Note also that 94644 carries no physician work RVUs. When the service is performed in a facility using facility staff and supplies, the physician has no related practice expense and should not report it.
Two more edits worth memorizing. CPT 94060 (bronchodilation responsiveness) already includes administration of the bronchodilator, so reporting 94640 for that administration is misuse of the code, although the drug itself is separately reportable. And 94664, demonstration or evaluation of inhaler or nebulizer technique, may be reported only once per day and is bundled into 94640 when the same device is used at the same encounter.
Pulmonary function test CPT code combinations
There is no single “complete PFT” code. A full study is assembled from components, and the components carry mutually exclusive edits.
- 94010 spirometry, including graphic tracing and total and timed vital capacity
- 94060 bronchodilation responsiveness, pre- and post-bronchodilator
- 94200 maximum breathing capacity, maximal voluntary ventilation
- 94375 respiratory flow volume loop
- 94726 plethysmography for lung volumes and, when performed, airway resistance
- 94727 gas dilution or washout for lung volumes
- 94728 airway resistance by impulse oscillometry
- 94729 diffusing capacity, an add-on code reported with 94010, 94060, 94070, 94375, or 94726 to 94728
Do not report 94010 with 94150, 94200, 94375, or 94728. The reasoning appears in NCCI Chapter 11: a flow volume loop is an alternative method of calculating a standard spirometric parameter, so 94375 is already inside standard spirometry. Similarly, when multiple spirometric determinations are needed to complete a service such as 94070 (bronchospasm provocation), that is still one unit of service.
Cardiopulmonary exercise testing (94621) absorbs its components. Venous access, ECG monitoring, spirometry before and after exercise, oximetry, O2 consumption, and CO2 production are not separately reportable at the same encounter, and neither is the simple pulmonary stress test.
That simple test is 94618, which CMS put in place effective January 1, 2018 when CPT deleted 94620. Claims submitted with 94620 after that date deny. Use 94617 for exercise testing to detect bronchospasm; the inhaled bronchodilator cannot be coded separately there either, though the medication is a billable supply. Oxygen uptake codes 94680, 94681, and 94690 are not reportable in conjunction with 94621. When nothing fits, 94799 is the unlisted pulmonary service code, and it requires a supporting report.
CPT code for oxygen therapy and oxygen administration
There is no CPT code for oxygen administration in the office. Oxygen given during a visit or procedure is part of that service.
Home oxygen moves to HCPCS Level II and is billed by the DME supplier, not the practice: E0424 (stationary compressed gaseous system, rental), E0431 (portable gaseous system, rental), and E1390 (oxygen concentrator) are the workhorses. Coverage follows NCD 240.2 and LCD L33797. The core qualifying threshold is an arterial PO2 at or below 55 mm Hg, or arterial oxygen saturation at or below 88 percent, taken at rest while awake and breathing room air. A second group qualifies at PO2 of 56 to 59 mm Hg or saturation of 89 percent with specified comorbidities such as dependent edema.
Documentation timing is where these claims fail. E0424, E0431, E0433, E0434, E0439, and E0441 through E0444 require a written order prior to delivery. For concentrators (E1390, E1391, E1392, K0738), CMS instead expects documentation that the treating physician saw and evaluated the beneficiary within 30 days before the initial certification date.
Oximetry CPT code and peak flow: two frequent write-offs
CPT 94760 (single determination) and 94761 (multiple determinations) carry a payment status indicator of T. If any other service payable under the physician fee schedule is billed on the same date by the same provider, oximetry is bundled into it. CMS reached this position because a pulse oximetry reading is closer to a vital sign than a diagnostic test; 94760 carries roughly 0.07 total RVUs against about 1.34 for a 99213. Only 94762, continuous overnight monitoring, behaves like a standalone study. Also note that 94625 and 94626 are not reportable with 94760 or 94761, and neither is car seat testing (94780, 94781).
There is no peak flow CPT code, and none for incentive spirometry. Peak flow measurement is not separately billable. The meter itself is covered as a supply under HCPCS A4614 when furnished in the office for home use.
Chest physiotherapy CPT code and airway clearance
Hands-on chest wall manipulation, meaning cupping, percussion, and vibration, is reported with 94667 for the initial demonstration or evaluation, billable once per day, and 94668 for subsequent sessions. When a device delivers high-frequency chest wall oscillation, the correct code is 94669, reported per session.
For suctioning, 31720 describes catheter aspiration through the nose and pharynx into the trachea. It is assigned 1.06 physician work RVUs, which signals a practitioner-level procedure rather than routine care. No CPT code exists for nasopharyngeal suctioning; that is treated as a component of the E/M service.
CPT code for pulmonary rehab and individual respiratory therapy
CMS deleted HCPCS G0424 effective December 31, 2021. Since January 1, 2022, outpatient pulmonary rehabilitation is reported with 94625 (without continuous oximetry monitoring, per session) or 94626 (with continuous oximetry monitoring, per session).
The session rules are specific. No more than two one-hour sessions may be billed in a single day. One session requires at least 31 minutes of treatment; billing two sessions on the same day requires at least 91 minutes. Services are covered only in a physician office or hospital outpatient department. Eligibility runs to moderate through very severe COPD, GOLD stages II to IV, and since January 1, 2022 also to beneficiaries with confirmed or suspected COVID-19 who have had persistent respiratory symptoms for at least four weeks.
Patients who do not meet those criteria are not billed with 94625 or 94626. Their care falls under individual respiratory therapy services: G0237 and G0238 in 15-minute one-on-one increments, and G0239 for group sessions of two or more patients. G0239 is not a timed code and is reported once per day per patient. Coverage for this subset is set by local coverage determinations, which vary by Medicare Administrative Contractor.
The 2027 change already worth preparing for
Sleep testing is the exception to an otherwise quiet code set. The AMA CPT Editorial Panel approved deletion of 95800, 95801, and 95806 at its February 2025 meeting, effective January 1, 2027, replacing them with six complexity-tiered codes that separate technical and professional work. CMS addressed valuation in the CY2027 Physician Fee Schedule proposed rule published July 16, 2026, with a comment period running to September 14, 2026. The three legacy codes remain billable through December 31, 2026, but documentation should already be capturing device type and channel counts, because the replacement codes sort studies by the physiologic signals recorded rather than by device.
Accuracy in respiratory billing comes down to a short list of habits: check the NCCI edit before pairing any two pulmonary codes, count episodes of care rather than treatments for 94640, confirm place of service before choosing a ventilator code, and verify the LCD for anything oxygen related. The CPT codes for respiratory services change little from year to year. The rules governing how they combine are where the revenue is won or lost.