

If you came here expecting a rebuilt EEG code set, the news is quieter than most 2026 coding roundups suggest. The EEG CPT codes in Category I carried over from 2025 without renumbering. What did change sits in two places: a handful of new Category III codes for implanted continuous monitoring, and a set of Medicare payment policies that will cut real dollars from hospital-based epilepsy programs even though the conversion factor went up.
That gap between “the codes are the same” and “the payment is not” is where most billing errors will happen this year.
What actually changed in the 2026 CPT code set
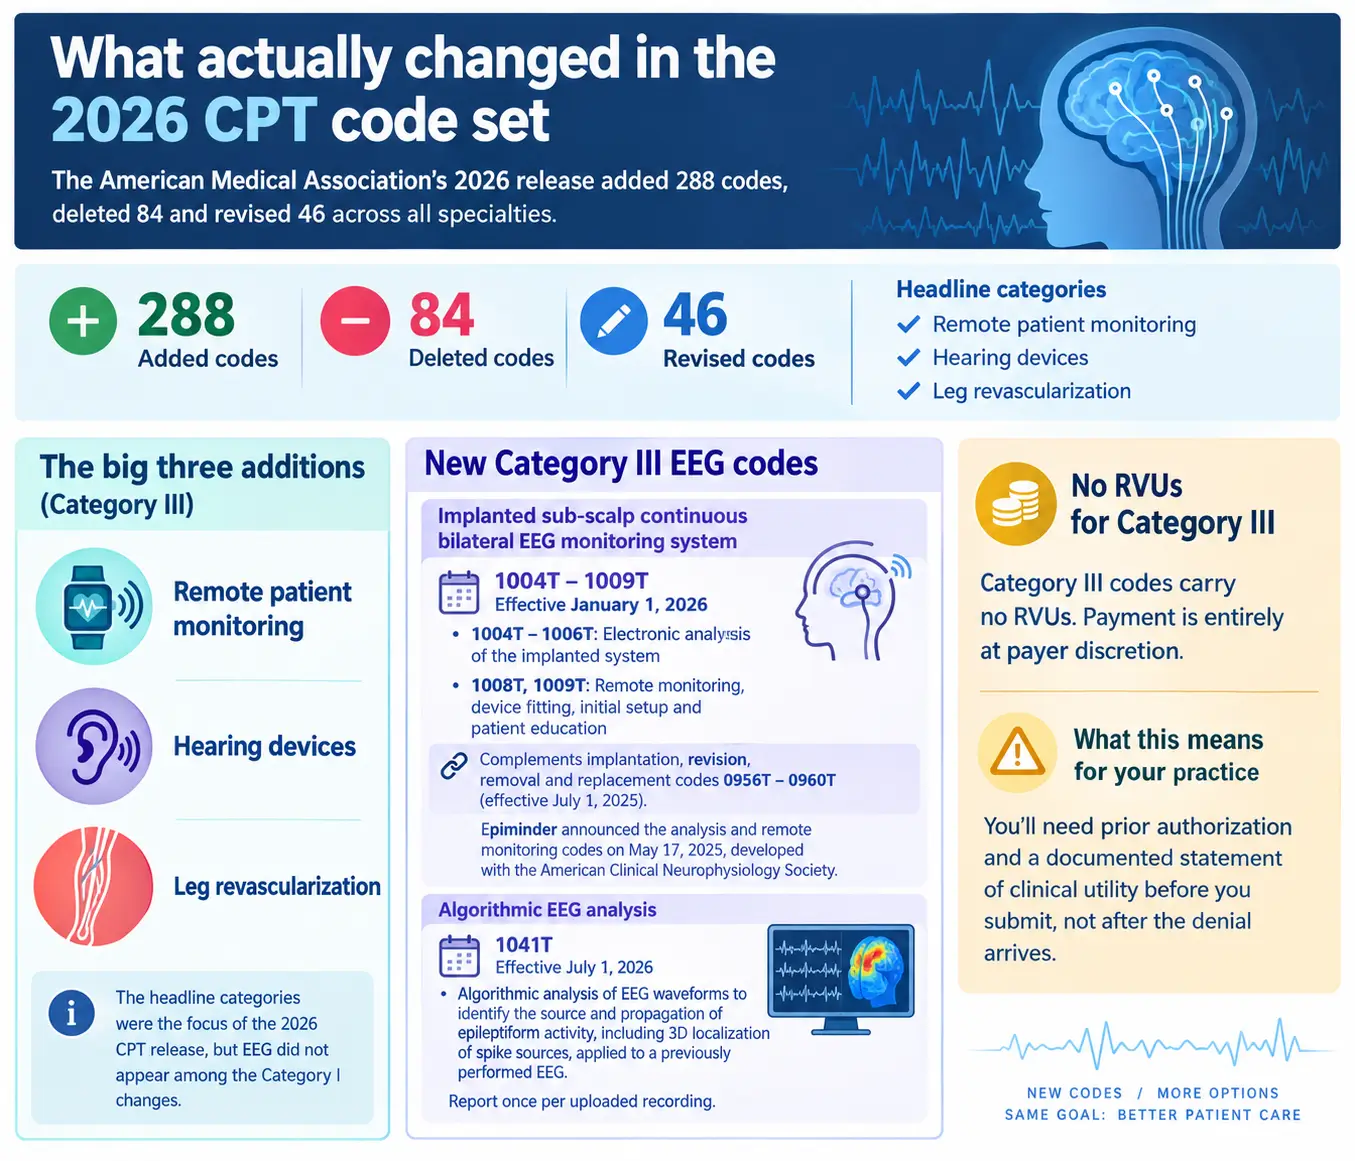
The American Medical Association’s 2026 release added 288 codes, deleted 84 and revised 46 across all specialties. The headline categories were remote patient monitoring, hearing devices and leg revascularization. EEG did not appear among the Category I changes, and when Gregory L. Barkley, MD, presented the 2026 coding update at the American Epilepsy Society annual meeting in Atlanta on December 8, 2025, his session on video EEG rules covered the same 95700 through 95726 descriptors that took effect in 2020.
The additions landed in Category III instead.
Codes 1004T through 1009T took effect January 1, 2026 for services tied to an implanted sub-scalp continuous bilateral EEG monitoring system. The range splits into electronic analysis of the implanted system (1004T to 1006T) and remote monitoring, including device fitting, initial setup and patient education (1008T, 1009T). These complement the implantation, revision, removal and replacement codes 0956T through 0960T, which became reportable July 1, 2025. Epiminder announced the creation of the analysis and remote monitoring codes on May 17, 2025, developed in partnership with the American Clinical Neurophysiology Society.
A second addition, 1041T, became effective July 1, 2026. It describes algorithmic analysis of EEG waveforms to identify the source and propagation of epileptiform activity, including 3D localization of spike sources, applied to a previously performed EEG. CPT instructs that it be reported once per uploaded recording.
Category III codes carry no RVUs. Payment is entirely at payer discretion, which means prior authorization and a documented statement of clinical utility before you submit, not after the denial arrives.
The 2026 payment changes matter more than the code changes
For the first time, Medicare runs two conversion factors. CMS finalized $33.5675 for qualifying Alternative Payment Model participants and $33.4009 for everyone else, increases of 3.77 percent and 3.26 percent over the 2025 factor of $32.3465. The bump comes largely from a one-year 2.5 percent increase enacted in the One Big Beautiful Bill Act.
Two other policies pull the opposite direction.
CMS finalized a -2.5 percent efficiency adjustment applied to work RVUs and the intraservice portion of physician time for non-time-based services. Barkley’s AES presentation listed the affected neurophysiology codes directly: 95812, 95813, 95816, 95819, 95822, 95829, 95836, 95954, 95957, 95958, 95965 and 95966. Time-based codes, E/M services and codes on the telehealth list were exempted.
CMS also cut the portion of facility practice expense RVUs allocated on work RVUs to half the non-facility amount. Susan T. Herman, MD, of the Barrow Neurological Institute, summarized the practical result in the same AES session: a 7 to 10 percent decrease in RVUs for facility-based services against a 4 percent increase for non-facility services. An outpatient neurology office and a hospital-based epilepsy monitoring unit will experience 2026 very differently.
Routine EEG CPT codes
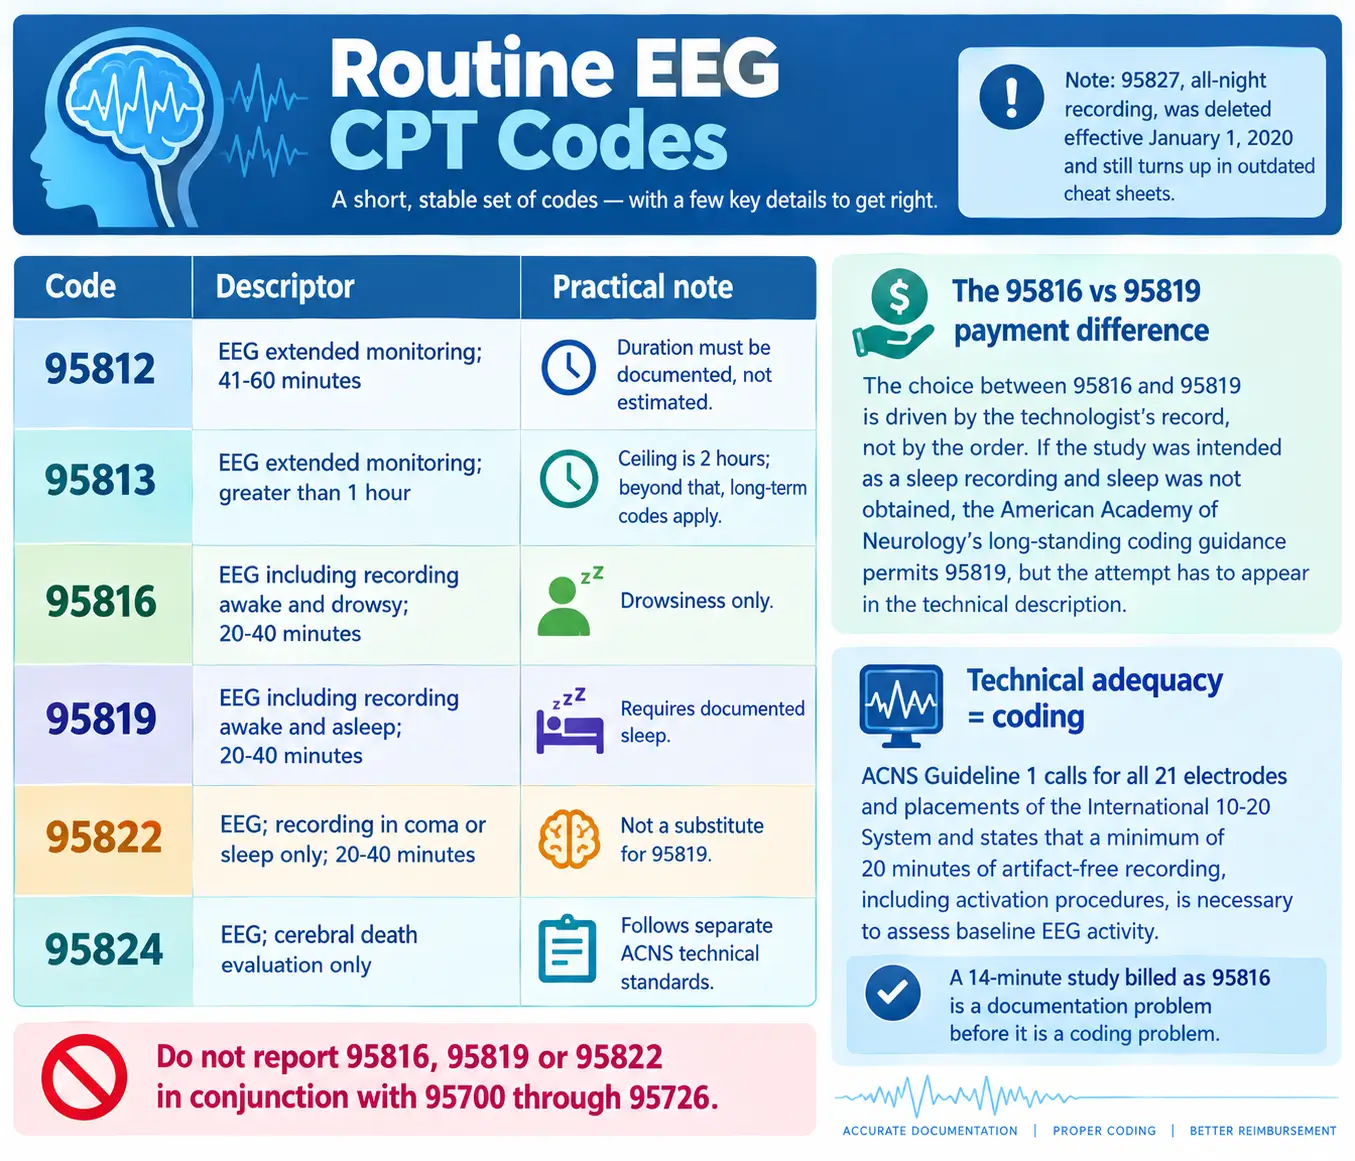
The routine set is short and stable. Note that 95827, all-night recording, was deleted effective January 1, 2020 and still turns up in outdated cheat sheets.
Code | Descriptor | Practical note |
95812 | EEG extended monitoring; 41-60 minutes | Duration must be documented, not estimated |
95813 | EEG extended monitoring; greater than 1 hour | Ceiling is 2 hours; beyond that, long-term codes apply |
95816 | EEG including recording awake and drowsy; 20-40 minutes | Drowsiness only |
95819 | EEG including recording awake and asleep; 20-40 minutes | Requires documented sleep |
95822 | EEG; recording in coma or sleep only; 20-40 minutes | Not a substitute for 95819 |
95824 | EEG; cerebral death evaluation only | Follows separate ACNS technical standards |
The 95816 versus 95819 choice drives a real payment difference, and it is decided by the technologist’s record, not by the order. If the study was intended as a sleep recording and sleep was not obtained, the American Academy of Neurology’s long-standing coding guidance permits 95819, but the attempt has to appear in the technical description.
Technical adequacy is not a separate issue from coding. ACNS Guideline 1 calls for all 21 electrodes and placements of the International 10-20 System and states that an absolute minimum of 20 minutes of artifact-free recording, including activation procedures, is necessary to assess baseline EEG activity. A 14-minute study billed as 95816 is a documentation problem before it is a coding problem.
Do not report 95816, 95819 or 95822 in conjunction with 95700 through 95726.
Ambulatory, video and continuous EEG CPT codes
Anything recorded beyond two hours moves into the long-term family created in 2020, which replaced 95950, 95951, 95953 and 95956. The structure has three layers.
Setup (95700). Continuous recording with video when performed, setup, patient education and takedown, administered in person by an EEG technologist, minimum of 8 channels. Report it once per recording period, not once per day. CPT is explicit that “in person” means the technologist is physically present. For patient-placed electrode sets, or setup by a non-technologist or one supervised remotely, report 95999 instead.
Technical monitoring (95705-95716). Selection turns on three variables: with or without video, duration tier (2-12 hours, or each increment greater than 12 up to 26 hours), and monitoring level (unmonitored, intermittent, or continuous real-time). The monitoring level claimed must match what the technologist log shows.
Professional interpretation (95717-95726). Four variables here, and the two that get missed are not duration and video. They are when the report was generated and whether the physician had access to the data during the recording.
- 95717 and 95718 cover 2-12 hours and may be reported a maximum of once per entire long-term service, either for a study that lasted only 2-12 hours or for the final partial increment of a longer study.
- 95719 and 95720 cover each increment greater than 12 up to 26 hours with a report after each 24-hour period. There is no cap. A 21-day admission with 21 daily reports supports 95720 x 21.
- 95721 through 95726 apply only when the total recording exceeds 36 hours and the entire professional interpretation is produced after the recording finishes. Never report them alongside 95717 through 95720.
A 72-hour ambulatory study with daily reads is therefore 95700 once, the appropriate technical increments, and 95720 x 3 (or 95719 x 3 without video). If the final segment runs 8 hours, that final piece becomes a single unit of 95718 or 95717.
One Medicare rule catches practices repeatedly. Palmetto GBA’s billing and coding article A56771, which supports LCD L33447, requires that a routine EEG described by 95812, 95813, 95816, 95819 or 95822 be performed before an ambulatory continuous EEG, with the routine EEG claim submitted for a date of service within one year of the ambulatory study.
Related codes that get overlooked
- 95957, digital analysis of EEG for epileptic spike analysis, the code most people mean by QEEG. CPT prohibits reporting it for automated software; when automated spike and seizure detection accompanies long-term EEG, that work belongs to 95700-95726. Barkley’s guidance is to reserve it for special circumstances such as surgical planning, once per session.
- 95829, electrocorticogram at surgery. 95830, insertion of sphenoidal electrodes.
- 95836, electrocorticogram from an implanted brain neurostimulator pulse generator, with interpretation and report, up to 30 days.
- 61760, stereotactic implantation of depth electrodes into the cerebrum for long-term seizure monitoring, the surgical component of a stereo-EEG evaluation.
EEG documentation requirements for 2026
The technical description is not boilerplate. CPT specifies its required elements for the monitoring codes: uploading or transferring data from the equipment to a server or storage device, reviewing raw data and events along with automated detections and patient activations, and annotating, editing and archiving the record for physician review. For unmonitored services, the technologist annotates and creates a single summary.
Build the report around what a reviewer will look for:
- Recording start and stop times, and total duration
- Number of channels, electrode system used, and any additional or special electrodes
- Activation procedures performed (hyperventilation, photic stimulation, sleep deprivation) and whether sleep was achieved
- Video present or absent, stated explicitly
- Monitoring level and who performed setup
- Filter settings and sensitivity used on review, per ACNS Guideline 7
- Description of the record kept separate from the interpretation and clinical correlation
Component billing is the other frequent failure point. Bill modifier 26 for interpretation only, TC for the technical side, and neither when your practice owns the equipment and reads the study globally. When an E/M service and an EEG interpretation occur on the same date, modifier 25 goes on the E/M code and the encounter needs two separate notes.
Front-end documentation also decides admission status. Deepti Zutshi, MD, reported at the same December 2025 AES session that adding payer inpatient criteria directly into EMU admission orders and daily notes took her six-bed unit from 18 denials in three months to one. The criteria she cited come from published policies including Molina Clinical Policy 133 and UnitedHealthcare 2025T0596N, which generally cap outpatient video EEG at 48 to 72 hours before inpatient monitoring can be authorized.
For 2026, the codes will not trip you up. The pairing of a higher conversion factor with a 2.5 percent efficiency cut on 95812, 95813, 95816, 95819, 95822, 95836 and 95957, plus a facility practice expense reduction of 7 to 10 percent, means the same clean claim returns less in a hospital setting than it did last year. Practices that audit their pro-tech splits, their monitoring-level documentation and their day counts against actual recording time will keep more of what they earn than those that only update the code list.