


According to the Centers for Disease Control and Prevention, fungal nail infections affect up to 14% of the general population. The prevalence increases significantly among older adults and patients with compromised immune systems. Accurate diagnosis coding ensures medical practices track these infections properly while securing appropriate payment for treatment. Medical billers and healthcare providers rely on the Tinea Unguium ICD-10 framework to classify these dermatophyte infections of the nail plate. This guide details the specific codes, documentation standards, and billing rules that govern onychomycosis claims.
Understanding tinea unguium and onychomycosis in ICD-10
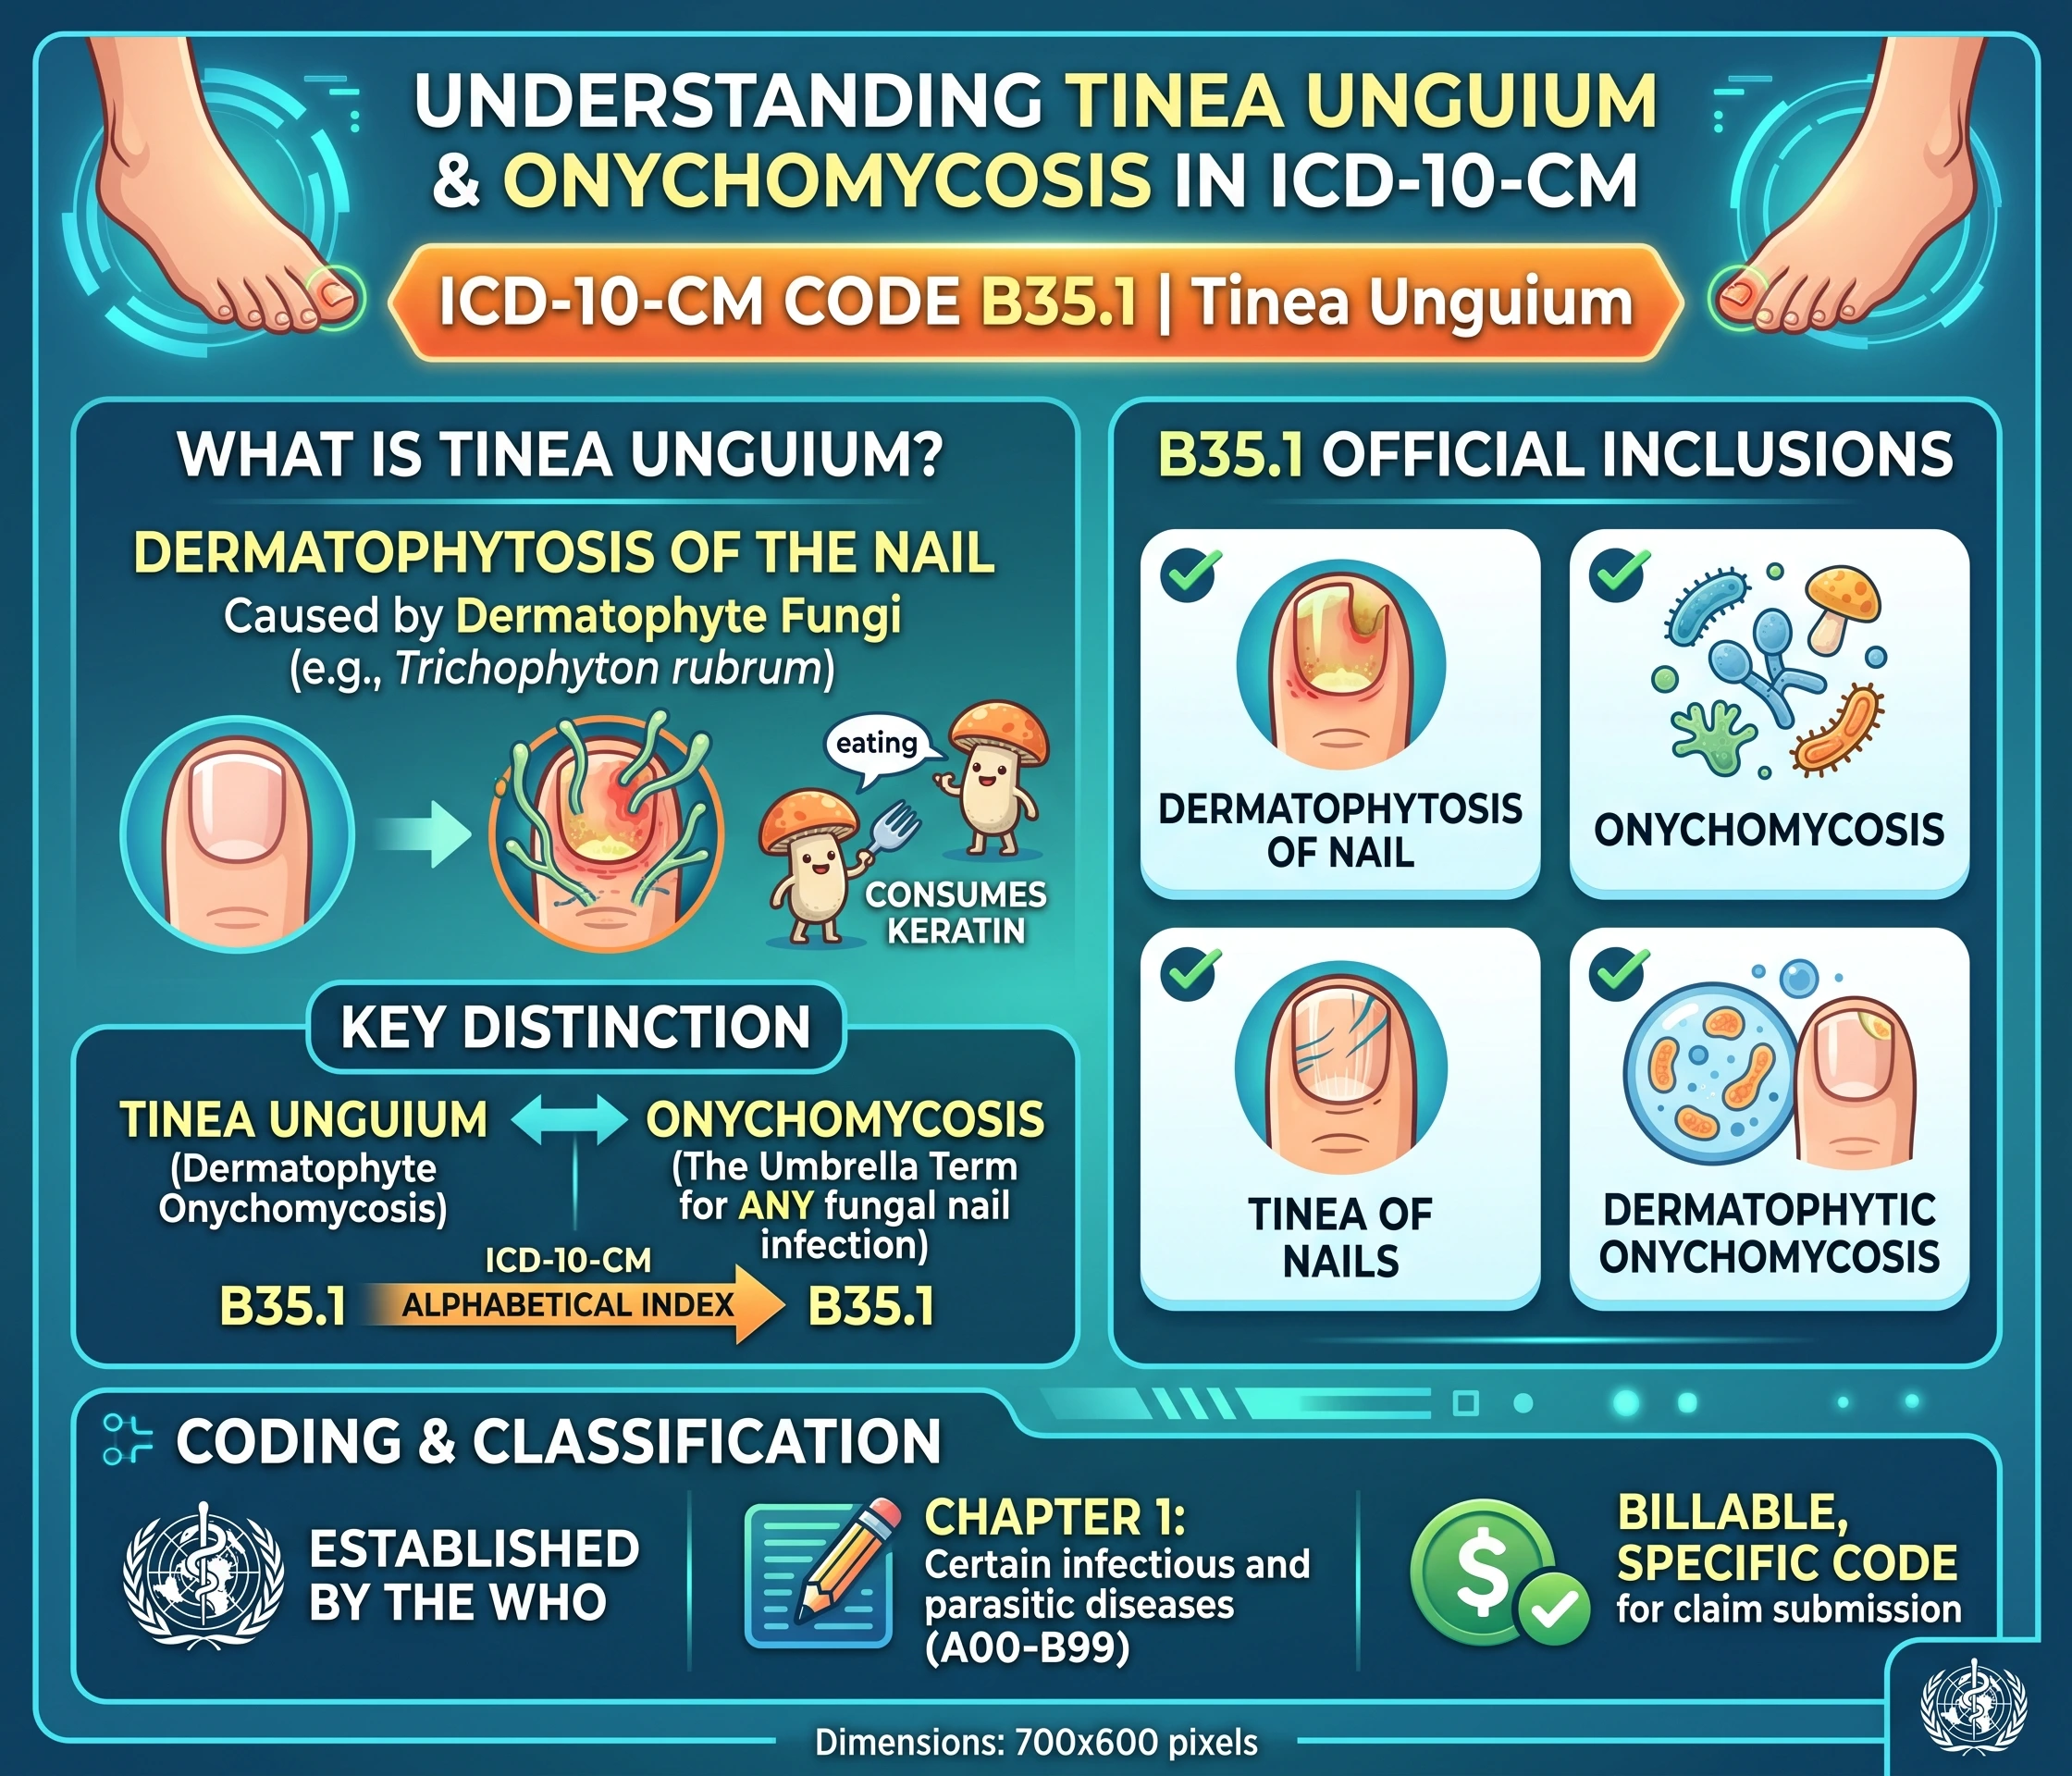
The World Health Organization established the ICD-10-CM code B35.1 for tinea unguium. This code classifies dermatophytosis of the nail. Medical coders use B35.1 to report fungal infections caused by dermatophyte fungi, which consume keratin in the nail bed and plate.
Many providers ask if tinea unguium is the same as onychomycosis. Onychomycosis serves as the umbrella clinical term for any fungal nail infection. Tinea unguium specifically describes onychomycosis caused by dermatophytes, such as Trichophyton rubrum. The ICD-10-CM alphabetical index directs coders to assign B35.1 for both terms.
Under the B35.1 diagnosis code, the official inclusions cover:
- Dermatophytosis of nail
- Onychomycosis
- Tinea of nails
- Dermatophytic onychomycosis
Coders must note that B35.1 falls under Chapter 1: Certain infectious and parasitic diseases (A00-B99). It is a billable, specific code valid for claim submission.
Clinical documentation requirements for B35.1
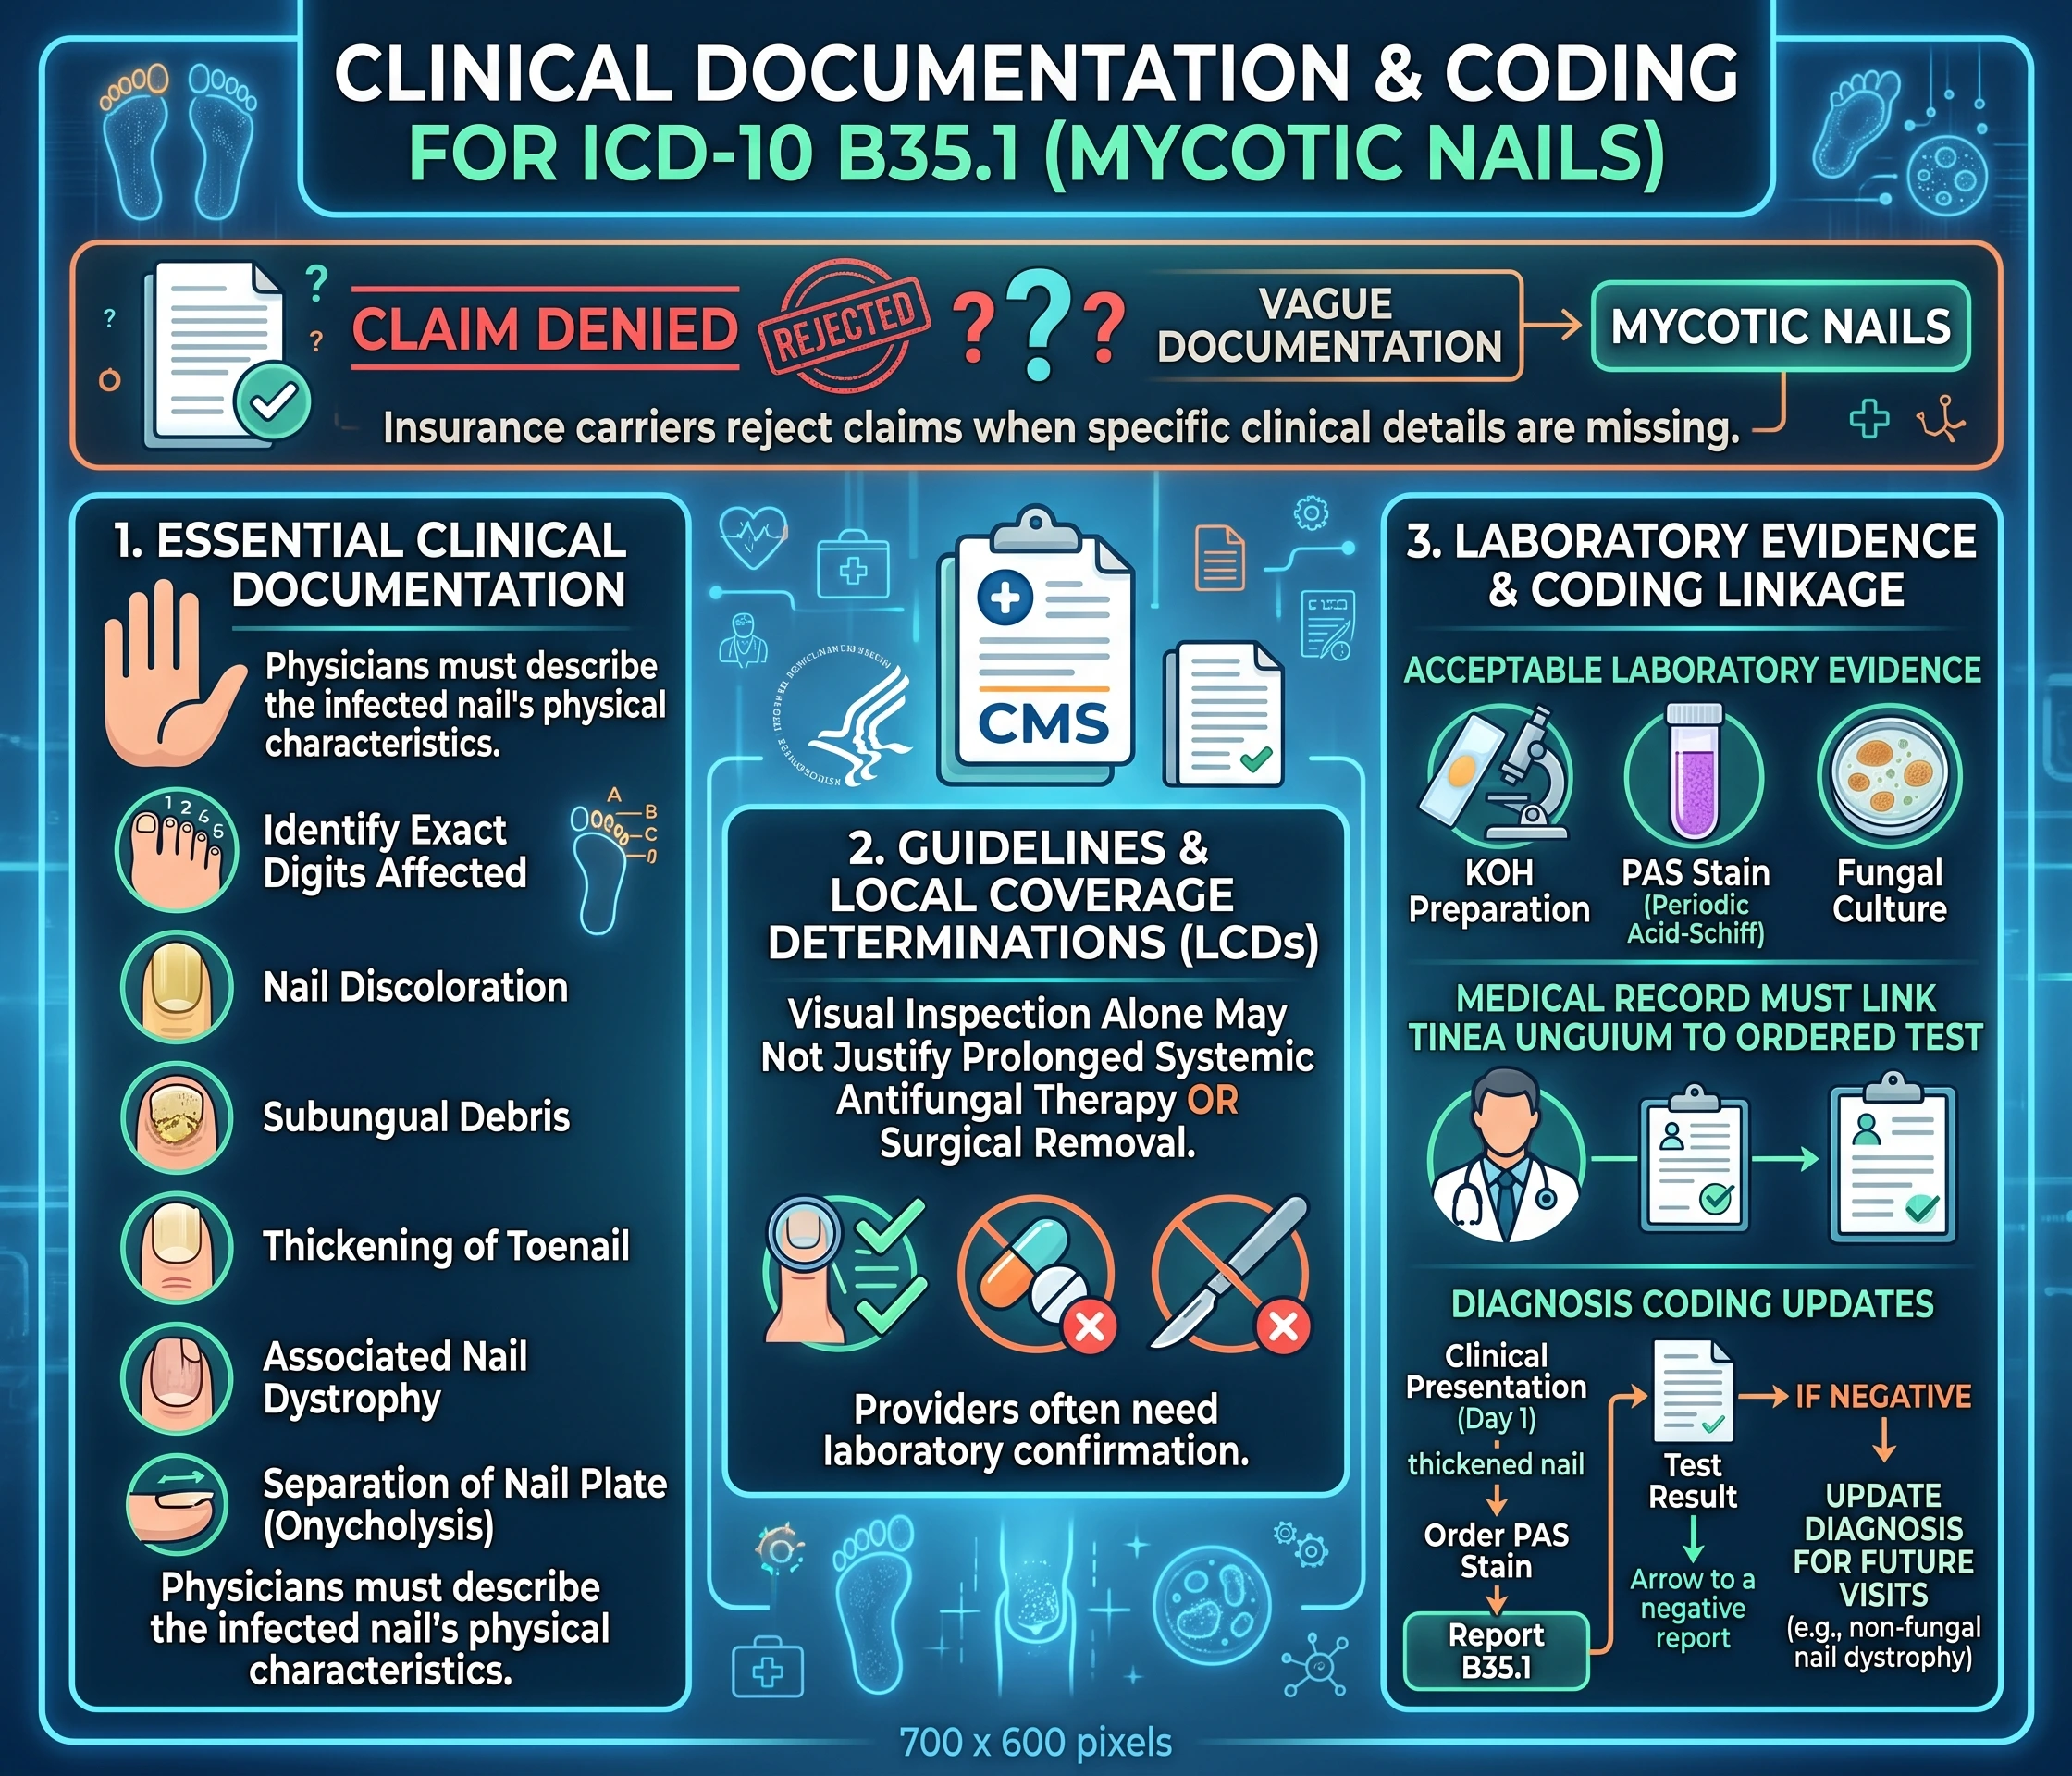
Insurance carriers deny claims for mycotic nails when the medical record lacks specific clinical details. To support the B35.1 ICD-10 code, physicians must describe the physical characteristics of the infected nail. Vague documentation leads to immediate claim rejections.
Clinical notes should identify the exact digits affected. Documentation must describe the visual evidence of the fungal nail infection, which typically includes nail discoloration, subungual debris, and thickening of the toenail. Providers should also record any associated nail dystrophy or separation of the nail plate from the bed, known clinically as onycholysis.
Medicare Administrative Contractors frequently publish Local Coverage Determinations that outline strict documentation requirements for podiatry and dermatology services. According to the Centers for Medicare & Medicaid Services guidelines for routine foot care, visual inspection alone may not always justify prolonged systemic antifungal therapy or surgical nail removal. Providers often need to document laboratory confirmation.
Laboratory confirmation and diagnosis coding
Acceptable laboratory evidence includes a positive potassium hydroxide (KOH) preparation, a Periodic Acid-Schiff (PAS) stain, or a formal fungal culture. When billing for the diagnosis and the subsequent laboratory tests, the medical record must explicitly link the suspected tinea unguium to the ordered test.
If a physician orders a PAS stain for a thickened nail, the coder initially reports B35.1 based on the clinical presentation. If the laboratory report returns negative for fungal elements, the coder must update the diagnosis code for future visits to reflect a non-fungal nail dystrophy.
Medicare reimbursement issues and medical necessity
Billing for a toenail infection carries high audit risk. Medicare and most commercial payers consider routine foot care a non-covered service. Cutting or removing corns, calluses, and trimming nails falls under this exclusion unless specific criteria are met.
To establish medical necessity for treating tinea unguium, the patient must experience distinct physical limitations or secondary medical complications. Pain serves as the primary qualifier. The documentation must state that the mycotic toenails cause marked pain or limit the patient’s ability to walk. The physician should note if the thickened nails cause pressure against footwear.
Secondary infection risk provides another pathway for coverage. Patients with systemic conditions like diabetes mellitus, peripheral neuropathy, or chronic thrombophlebitis face a high risk of losing a limb from minor foot trauma. When treating a diabetic patient for B35.1, the coder usually lists the systemic condition first, followed by the tinea unguium diagnosis code.
Using class findings and Q modifiers
When submitting claims for mycotic nail debridement (CPT codes 11720 or 11721), billers append specific modifiers to demonstrate the severity of the patient’s systemic disease. The Centers for Medicare & Medicaid Services designates three modifiers for this purpose.
Q7: Indicates one Class A finding (e.g., non-traumatic amputation of a foot or integral skeletal portion).
Q8: Indicates two Class B findings (e.g., absent posterior tibial pulse and absent dorsalis pedis pulse).
Q9: Indicates one Class B and two Class C findings (e.g., claudication, temperature changes, edema).
If the provider bills B35.1 based solely on pain and not systemic disease, the Q modifiers do not apply. The physician must instead document the exact nature of the pain and the limitations it places on the patient’s daily activities.
Prior authorization for antifungal medications
Accurate ICD-10 coding extends beyond procedural reimbursement. Pharmacy benefit managers require precise diagnosis codes to authorize expensive topical and oral antifungal medications.
Newer topical treatments often cost hundreds of dollars per bottle. Insurance companies require the B35.1 code along with proof of a positive fungal laboratory test before approving these prescriptions. Payer step-therapy protocols frequently mandate that the patient try and fail a less expensive oral medication, such as generic terbinafine, before approving brand-name topical solutions.
The medical biller must ensure the clinical note contains the B35.1 diagnosis, the date of the positive lab test, and a record of any previous failed treatments. Submitting a prior authorization request with an unspecified nail disorder code usually results in an automatic pharmacy denial.
Comparing B35.1 to related ICD-10-CM codes
Medical coders must distinguish tinea unguium from other dermatological conditions that affect the nails. Using the wrong code leads to claim denials and incorrect patient medical histories.
Diagnosis | ICD-10 Code | Distinguishing Feature |
Tinea unguium | B35.1 | Fungal infection of the nail plate (onychomycosis) |
Tinea pedis | B35.3 | Dermatophyte infection of the foot skin (Athlete’s foot) |
Candidiasis of nails | B37.2 | Nail infection caused specifically by Candida yeast |
Psoriasis, unspecified | L40.9 | Autoimmune condition causing nail pitting and thickening |
Dystrophia unguium | L60.3 | Non-infectious abnormal nail formation |
If a patient presents with both athlete’s foot and toenail fungus, the coder should report both B35.1 and B35.3. Psoriasis of the nails frequently mimics tinea unguium visually. If laboratory tests return negative for dermatophytes, the provider must amend the diagnosis to reflect the actual pathology, such as L60.3 or L40.9.
Practical coding and billing scenarios
Applying the correct ICD-10 code for tinea unguium requires understanding the clinical context. Reviewing practical scenarios helps clarify the billing guidelines for medical coders and providers.
Scenario A: Diabetic patient with systemic risk
A 68-year-old patient with type 2 diabetes and peripheral neuropathy visits the podiatrist. The physician notes severely thickened, discolored nails on both great toes. The patient denies pain but lacks sensation in the feet. The physician debrides the nails to prevent ulceration. The coder reports E11.40 (Type 2 diabetes mellitus with diabetic neuropathy, unspecified) as the primary diagnosis, followed by B35.1 (Tinea unguium). The biller appends the appropriate Q modifier to the debridement CPT code to indicate the systemic risk factors.
Scenario B: Healthy patient with painful mycotic nails
A 45-year-old healthy patient complains of sharp pain in the left great toe when wearing closed shoes. The physician observes subungual debris and a brittle nail plate. A KOH test confirms dermatophyte infection. The physician prescribes oral terbinafine and debrides the nail. The coder reports B35.1 as the sole diagnosis. The clinical note detailing the pain and shoe interference provides the medical necessity for the debridement without needing systemic class findings.
Scenario C: Cosmetic concern only
A 30-year-old patient requests laser treatment for a yellowed toenail. The patient experiences no pain, has no systemic diseases, and simply dislikes the appearance of the nail. While the diagnosis code remains B35.1, the service does not meet the threshold for medical necessity. The provider must issue an Advance Beneficiary Notice to a Medicare patient, or inform a commercial patient that the cosmetic treatment will be an out-of-pocket expense.
Resolving common tinea unguium claim denials
Claims containing the tinea unguium ICD-10 code frequently face scrutiny from payer algorithms. Most denials stem from frequency limits and incomplete documentation.
Medicare restricts routine foot care frequency. Payer policies generally allow nail debridement once every 60 days. If a provider bills for CPT 11720 or 11721 with the B35.1 diagnosis before 60 days have passed since the previous treatment, the payer will deny the claim automatically. The only exception occurs when the provider documents a new, acute complication that requires immediate intervention.
Denials also occur when the diagnosis code lacks specificity. Some electronic health record systems default to vague codes like L60.9 (Nail disorder, unspecified). Coders must verify that the physician’s note supports the specific B35.1 code. If the pathology report indicates a non-dermatophyte mold rather than a dermatophyte, coders must check specific payer policies. Some insurers require B36.9 (Superficial mycosis, unspecified) instead of B35.1 for non-dermatophyte fungal nail infections.
Proper diagnosis coding directly affects population health tracking and antimicrobial stewardship. When medical coders accurately capture the prevalence of dermatophyte infections using B35.1, public health organizations can monitor treatment resistance patterns. According to a 2023 surveillance summary by the American Academy of Dermatology, dermatophyte resistance to oral antifungals has increased globally. Tracking treatment outcomes against specific ICD-10 codes helps researchers identify which populations face the highest risk of recurrent fungal nail infections. Thorough documentation protects the medical practice from recoupment during post-payment audits. By consistently recording the physical findings, ordering appropriate laboratory tests, and detailing the patient’s symptoms, healthcare providers ensure compliance with local and national billing guidelines. Correct application of the B35.1 diagnosis code establishes a clear clinical narrative from the initial assessment through the final reimbursement cycle.