


Patient registration dictates the financial success of a medical claim. If a front desk worker incorrectly assumes a patient has a PPO instead of an HMO, the clinic will likely perform unapproved services. The resulting claim will fail.
The Blue Cross Blue Shield network operates differently than a single centralized insurance corporation. It functions as a collection of 33 separate local entities sharing a common trademark. Medical billers face the daily challenge of decoding exactly which coverage rules apply to each patient. A card issued in California carries completely different authorization requirements than a card issued in Florida.
Identifying the specific plan structure requires more than looking at the company logo. Clinic staff must analyze the typography on the physical card, interpret electronic data interchange (EDI) files, and navigate complex routing protocols.
Analyzing the BCBS member ID card
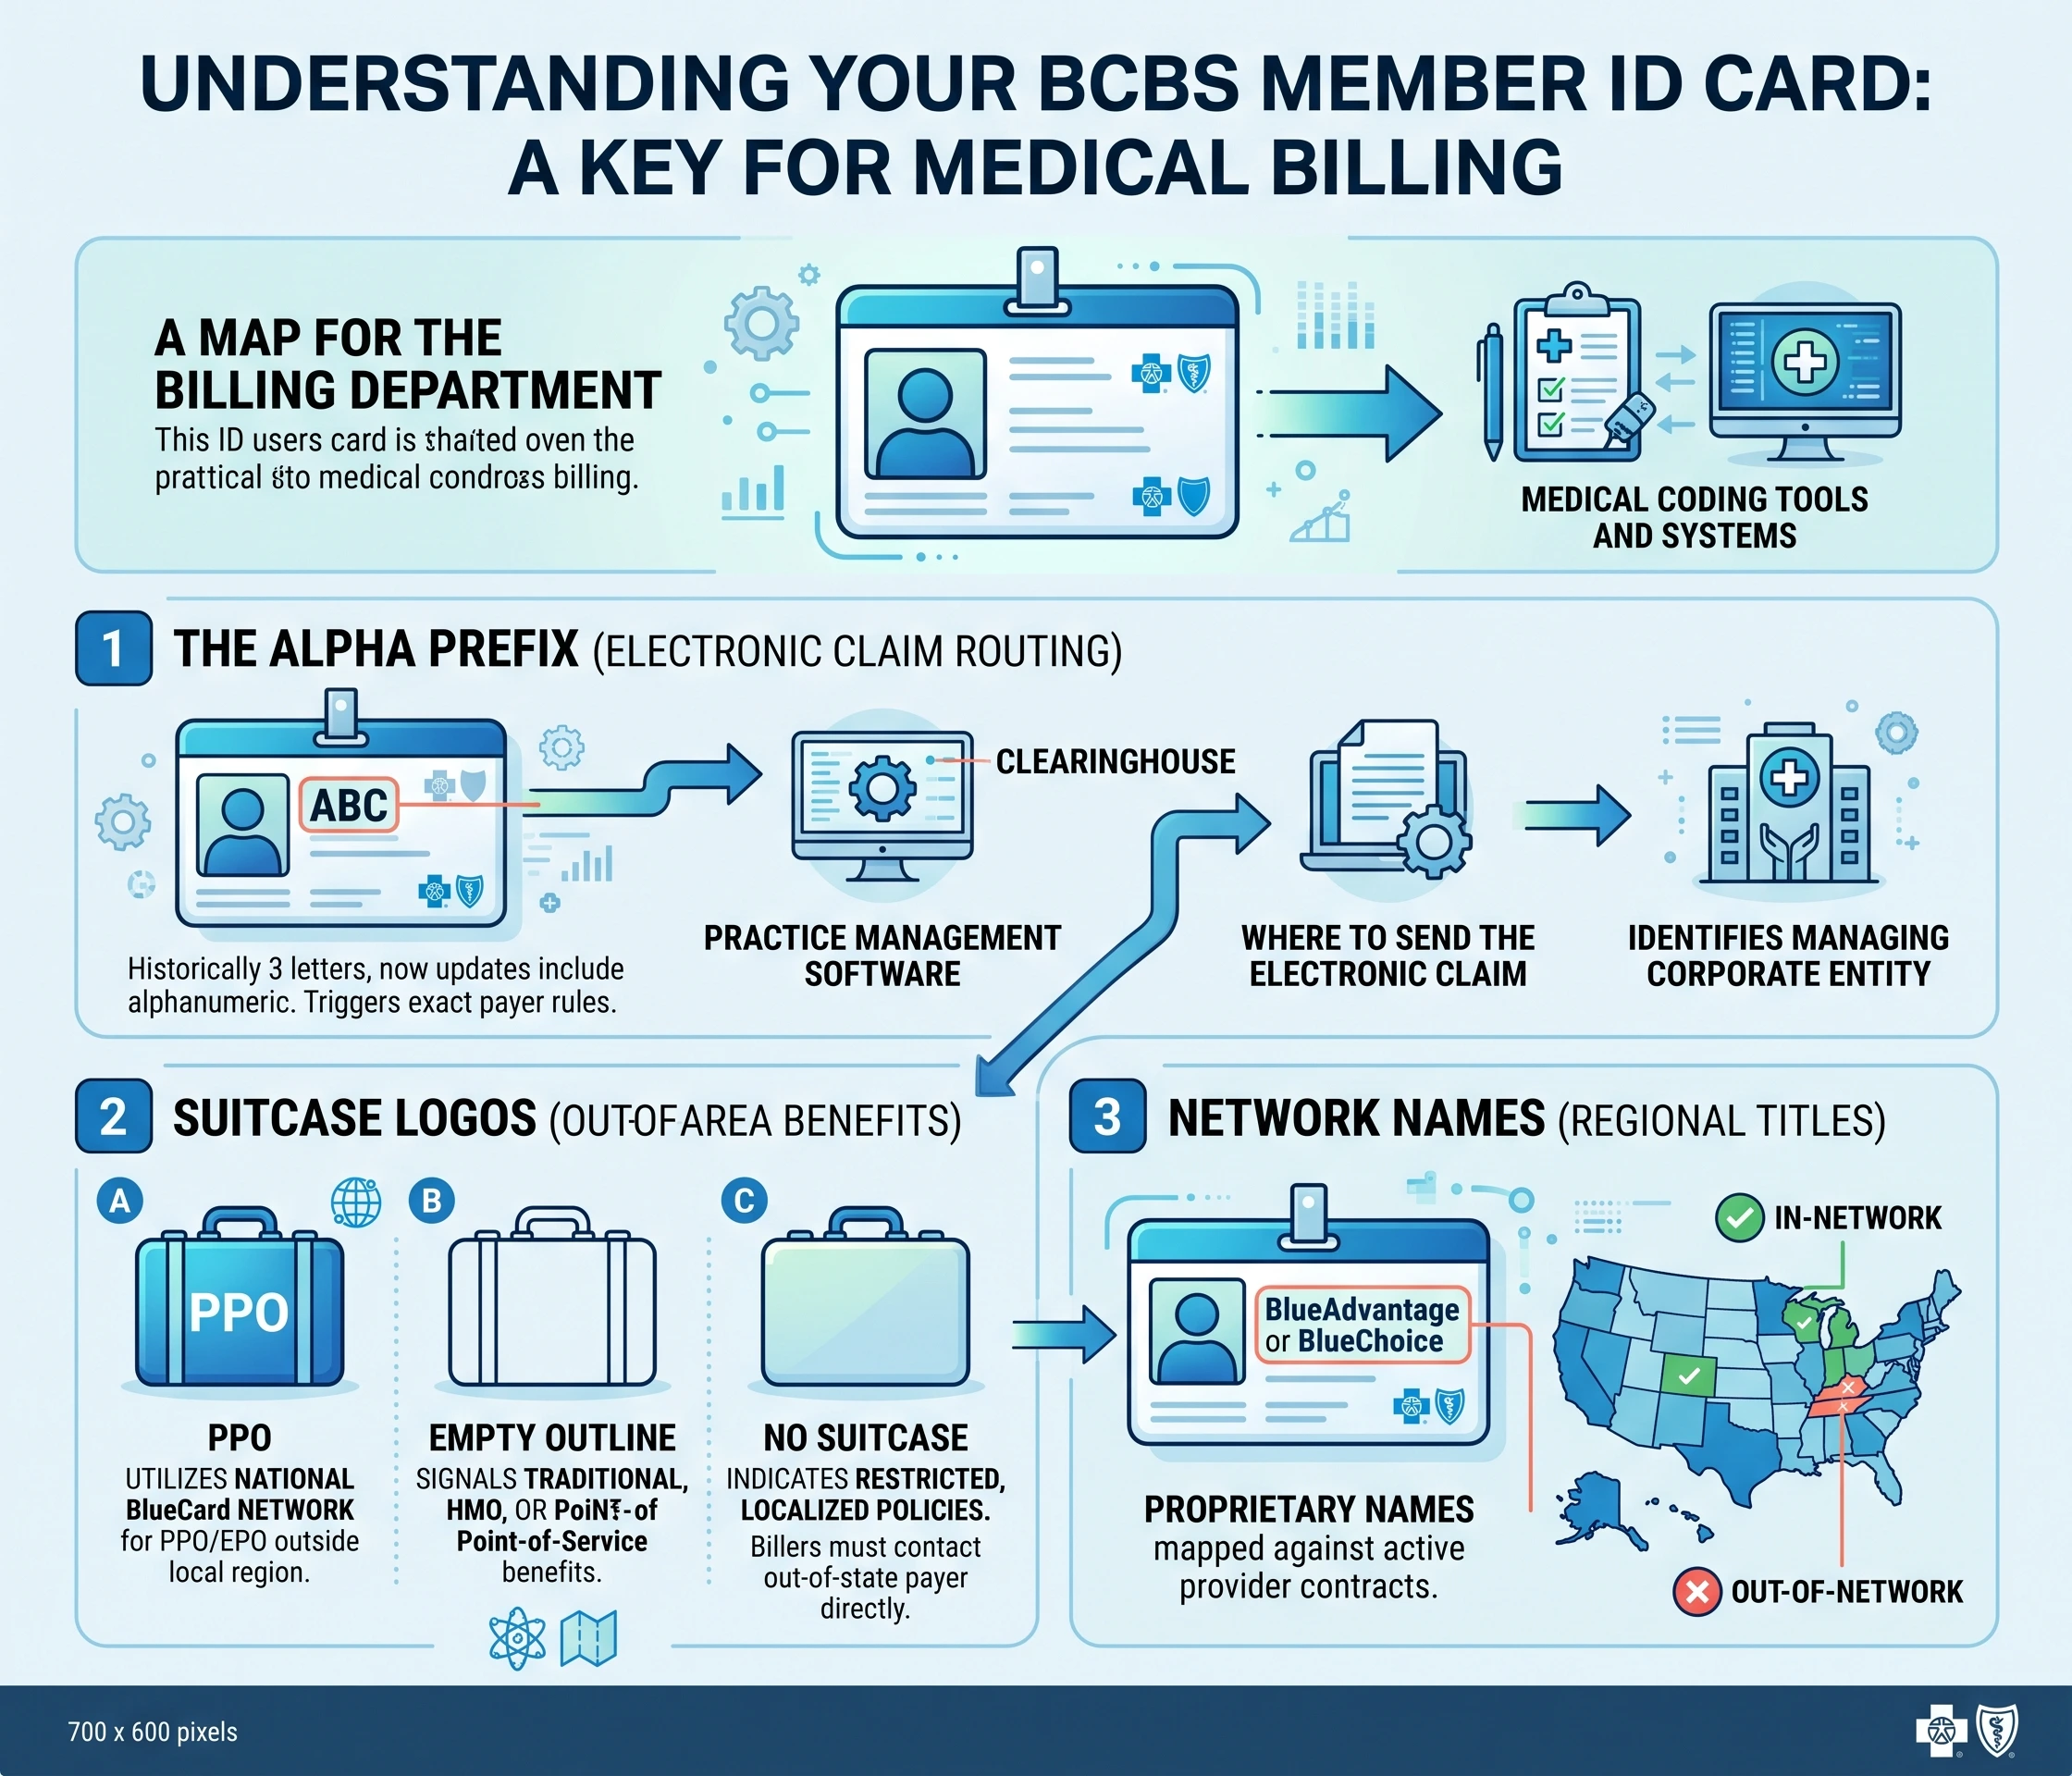
The physical insurance card acts as a map for the billing department. Patients look at the group numbers, but medical coders analyze specific visual markers that dictate electronic claim routing.
The alpha prefix
Every member ID carries specific routing instructions. Historically, this started with a three-letter prefix, though recent updates include alphanumeric sequences. This code tells the practice management software where to send the electronic claim. It identifies the specific corporate entity managing the patient’s benefits.
The characters themselves do not spell out the plan category. However, entering this prefix correctly into the clearinghouse software triggers the system to pull the exact payer rules for that specific patient.
The suitcase logos
The bottom section of the physical card usually displays a small suitcase icon. This graphic explicitly dictates out-of-area benefit rules.
- A suitcase showing “PPO” inside means the member utilizes the national BlueCard network for PPO or EPO coverage outside their local region.
- An empty suitcase outline signals traditional, HMO, or Point-of-Service benefits.
- Cards lacking any suitcase graphic entirely indicate restricted, localized policies. Billers must contact the out-of-state payer directly because the policy does not process through the national shared network.
Network names printed on the card
Beyond the standard logo, cards frequently display regional network titles. You will see proprietary names like “BlueAdvantage” or “BlueChoice.” The billing department maps these printed names against their active provider contracts. A clinic might hold a contract for one state’s “BlueSelect” network but remain out-of-network for a different state’s similarly named product.
How do I know if I have HMO or PPO Blue Cross Blue Shield?
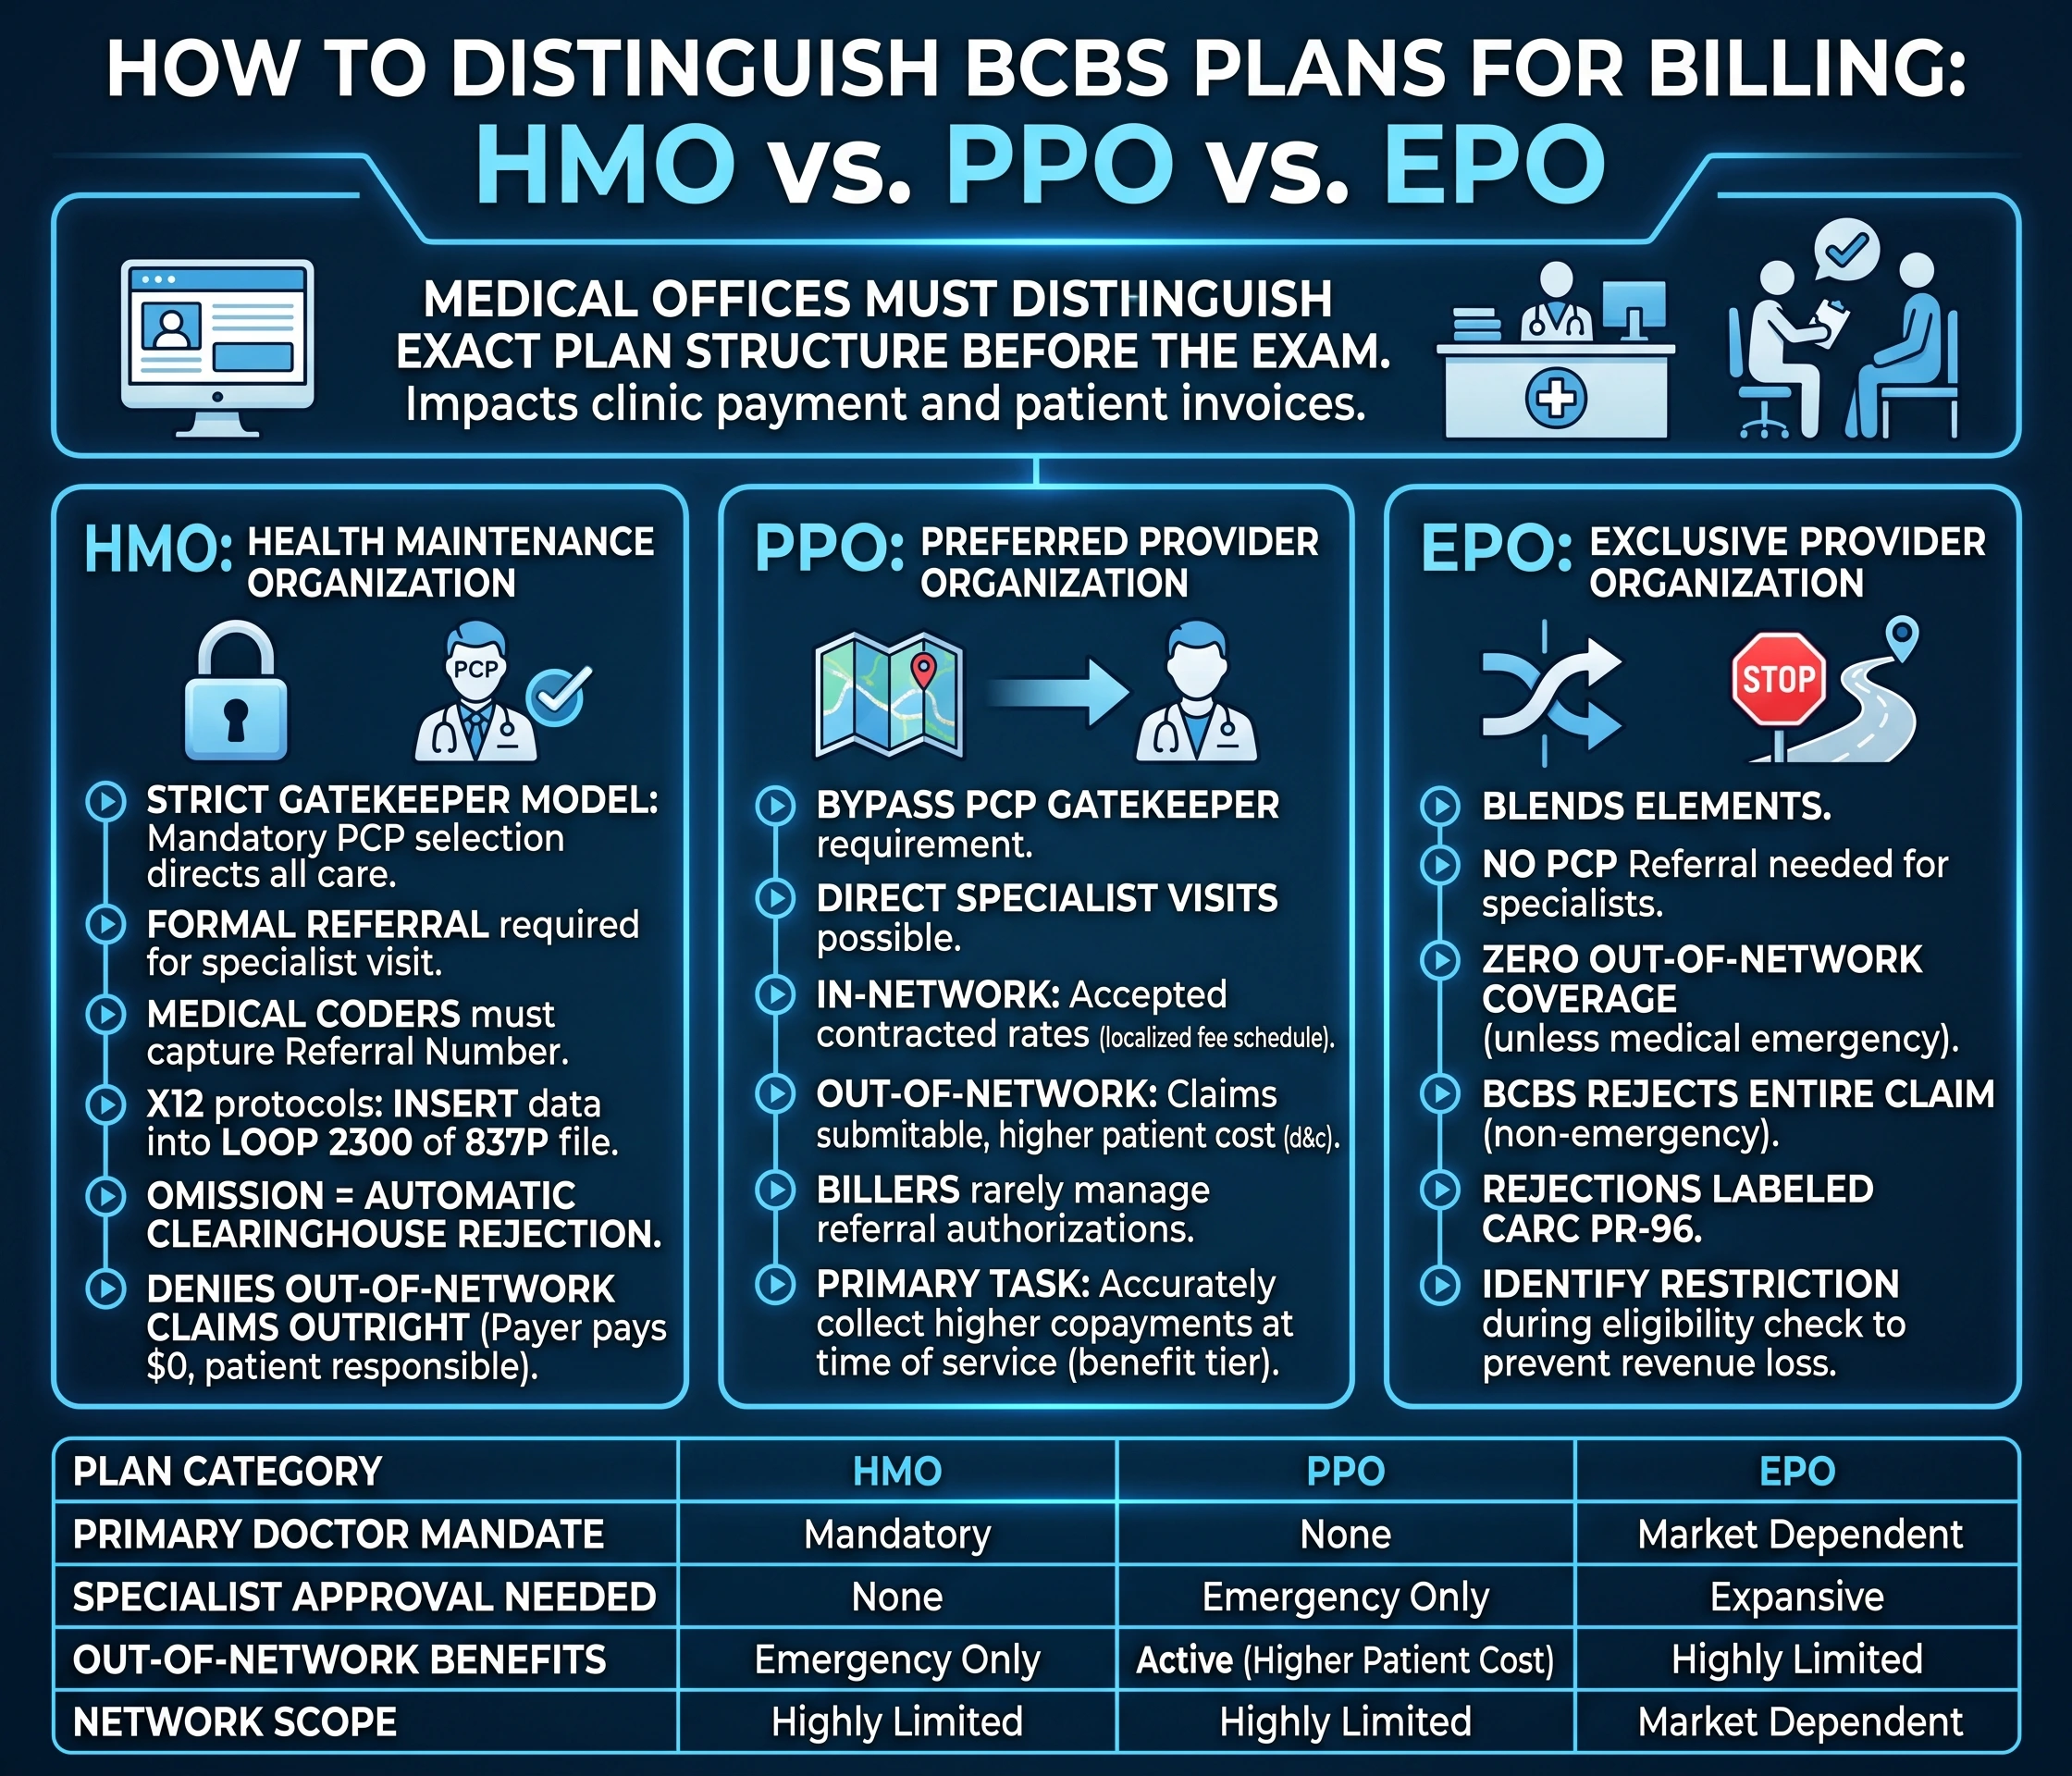
Medical offices must distinguish the exact plan structure before the physician enters the exam room. The differences between these policies dictate whether the clinic gets paid or the patient receives an unexpected invoice.
HMO billing requirements
Health Maintenance Organizations operate on a strict gatekeeper model. The patient must select a Primary Care Provider (PCP). This specific physician directs all subsequent care. When a patient requires a specialist visit, the primary physician generates a formal referral.
Medical coders must capture this exact referral number. The X12 electronic transaction protocols mandate that billers insert this authorization data into Loop 2300 of the 837P file. Omitting this segment triggers an automatic clearinghouse rejection. HMO plans deny out-of-network claims outright. If a patient visits an uncontracted doctor without authorization, the payer pays zero, leaving the patient financially responsible for the total balance.
PPO billing requirements
Preferred Provider Organizations remove the gatekeeper requirement. Patients bypass primary care physicians and schedule directly with specialists.
In-network physicians accept contracted rates based on a localized fee schedule. Out-of-network physicians can also submit claims, but the payer shifts a larger portion of the cost to the patient through higher deductibles and coinsurance rates. Billers rarely manage referral authorizations for PPO patients. Instead, their primary task involves accurately collecting higher copayments at the time of service based on the patient’s specific benefit tier.
EPO billing requirements
Exclusive Provider Organizations blend specific elements of the other two models. Patients do not need a primary care physician’s referral to schedule a visit with a specialist. However, they possess zero out-of-network coverage.
If a patient visits an uncontracted doctor, BCBS rejects the entire claim unless the encounter qualifies as a true, documented medical emergency. Billers frequently see these rejections labeled with Claim Adjustment Reason Code (CARC) PR-96. Identifying this restriction during the initial eligibility check prevents massive revenue loss for the practice.
Plan Category | Primary Doctor Mandate | Specialist Approval Needed | Out-of-Network Benefits | Network Scope |
HMO | Mandatory | Mandatory | Emergency Only | Highly Limited |
PPO | None | None | Active (Higher Patient Cost) | Expansive |
EPO | None | None | Emergency Only | Market Dependent |
Using electronic verification and the provider portal
Plastic cards degrade, get lost, or contain obsolete data. A patient might carry a PPO card from a previous employer while actually enrolled in an active HMO. Federal laws regulate how medical software verifies this data electronically.
The EDI 270/271 transaction set
The Health Insurance Portability and Accountability Act sets the standards for digital healthcare transactions. The software utilizes the 270/271 format for eligibility. The system sends a 270 request file to the payer. The payer’s servers respond with a 271 eligibility file.
This return document confirms the active dates, the specific plan category, and current deductible totals. It also lists any currently assigned primary care physician. Medical coders read this raw EDI data to confirm coverage limits rather than trusting verbal statements from the patient.
Web-based verification portals
Most regional branches utilize third-party web interfaces for manual checks. Availity Essentials operates as the primary portal for many states. Front office personnel input the patient’s identification number and birth date into this secure site. The resulting digital document explicitly states the plan category under the main coverage tab.
The BlueCard program and claim routing
Understanding coverage requires knowing how these independent companies pass data across state lines. The BlueCard system connects medical facilities with different corporate branches.
The process involves two separate agencies:
- The Home Plan manages the patient’s actual policy and holds the funds.
- The Host Plan operates in the state where the physician practices and holds the provider contracts.
Consider a patient from Texas receiving treatment at a clinic in New York. The New York clinic submits the charges to Empire BlueCross BlueShield (the local Host Plan). The software reads the alphanumeric prefix, identifies the Texas origin, and forwards the data to BCBS of Texas (the Home Plan). The Texas office applies the specific PPO or HMO rules and authorizes payment. The New York office then issues the final check to the local clinic based on local contracted rates.
Regulatory requirements for the Summary of Benefits and Coverage
Federal law provides another method for identifying coverage. The Affordable Care Act added Section 2715 to the Public Health Service Act. This legislation forces insurers to publish a standardized document called the Summary of Benefits and Coverage (SBC).
The federal government controls the exact layout of this form. On the first page, directly under the coverage dates, the insurer must print the precise plan category. It will display exact text such as “Plan Type: HMO” or “Plan Type: EPO.”
If electronic systems fail and the ID card lacks clear markings, billers can ask patients to log into their smartphone applications and download this document. It acts as a definitive legal record of the policy structure, allowing the clinic to proceed with treatment under the correct billing assumptions.
Navigating provider directories and referrals
Front desk workers often assist patients with specialist recommendations. The exact plan category determines which database the staff searches.
An HMO enrollee must stay within a highly specific regional database. Recommending a doctor who only holds a PPO contract guarantees a denied claim for that specialist. The primary care clinic must log into the payer portal and route the referral specifically to an HMO-contracted provider.
EPO policies demand even stricter verification. Since the patient doesn’t need a formal referral but faces total denial for out-of-network care, referring clinics carry a heavy administrative burden. The staff must cross-reference the exact EPO network tier before sending the patient to another facility.
Accurate data entry dictates the financial survival of a medical clinic. Billers isolate the exact plan category by decoding the prefix, reading the EDI responses, and verifying network directories. Correctly identifying the policy upfront prevents administrative appeals and protects patients from unexpected medical debt.